




 Previous
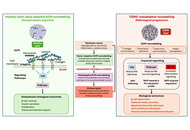
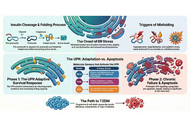
Type 2 diabetes mellitus (T2DM) is characterised by progressive insulin resistance and pancreatic β-cell dysfunction, ultimately resulting in impaired glucose homeostasis. While metabolic and genetic factors are central to disease development, increasing evidence indicates that disruption of the pancreatic islet extracellular matrix (ECM) may be an important contributor to β-cell failure. The islet ECM is not merely a structural scaffold but a dynamic signalling network that regulates β-cell adhesion, survival, proliferation and insulin secretion through integrin-mediated signalling and mechanotransduction pathways. In healthy islets, a tightly organised ECM composed of collagens, laminins, fibronectin and glycosaminoglycans maintains basement membrane integrity, vascular support and coordinated cell-matrix communication. In T2DM, chronic hyperglycaemia, inflammation and oxidative stress are associated with pathological ECM remodelling and are thought to contribute to alterations in islet ECM composition characterised by fibrosis, altered matrix composition, dysregulated proteolysis and excessive ECM protein deposition. These changes are potentially associated with impaired integrin signalling, altered mechanotransduction and compromised β-cell function and viability in experimental models. ECM remodelling may also promote islet stiffening, vascular dysfunction, amyloid deposition and inflammatory signalling, further amplifying β-cell decline. This review synthesises current understanding of islet ECM composition, cell-matrix interactions and the molecular mechanisms linking metabolic stress to ECM remodelling. It also highlights emerging preclinical evidence that incretin-based therapies, including semaglutide and tirzepatide, are associated with changes in ECM-related pathways, while emphasising that these effects may be secondary to improved metabolic control and that direct ECM-targeting effects have yet to be established. Finally, we discuss emerging therapeutic strategies targeting fibrosis, mechanotransduction and matrix signalling pathways, and identify key knowledge gaps regarding the causal contribution of ECM remodelling to β-cell dysfunction and loss in T2DM.
Type 2 diabetes mellitus (T2DM) is characterised by progressive insulin resistance and pancreatic β-cell dysfunction, ultimately resulting in impaired glucose homeostasis. While metabolic and genetic factors are central to disease development, increasing evidence indicates that disruption of the pancreatic islet extracellular matrix (ECM) may be an important contributor to β-cell failure. The islet ECM is not merely a structural scaffold but a dynamic signalling network that regulates β-cell adhesion, survival, proliferation and insulin secretion through integrin-mediated signalling and mechanotransduction pathways. In healthy islets, a tightly organised ECM composed of collagens, laminins, fibronectin and glycosaminoglycans maintains basement membrane integrity, vascular support and coordinated cell-matrix communication. In T2DM, chronic hyperglycaemia, inflammation and oxidative stress are associated with pathological ECM remodelling and are thought to contribute to alterations in islet ECM composition characterised by fibrosis, altered matrix composition, dysregulated proteolysis and excessive ECM protein deposition. These changes are potentially associated with impaired integrin signalling, altered mechanotransduction and compromised β-cell function and viability in experimental models. ECM remodelling may also promote islet stiffening, vascular dysfunction, amyloid deposition and inflammatory signalling, further amplifying β-cell decline. This review synthesises current understanding of islet ECM composition, cell-matrix interactions and the molecular mechanisms linking metabolic stress to ECM remodelling. It also highlights emerging preclinical evidence that incretin-based therapies, including semaglutide and tirzepatide, are associated with changes in ECM-related pathways, while emphasising that these effects may be secondary to improved metabolic control and that direct ECM-targeting effects have yet to be established. Finally, we discuss emerging therapeutic strategies targeting fibrosis, mechanotransduction and matrix signalling pathways, and identify key knowledge gaps regarding the causal contribution of ECM remodelling to β-cell dysfunction and loss in T2DM.
DOI: https://doi.org/10.37349/eemd.2026.101484
This article belongs to the special issue Innovative Strategies for Diabetes and Metabolic Disorders: Current and Future Directions


Type 2 diabetes is an error in the glycemic control system caused by insulin resistance. Self-organizing control systems use artificial intelligence to monitor and correct how they function and are used in modern applications of robotics. The development of type 2 diabetes is gradual and reversible through lifestyle changes, and this is consistent with insulin resistance being formed through a self-organizing or intelligent control system rather than the traditional control system on which current biomedical control systems are modelled. Lifestyles that induce high levels of glycemic variation would, in an intelligent control system, be detected as excessive oscillation, and an intelligent system can reduce oscillation by reducing the amplification. Insulin resistance represents low amplification in the glycemic control system. Intelligent control system functioning requires a network architecture, so if the glycemic control system is self-organizing, then it should be part of a network system that provides intelligent functioning for other control systems, and error in the glycemic control system would contribute to errors in other control systems and to a state of general network dysregulation. Intelligent systems theory explains how the comorbidities of type 2 diabetes and obesity would form through the dysregulation of a network of metabolic, immune, endocrine, and neurological pathways. The theory predicts that medical and lifestyle interventions for type 2 diabetes could improve comorbidities, but that comorbidities would reduce the effectiveness of those interventions. Studies are proposed to test this new theory that provides a non-blaming narrative for patients and could form a prequel to patient education.
Type 2 diabetes is an error in the glycemic control system caused by insulin resistance. Self-organizing control systems use artificial intelligence to monitor and correct how they function and are used in modern applications of robotics. The development of type 2 diabetes is gradual and reversible through lifestyle changes, and this is consistent with insulin resistance being formed through a self-organizing or intelligent control system rather than the traditional control system on which current biomedical control systems are modelled. Lifestyles that induce high levels of glycemic variation would, in an intelligent control system, be detected as excessive oscillation, and an intelligent system can reduce oscillation by reducing the amplification. Insulin resistance represents low amplification in the glycemic control system. Intelligent control system functioning requires a network architecture, so if the glycemic control system is self-organizing, then it should be part of a network system that provides intelligent functioning for other control systems, and error in the glycemic control system would contribute to errors in other control systems and to a state of general network dysregulation. Intelligent systems theory explains how the comorbidities of type 2 diabetes and obesity would form through the dysregulation of a network of metabolic, immune, endocrine, and neurological pathways. The theory predicts that medical and lifestyle interventions for type 2 diabetes could improve comorbidities, but that comorbidities would reduce the effectiveness of those interventions. Studies are proposed to test this new theory that provides a non-blaming narrative for patients and could form a prequel to patient education.
DOI: https://doi.org/10.37349/eemd.2026.101483
Metabolic diseases including obesity, type 2 diabetes mellitus (T2DM), and metabolic dysfunction-associated steatotic liver disease (MASLD) are increasing rapidly worldwide and contribute substantially to morbidity, mortality, and healthcare costs. Current therapies, including glucagon-like peptide-1 receptor agonists (GLP-1RAs), have transformed metabolic disease management but remain limited by high costs, adverse effects, treatment discontinuation, and the need for chronic administration. Duodenal mucosal resurfacing (DMR) and gene therapy represent potential long-term strategies for metabolic disease modulation. DMR is a minimally invasive endoscopic procedure that ablates and regenerates the duodenal mucosa, with clinical studies demonstrating improvements in glycemic control, insulin sensitivity, and liver fibrosis markers in patients with T2DM and MASLD. Although the precise mechanisms remain incompletely understood, recent evidence suggests that DMR may induce significant genetic, enteroendocrine, and gut microbiota changes involving pathways associated with glucose uptake, intestinal differentiation, and metabolic signaling. In parallel, advances in gene therapy using adeno-associated viral (AAV) vectors and lipid nanoparticles (LNPs) have shown potential in sustained modulation of insulin secretion, GLP-1 signaling, and β-cell regeneration. These approaches may overcome several limitations of conventional pharmacotherapy by providing longer-lasting therapeutic effects with fewer pharmacokinetic fluctuations. This review highlights the biological rationale underlying DMR and gene therapy, evaluates current preclinical and clinical evidence, and discusses limitations related to safety, efficacy, delivery specificity, manufacturing scalability, and ethical accessibility. Additionally, it explores the potential intersection between DMR and gene therapy, proposing that genes identified through DMR-mediated metabolic remodeling may serve as future therapeutic targets. This review also hypothesizes how DMR and gene therapy could be used together to have long-lasting complementary effects. Together, these technologies represent promising and potentially complementary strategies that could reshape the therapeutic landscape for obesity, diabetes, and MASLD.
Metabolic diseases including obesity, type 2 diabetes mellitus (T2DM), and metabolic dysfunction-associated steatotic liver disease (MASLD) are increasing rapidly worldwide and contribute substantially to morbidity, mortality, and healthcare costs. Current therapies, including glucagon-like peptide-1 receptor agonists (GLP-1RAs), have transformed metabolic disease management but remain limited by high costs, adverse effects, treatment discontinuation, and the need for chronic administration. Duodenal mucosal resurfacing (DMR) and gene therapy represent potential long-term strategies for metabolic disease modulation. DMR is a minimally invasive endoscopic procedure that ablates and regenerates the duodenal mucosa, with clinical studies demonstrating improvements in glycemic control, insulin sensitivity, and liver fibrosis markers in patients with T2DM and MASLD. Although the precise mechanisms remain incompletely understood, recent evidence suggests that DMR may induce significant genetic, enteroendocrine, and gut microbiota changes involving pathways associated with glucose uptake, intestinal differentiation, and metabolic signaling. In parallel, advances in gene therapy using adeno-associated viral (AAV) vectors and lipid nanoparticles (LNPs) have shown potential in sustained modulation of insulin secretion, GLP-1 signaling, and β-cell regeneration. These approaches may overcome several limitations of conventional pharmacotherapy by providing longer-lasting therapeutic effects with fewer pharmacokinetic fluctuations. This review highlights the biological rationale underlying DMR and gene therapy, evaluates current preclinical and clinical evidence, and discusses limitations related to safety, efficacy, delivery specificity, manufacturing scalability, and ethical accessibility. Additionally, it explores the potential intersection between DMR and gene therapy, proposing that genes identified through DMR-mediated metabolic remodeling may serve as future therapeutic targets. This review also hypothesizes how DMR and gene therapy could be used together to have long-lasting complementary effects. Together, these technologies represent promising and potentially complementary strategies that could reshape the therapeutic landscape for obesity, diabetes, and MASLD.
DOI: https://doi.org/10.37349/eemd.2026.101482
This article belongs to the special issue Innovative Strategies for Diabetes and Metabolic Disorders: Current and Future Directions
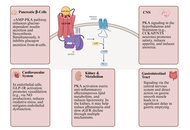
With the rising global prevalence of obesity and type 2 diabetes, metabolic disorders have become major drivers of cardiovascular morbidity and mortality worldwide. Cardiovascular-kidney-metabolic (CKM) syndrome encompasses obesity, type 2 diabetes mellitus (T2DM), chronic kidney disease (CKD), and cardiovascular disease (CVD), all of which share common pathophysiological pathways. Glucagon-like peptide-1 receptor agonists (GLP-1RAs), a novel class of antihyperglycemic agents, have demonstrated pleiotropic effects—including weight reduction, blood pressure lowering, albuminuria reduction, decreased major adverse cardiovascular events (MACE), and slowed progression of renal dysfunction. These benefits position GLP-1RAs as a potential cornerstone therapy for CKM syndrome. This review synthesizes recent advances in GLP-1RA research within the CKM framework, explores their underlying mechanisms, and offers insights to refine diagnostic and therapeutic strategies for cardiometabolic diseases.
With the rising global prevalence of obesity and type 2 diabetes, metabolic disorders have become major drivers of cardiovascular morbidity and mortality worldwide. Cardiovascular-kidney-metabolic (CKM) syndrome encompasses obesity, type 2 diabetes mellitus (T2DM), chronic kidney disease (CKD), and cardiovascular disease (CVD), all of which share common pathophysiological pathways. Glucagon-like peptide-1 receptor agonists (GLP-1RAs), a novel class of antihyperglycemic agents, have demonstrated pleiotropic effects—including weight reduction, blood pressure lowering, albuminuria reduction, decreased major adverse cardiovascular events (MACE), and slowed progression of renal dysfunction. These benefits position GLP-1RAs as a potential cornerstone therapy for CKM syndrome. This review synthesizes recent advances in GLP-1RA research within the CKM framework, explores their underlying mechanisms, and offers insights to refine diagnostic and therapeutic strategies for cardiometabolic diseases.
DOI: https://doi.org/10.37349/eemd.2026.101481
Aim:
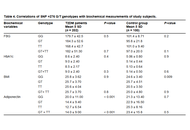
Type 2 diabetes mellitus is a polygenic disorder influenced by multiple genes and environmental factors. Polymorphisms in the adiponectin gene are linked to insulin resistance, serum adiponectin levels, and type 2 diabetes mellitus. This study investigated the association between adiponectin levels, the ADIPOQ +276G>T single nucleotide polymorphism (SNP), and type 2 diabetes in the Sudanese population.
Methods:
A case-control study involved 202 individuals with type 2 diabetes and 100 controls, after providing written informed consent. Blood samples were collected after overnight fasting for measurements of fasting blood glucose (FBG), and hemoglobin A1C (HbA1c) levels were measured using enzymatic methods. Participants’ body mass index (BMI) was calculated based on weight and height measurements. Adiponectin levels were measured by sandwich ELISA. Adiponectin gene +276G>T SNP was performed using polymerase chain reaction-restriction fragment length polymorphism (PCR-RFLP).
Results:
Patients with type 2 diabetes had significantly lower adiponectin levels compared to controls (P < 0.001). The distribution of the +276G>T SNP genotypes and the T allele was significantly different between diabetic patients and controls, with TT, GT, and T allele more frequent in diabetics (P < 0.05). Adiponectin levels varied by genotype, with GG carriers having higher levels than GT and TT carriers, who exhibited significantly lower levels (P < 0.001).
Conclusions:
The +276G>T SNP in the adiponectin gene is associated with reduced adiponectin levels in individuals with type 2 diabetes in the Sudanese population.
DOI: https://doi.org/10.37349/eemd.2026.101480
This article belongs to the special issue Current Views on Pathogenesis, Diagnosis and Management of Type 2 Diabetes Mellitus and Its Complications and Related Conditions
Aim:
The aim of this study was to investigate the relationship between the triglyceride-glucose (TyG) index and hormonal, biochemical, and lipid parameters in patients with polycystic ovary syndrome (PCOS).
Methods:
In this retrospective single-center study, 2,243 outpatient records were reviewed. Among 696 patients diagnosed with PCOS between 2015 and 2022, 233 newly diagnosed and treatment-naive patients were included. TyG was calculated using fasting triglyceride and glucose values. Correlations between TyG and laboratory parameters were assessed. The optimal TyG cut-off for insulin resistance was evaluated using HOMA-IR and receiver operating characteristic analysis.
Results:
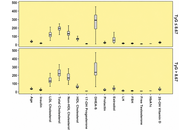
TyG was positively correlated with HbA1c, age, LDL cholesterol, total cholesterol, non-HDL cholesterol, insulin, and HOMA-IR, and negatively correlated with HDL cholesterol. The optimal TyG cut-off was 8.67, with an AUC of 0.709, sensitivity of 50.49%, and specificity of 85.38%. Patients with TyG values above the cut-off had higher age, insulin, LDL cholesterol, total cholesterol, non-HDL cholesterol, and HbA1c values, whereas HDL cholesterol and estradiol levels were lower.
Conclusions:
TyG was associated with insulin resistance markers and dyslipidemic parameters in patients with PCOS. These findings support the potential clinical utility of TyG as a simple surrogate marker for metabolic risk assessment in PCOS.
DOI: https://doi.org/10.37349/eemd.2026.101479
Aim:
Assess the benefits of using a diabetes app and connected blood glucose (BG) meter in people with type 2 diabetes (PwT2D) with higher-than-recommended mean BG. It is well understood that sustained higher levels of glycemia are linked to diabetes related complications and that early intervention to reduce hyperglycemia is an important clinical goal.
Methods:
We sourced server data from a total population of 22,696 PwT2D using the OneTouch Reveal diabetes app in conjunction with a OneTouch Verio Flex or Reflect BG meter. We identified three groups (mean BG > 180, > 155, and between > 155 and < 180 mg/dL) at higher risk for diabetes-associated complications based on their hyperglycemia. Data from their first 14 days using the app was compared with the last 14 days at the end of each timeframe, using paired within-subject differences.
Results:
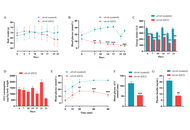
At 1 year in PwT2D with baseline mean BG > 155 mg/dL, readings in range (RIR) improved by 24.0%, and mean BG decreased by 35.9 mg/dL, from 196.4 mg/dL to 160.5 mg/dL. These improvements were due to reductions in hyperglycemic readings. Subjects with the highest baseline mean BG of > 180 mg/dL had the greatest reduction (–54.3 mg/dL) in mean BG after experiencing the new app and meter for 1 year. Those engaging more often with the app had greater improvements in glycemia.
Conclusions:
In PwT2D with higher-than-recommended mean BG, substantial improvements in glycemia were associated with subjects using a diabetes app with a connected blood glucose meter at 3 months, and these improvements were sustained out to 1-year.
DOI: https://doi.org/10.37349/eemd.2026.101478
Background:
Type 2 diabetes (T2D) is a chronic metabolic condition requiring sustained pharmacological and behavioural management. Suboptimal medication adherence remains a major barrier to achieving adequate glycaemic control and is associated with increased morbidity, mortality, and healthcare costs. Patient-centred care (PCC) has been widely recommended as an approach to enhance patient engagement, adherence, and clinical outcomes; however, evidence regarding its effectiveness remains inconsistent. This systematic review aimed to synthesise evidence from primary studies evaluating PCC interventions on medication adherence, glycaemic control, and psychosocial outcomes in adults with T2D.
Methods:
This review followed PRISMA 2020 guidelines and was prospectively registered in PROSPERO (CRD420251115067). A comprehensive search of MEDLINE, Embase, EMCare, CINAHL, PsycINFO, and the Cochrane Library was conducted for studies published between 2005 and 2025. Eligible studies included primary research evaluating PCC interventions in adults with T2D and reporting adherence or clinical outcomes. Data were synthesised narratively due to heterogeneity, and vote counting based on direction of effect was applied. Risk of bias was assessed using RoB 2.0, ROBINS-I, and CASP tools, and overall certainty of evidence was evaluated using the GRADE framework.
Results:
Eighteen studies were included, comprising seven randomised controlled trials, eight observational studies, and three qualitative studies. PCC interventions consistently improved medication adherence and psychosocial outcomes, including patient empowerment and engagement. In contrast, effects on glycaemic control were variable, with four studies reporting improvement, seven showing no effect, and three demonstrating mixed findings. Overall, the evidence suggests a predominantly positive but inconsistent effect on HbA1c.
Discussion:
PCC interventions appear effective in improving behavioural and psychosocial outcomes but demonstrate inconsistent impact on glycaemic control. These findings suggest that PCC should be considered a supportive strategy to enhance engagement and adherence rather than a standalone intervention for improved clinical outcomes. Further research is required to identify optimal intervention components that can improve clinical outcomes.
DOI: https://doi.org/10.37349/eemd.2026.101477
This article belongs to the special issue Current Views on Pathogenesis, Diagnosis and Management of Type 2 Diabetes Mellitus and Its Complications and Related Conditions
Aim:
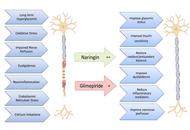
Diabetic neuropathy is the most prevalent diabetic complication, impacting up to 60% of people with diabetes. It is characterized by distal symmetrical loss of sensory function in the lower extremities, presenting with spontaneous excruciating neuropathic pain, hyperalgesia, and allodynia that impairs quality of life. The current work aims to evaluate the neuroprotective potential of naringin (a citrus flavonoid) and examine its ability to improve Streptozotocin (STZ)-induced diabetic neuropathic pain by investigating its hypoglycemic, lipid-lowering, anti-inflammatory, and antioxidant effects.
Methods:
Diabetes was induced in 30 of 40 male Sprague-Dawley rats via a single STZ injection (45 mg/kg). Rats were divided into four groups: normal control, diabetic control, naringin-treated, and glimepiride-treated (positive control). After treatment, serum and brain tissues were collected to assess biochemical parameters. Pain-related behaviors were evaluated using hot plate, tail immersion, and von Frey filament tests.
Results:
A significant increase in the serum levels of glucose, triglyceride, total cholesterol, low-density lipoprotein-cholesterol, and nitric oxide, with a concomitant decrease in body weight, plasma insulin, and high-density lipoprotein-cholesterol, was observed in diabetic rats. Also, the brain level of malondialdehyde was increased, while that of reduced glutathione, glutathione peroxidase, catalase, and superoxide dismutase were markedly decreased. Furthermore, diabetic rats showed a marked increase in plasma levels of inflammatory cytokines including interleukin-6 and tumor necrosis factor-α. Moreover, hot plate, tail immersion, and von Frey tests revealed hyperalgesia in diabetic rats. Treatment with naringin and glimepiride reduced pain hypersensitivity, restored body weight, and nearly normalized the altered biochemical parameters, more significantly with naringin than with glimepiride.
Conclusions:
These results may highlight the potential effects of naringin as a therapeutic strategy for diabetes and its complications, including peripheral neuropathy.
DOI: https://doi.org/10.37349/eemd.2026.101476
This article belongs to the special issue Current Views on Pathogenesis, Diagnosis and Management of Type 2 Diabetes Mellitus and Its Complications and Related Conditions
Aim:
Estrogens regulate energy balance and glucose homeostasis, but whether they coordinate endocrine changes across the gut–pancreas axis in obesity remains unclear. This study examined whether ethinyl estradiol (EE2) improves metabolic control in obese diabetic mice through combined effects on pancreatic islets and intestinal enteroendocrine cells.
Methods:
Female ob/ob mice received EE2 (4,000 ng/mL) or vehicle in drinking water for 21 days. Body weight, food intake, glucose levels, glucose tolerance, pancreatic islet composition, and ileal enteroendocrine cell populations were assessed using biochemical assays and immunohistochemistry.
Results:
EE2 significantly reduced body weight and energy intake and produced sustained lowering of blood glucose with markedly improved glucose tolerance and reduced terminal insulin levels. EE2 increased islet density and beta-cell proliferation and shifted islet size distribution toward larger islets, consistent with enhanced islet growth. Alpha-cell area was significantly reduced, indicating improved insulin–glucagon balance. Peptide YY (PYY)-positive cells within pancreatic islets were markedly increased, whereas somatostatin (SST)-positive cells were unchanged. In the ileum, EE2 significantly reduced crypt depth and increased the number of glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP)-positive enteroendocrine cells, particularly within crypt regions, indicating enhanced incretin cell abundance. These coordinated changes across the gut and pancreas were associated with improved glucose control and reduced hyperinsulinaemia.
Conclusions:
EE2 improves metabolic control in obese diabetic mice through linked changes in pancreatic islet cell composition and intestinal incretin-producing cells. By increasing beta-cell renewal, reducing alpha-cell area, and enhancing GLP-1, GIP, and PYY expression, estrogen establishes a gut–pancreas endocrine environment that supports glucose homeostasis in obesity.
DOI: https://doi.org/10.37349/eemd.2026.101475
This article belongs to the special issue Innovative Strategies for Diabetes and Metabolic Disorders: Current and Future Directions
Background:
Diabetes mellitus (DM) refers to a group of metabolic diseases characterized by reduced insulin synthesis and release, leading to hyperglycemia, oxidative stress, and inflammation. The prevalence of DM continues to increase worldwide, primarily driven by type 2 DM (T2DM). While numerous prescription drugs are widely available for the management of T2DM, these treatments must be coupled with significant changes in diet and lifestyle to have long-term effects. This comparative review aims to summarize and critically evaluate some of the dietary antioxidant and anti-inflammatory functional foods (FFs), including bioactive compounds on glycemic regulation, oxidative stress, inflammatory markers, and other outcomes in T2DM patients.
Methods:
A comprehensive literature search was performed from June 2014 to December 2025 in Cochrane Library, Embase, Google Scholar, PubMed/Medline, and Scopus databases.
Results:
Thirty-one meta-analyses describing the effects of specific FFs on glycemic outcomes, including fasting blood glucose, HbA1c, insulin levels, insulin resistance, oxidative or inflammatory stress, and/or the doses needed to achieve these endpoints, in T2DM patients were included. Comparative analyses of the data for green tea in T2DM showed significant antioxidant effects, but conflicting data for glycemic regulation, and no significant effect on inflammatory markers. Flaxseed products significantly reduced oxidative stress and HbA1c but had no anti-inflammatory effects. Both anthocyanins and resveratrol from fruits and vegetables significantly reduced fasting blood glucose, HbA1c, as well as oxidative and inflammatory markers. Turmeric and curcumin significantly reduced fasting blood glucose, but the data for ginger were conflicted. In T2DM patients, turmeric and ginger significantly reduced markers of oxidation and inflammation.
Discussion:
Overall, improvements in diet, including the incorporation of specific FFs and exercise, along with standard treatments, may be cost-effective methods to reduce the public health impact of T2DM. Limitations included the significant heterogeneity, high risk of bias, and low to moderate quality of the randomized controlled trial (RCT).
DOI: https://doi.org/10.37349/eemd.2026.101474
Establishing remission as a clinical goal for carefully selected patients with Type 2 Diabetes Mellitus (T2DM) represents a fundamental shift from the traditional paradigm of lifelong disease management. Short disease duration, preserved C-peptide levels, and overweight or obesity are the central criteria for T2DM remission. T2DM remission may help reduce the psychological burden on patients, improve quality of life, delay disease progression, and reduce the risk of long-term complications. This consensus aims to help physicians establish standardized clinical diagnosis and treatment protocols for T2DM remission in overweight or obese patients with T2DM, and support related research to develop safer and more effective interventions. Notably, T2DM remission is conditional, reversible and population-selective, which is not universally applicable to all T2DM patients across different disease stages and healthcare settings.
Establishing remission as a clinical goal for carefully selected patients with Type 2 Diabetes Mellitus (T2DM) represents a fundamental shift from the traditional paradigm of lifelong disease management. Short disease duration, preserved C-peptide levels, and overweight or obesity are the central criteria for T2DM remission. T2DM remission may help reduce the psychological burden on patients, improve quality of life, delay disease progression, and reduce the risk of long-term complications. This consensus aims to help physicians establish standardized clinical diagnosis and treatment protocols for T2DM remission in overweight or obese patients with T2DM, and support related research to develop safer and more effective interventions. Notably, T2DM remission is conditional, reversible and population-selective, which is not universally applicable to all T2DM patients across different disease stages and healthcare settings.
DOI: https://doi.org/10.37349/eemd.2026.101473
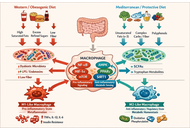
The emerging field of immunometabolism has established that the metabolic pathways governing immune cell function—glycolysis, oxidative phosphorylation, fatty acid oxidation, and amino acid metabolism—are fundamental determinants of immune responses in health and disease. This review synthesizes current evidence on how dietary inputs serve as primary environmental modulators of this immunometabolism programming. We detail the mechanisms by which macronutrients (carbohydrates, lipids, proteins), micronutrients, and specific dietary patterns (e.g., Western, Mediterranean, ketogenic) engage key nutrient-sensing pathways (mechanistic target of rapamycin [mTOR], AMP-activated protein kinase [AMPK], hypoxia-inducible factor-1α [HIF-1α], peroxisome proliferator-activated receptor [PPARs]) to rewire immune cell metabolism and influence functional phenotypes. A central role is afforded to the gut microbiota as a critical intermediary, translating diet into immunoregulatory signals, such as short-chain fatty acids. We further explore how obesogenic diets disrupt this network to fuel chronic low-grade inflammation (metaflammation), driving the pathophysiology of common metabolic diseases, including obesity, type 2 diabetes, non-alcoholic fatty liver disease (NAFLD), and atherosclerosis. Finally, we evaluate therapeutic nutritional strategies—from nutraceuticals and probiotics to the promise of precision nutrition—designed to recalibrate immunometabolism. This review underscores that diet is a powerful, modifiable lever of immunity, positioning targeted nutritional intervention as a pivotal strategy for preventing and managing metabolic disease.
The emerging field of immunometabolism has established that the metabolic pathways governing immune cell function—glycolysis, oxidative phosphorylation, fatty acid oxidation, and amino acid metabolism—are fundamental determinants of immune responses in health and disease. This review synthesizes current evidence on how dietary inputs serve as primary environmental modulators of this immunometabolism programming. We detail the mechanisms by which macronutrients (carbohydrates, lipids, proteins), micronutrients, and specific dietary patterns (e.g., Western, Mediterranean, ketogenic) engage key nutrient-sensing pathways (mechanistic target of rapamycin [mTOR], AMP-activated protein kinase [AMPK], hypoxia-inducible factor-1α [HIF-1α], peroxisome proliferator-activated receptor [PPARs]) to rewire immune cell metabolism and influence functional phenotypes. A central role is afforded to the gut microbiota as a critical intermediary, translating diet into immunoregulatory signals, such as short-chain fatty acids. We further explore how obesogenic diets disrupt this network to fuel chronic low-grade inflammation (metaflammation), driving the pathophysiology of common metabolic diseases, including obesity, type 2 diabetes, non-alcoholic fatty liver disease (NAFLD), and atherosclerosis. Finally, we evaluate therapeutic nutritional strategies—from nutraceuticals and probiotics to the promise of precision nutrition—designed to recalibrate immunometabolism. This review underscores that diet is a powerful, modifiable lever of immunity, positioning targeted nutritional intervention as a pivotal strategy for preventing and managing metabolic disease.
DOI: https://doi.org/10.37349/eemd.2026.101472
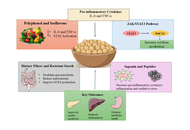
Metabolic diseases, including obesity, insulin resistance, and type 2 diabetes mellitus, are increasingly recognized as conditions characterized by chronic low-grade inflammation driven by dysregulated cytokine signaling. Persistent elevation of pro-inflammatory mediators disrupts insulin signaling and contributes to metabolic dysfunction. Nutritional interventions capable of restoring cytokine balance are emerging as promising adjunct strategies for metabolic disease management. Chickpea (Cicer arietinum L.), a widely consumed legume, is rich in polyphenols, saponins, dietary fiber, and bioactive peptides with potential immunometabolic benefits. This review critically summarizes the role of chickpea bioactives in modulating cytokine signaling networks, with particular emphasis on the IL-6-JAK-STAT3-SOCS3 axis and NF-κB pathway. Chickpea components exert antioxidant and anti-inflammatory effects, suppress pro-inflammatory cytokine production, and may improve insulin sensitivity. Additionally, their potential chemoprotective effects in obesity-associated metabolic disorders are discussed. Furthermore, this review highlights key gaps in mechanistic and translational research and proposes future directions for pathway-oriented investigations. Although current evidence supports the therapeutic potential of chickpea, further mechanistic and clinical validation is required.
Metabolic diseases, including obesity, insulin resistance, and type 2 diabetes mellitus, are increasingly recognized as conditions characterized by chronic low-grade inflammation driven by dysregulated cytokine signaling. Persistent elevation of pro-inflammatory mediators disrupts insulin signaling and contributes to metabolic dysfunction. Nutritional interventions capable of restoring cytokine balance are emerging as promising adjunct strategies for metabolic disease management. Chickpea (Cicer arietinum L.), a widely consumed legume, is rich in polyphenols, saponins, dietary fiber, and bioactive peptides with potential immunometabolic benefits. This review critically summarizes the role of chickpea bioactives in modulating cytokine signaling networks, with particular emphasis on the IL-6-JAK-STAT3-SOCS3 axis and NF-κB pathway. Chickpea components exert antioxidant and anti-inflammatory effects, suppress pro-inflammatory cytokine production, and may improve insulin sensitivity. Additionally, their potential chemoprotective effects in obesity-associated metabolic disorders are discussed. Furthermore, this review highlights key gaps in mechanistic and translational research and proposes future directions for pathway-oriented investigations. Although current evidence supports the therapeutic potential of chickpea, further mechanistic and clinical validation is required.
DOI: https://doi.org/10.37349/eemd.2026.101471
This article belongs to the special issue Role of Dysregulated Cytokine Signaling Pathways in Metabolic Disease
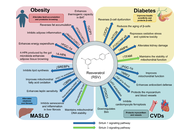
Obesity, diabetes mellitus (DM), metabolic dysfunction-associated steatotic liver disease (MASLD), and cardiovascular diseases (CVDs) share pathogenic mechanisms like oxidative stress and inflammation. Resveratrol (RSV) offers therapeutic potential by activating the sirtuin (SIRT) signaling network. This review synthesizes RSV’s pharmacological impacts on adipose, pancreatic, hepatic, and cardiovascular tissues, focusing on the AMPK/SIRT1/PGC-1α axis, PI3K/AKT pathways, and epigenetic modulations. Despite robust preclinical data, a significant translational gap exists. Clinical evidence is heterogeneous, often contradicting animal studies due to varying dosages, durations, and population characteristics. RSV acts as a pan-SIRT activator, though its precise SIRT1 activation mechanism, direct or via NAD+ modulation, remains debated. In obesity, RSV promotes adipose beiging and thermogenesis, yet clinical weight loss is modest. For DM, it preserves β-cell function and improves insulin sensitivity, primarily benefiting diabetic populations with variable glycemic outcomes. In MASLD, RSV ameliorates steatosis and fibrosis in models, but large-scale human trials confirming histological benefits are lacking. Regarding CVDs, RSV protects against endothelial dysfunction and inflammation, showing minor improvements in biomarkers like blood pressure, though hard endpoints need validation. Major limitations hinder clinical efficacy, such as poor oral bioavailability, rapid metabolism, and significant interindividual pharmacokinetic variability. The lack of standardized formulations further complicates systemic exposure. Nevertheless, the RSV-SIRT axis remains a unified metabolic and epigenetic modulator, stabilizing cellular microenvironments across organ systems. It represents a promising target for complex metabolic syndromes. Future research should prioritize overcoming bioavailability challenges through novel delivery systems and investigating synergistic combinatorial therapies to bridge the gap between preclinical promise and clinical reality.
Obesity, diabetes mellitus (DM), metabolic dysfunction-associated steatotic liver disease (MASLD), and cardiovascular diseases (CVDs) share pathogenic mechanisms like oxidative stress and inflammation. Resveratrol (RSV) offers therapeutic potential by activating the sirtuin (SIRT) signaling network. This review synthesizes RSV’s pharmacological impacts on adipose, pancreatic, hepatic, and cardiovascular tissues, focusing on the AMPK/SIRT1/PGC-1α axis, PI3K/AKT pathways, and epigenetic modulations. Despite robust preclinical data, a significant translational gap exists. Clinical evidence is heterogeneous, often contradicting animal studies due to varying dosages, durations, and population characteristics. RSV acts as a pan-SIRT activator, though its precise SIRT1 activation mechanism, direct or via NAD+ modulation, remains debated. In obesity, RSV promotes adipose beiging and thermogenesis, yet clinical weight loss is modest. For DM, it preserves β-cell function and improves insulin sensitivity, primarily benefiting diabetic populations with variable glycemic outcomes. In MASLD, RSV ameliorates steatosis and fibrosis in models, but large-scale human trials confirming histological benefits are lacking. Regarding CVDs, RSV protects against endothelial dysfunction and inflammation, showing minor improvements in biomarkers like blood pressure, though hard endpoints need validation. Major limitations hinder clinical efficacy, such as poor oral bioavailability, rapid metabolism, and significant interindividual pharmacokinetic variability. The lack of standardized formulations further complicates systemic exposure. Nevertheless, the RSV-SIRT axis remains a unified metabolic and epigenetic modulator, stabilizing cellular microenvironments across organ systems. It represents a promising target for complex metabolic syndromes. Future research should prioritize overcoming bioavailability challenges through novel delivery systems and investigating synergistic combinatorial therapies to bridge the gap between preclinical promise and clinical reality.
DOI: https://doi.org/10.37349/eemd.2026.101470
Aim:
The aim of this study was to compare the effects of high-intensity interval training (HIIT) and concurrent training (CONC) on body composition and metabolic profile in postmenopausal women.
Methods:
Forty-five postmenopausal women with overweight or obesity (50–65 years) were randomly assigned to one of three groups: HIIT group, CONC group, or control group (CG). All groups underwent a 12-week intervention, consisting of three training sessions per week, scheduled on alternate days. All dependent variables (body composition, lipid, or glycemic markers) were assessed before and after a 12-week intervention period.
Results:
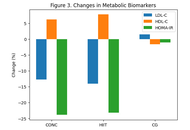
The CONC and HIIT groups showed anthropometric improvements compared to the CG. In this regard, CONC and HIIT significantly (P < 0.05) reduced their body weight and body mass index (BMI) compared with the CG. This reduction was due to a decrease in fat mass, mainly in the abdominal area, as reflected by the reduction in the waist-to-hip ratio. Participants in the CONC group showed greater reductions in body weight, BMI, and body fat percentage compared with the HIIT group, while both exercise interventions produced similar improvements in metabolic biomarkers. Regarding circulating parameters, CONC and HIIT significantly (P < 0.05) reduced circulating triglycerides, total cholesterol, and LDL-cholesterol, which resulted in a decrease in the atherogenic index of plasma (AIP, calculated as log[TG/HDL-C]) compared with CG. Blood glucose and insulin levels also decreased significantly (P < 0.05) in CONC and HIIT compared with CG, with a consequent reduction in the homeostatic model assessment-insulin resistance (HOMA-IR).
Conclusions:
A 12-week program of HIIT or CONC training represents an effective strategy for improving body fat reduction and metabolic profile in sedentary postmenopausal women with overweight or obesity [ClinicalTrials.gov, identifier (ID NCT07302191)].
DOI: https://doi.org/10.37349/eemd.2026.101469
This article belongs to the special issue Metabolic Syndrome in Menopause
The global rise in consumption of added sugars and confectionery parallels the increasing prevalence of obesity, metabolic dysfunction, and male hypogonadism. Testosterone is essential for male reproductive, metabolic, and cardiovascular health, and growing evidence indicates that excessive sugar intake may disrupt hormonal regulation. This narrative review synthesizes data from human observational and interventional studies and experimental animal models to evaluate the effects of sugar consumption on testosterone homeostasis and male reproductive outcomes. Acute glucose ingestion is associated with hyperinsulinemia and inflammatory cytokine release, which may contribute to transient reductions in circulating testosterone of approximately 20–30%, although findings vary across populations and study designs. Chronic high-sugar intake, particularly from sugar-sweetened beverages, promotes oxidative stress, adiposity, insulin resistance, and leptin dysregulation, which may collectively impair Leydig cell steroidogenesis and contribute to testosterone suppression. Animal studies consistently demonstrate testicular structural damage, downregulation of steroidogenic enzymes, and impaired spermatogenesis under high-sugar dietary conditions. Epidemiological studies associate frequent intake of sugar-sweetened beverages and confectionery with lower testosterone levels and poorer semen parameters. Emerging evidence suggests partial reversibility with dietary interventions emphasizing reduced sugar intake and increased antioxidant consumption. Overall, current data support a biologically plausible link between excessive sugar intake and impaired testosterone regulation, underscoring the need for longitudinal studies and public health strategies targeting added sugar reduction.
The global rise in consumption of added sugars and confectionery parallels the increasing prevalence of obesity, metabolic dysfunction, and male hypogonadism. Testosterone is essential for male reproductive, metabolic, and cardiovascular health, and growing evidence indicates that excessive sugar intake may disrupt hormonal regulation. This narrative review synthesizes data from human observational and interventional studies and experimental animal models to evaluate the effects of sugar consumption on testosterone homeostasis and male reproductive outcomes. Acute glucose ingestion is associated with hyperinsulinemia and inflammatory cytokine release, which may contribute to transient reductions in circulating testosterone of approximately 20–30%, although findings vary across populations and study designs. Chronic high-sugar intake, particularly from sugar-sweetened beverages, promotes oxidative stress, adiposity, insulin resistance, and leptin dysregulation, which may collectively impair Leydig cell steroidogenesis and contribute to testosterone suppression. Animal studies consistently demonstrate testicular structural damage, downregulation of steroidogenic enzymes, and impaired spermatogenesis under high-sugar dietary conditions. Epidemiological studies associate frequent intake of sugar-sweetened beverages and confectionery with lower testosterone levels and poorer semen parameters. Emerging evidence suggests partial reversibility with dietary interventions emphasizing reduced sugar intake and increased antioxidant consumption. Overall, current data support a biologically plausible link between excessive sugar intake and impaired testosterone regulation, underscoring the need for longitudinal studies and public health strategies targeting added sugar reduction.
DOI: https://doi.org/10.37349/eemd.2026.101468
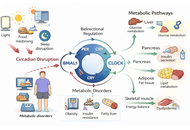
Circadian rhythms are intrinsic 24-hour cycles that coordinate key metabolic processes, including glucose homeostasis, lipid metabolism, and energy expenditure. Disruption of these rhythms, due to sleep disturbances, shift work, or irregular feeding schedules, contributes to the development of obesity, insulin resistance, and dyslipidemia. Core clock genes, including circadian locomotor output cycles kaput (CLOCK), brain and muscle ARNT-like 1 (BMAL1), period gene (PER), and cryptochrome (CRY), play a central role in orchestrating these metabolic pathways. Chronotherapy, aligning lifestyle, behavioral, and pharmacologic interventions with circadian timing, represents a promising, yet underexplored, strategy for metabolic disease management. Evidence suggests that interventions such as time-restricted feeding, light therapy, pharmacologic modulators of clock gene expression, and wearable technology can improve glucose control, lipid profiles, and body weight. This review synthesizes current knowledge on the molecular regulation of metabolism by circadian clocks, elucidates mechanistic links between rhythm disruption and metabolic dysfunction, and explores translational strategies to restore circadian homeostasis. By targeting circadian rhythms, personalized and cost-effective interventions can be developed to mitigate the global burden of metabolic disorders. Future research should focus on large-scale clinical trials, precision chronotherapy, and integration of wearable devices to optimize the timing of interventions, ultimately enhancing treatment efficacy and long-term metabolic health.
Circadian rhythms are intrinsic 24-hour cycles that coordinate key metabolic processes, including glucose homeostasis, lipid metabolism, and energy expenditure. Disruption of these rhythms, due to sleep disturbances, shift work, or irregular feeding schedules, contributes to the development of obesity, insulin resistance, and dyslipidemia. Core clock genes, including circadian locomotor output cycles kaput (CLOCK), brain and muscle ARNT-like 1 (BMAL1), period gene (PER), and cryptochrome (CRY), play a central role in orchestrating these metabolic pathways. Chronotherapy, aligning lifestyle, behavioral, and pharmacologic interventions with circadian timing, represents a promising, yet underexplored, strategy for metabolic disease management. Evidence suggests that interventions such as time-restricted feeding, light therapy, pharmacologic modulators of clock gene expression, and wearable technology can improve glucose control, lipid profiles, and body weight. This review synthesizes current knowledge on the molecular regulation of metabolism by circadian clocks, elucidates mechanistic links between rhythm disruption and metabolic dysfunction, and explores translational strategies to restore circadian homeostasis. By targeting circadian rhythms, personalized and cost-effective interventions can be developed to mitigate the global burden of metabolic disorders. Future research should focus on large-scale clinical trials, precision chronotherapy, and integration of wearable devices to optimize the timing of interventions, ultimately enhancing treatment efficacy and long-term metabolic health.
DOI: https://doi.org/10.37349/eemd.2026.101467
Osteoarthritis (OA) is the most prevalent form of arthritis and a leading cause of disability worldwide. Epidemiological studies indicate that its global prevalence is rising, particularly among women, who often experience more severe disease than men. This sex disparity is most pronounced around menopause and is influenced by female-specific biological and hormonal factors, joint morphology, reproductive history, and sex-specific comorbidities that contribute to disease onset and progression. A mechanistic understanding of these factors is essential to identify individuals at risk, implement preventive strategies, enable early diagnosis, and mitigate complications, ultimately preserving function and quality of life. This review focuses on the determinants underlying the higher incidence and severity of OA in women, highlighting the interplay between hormonal changes, anatomy, and systemic factors.
Osteoarthritis (OA) is the most prevalent form of arthritis and a leading cause of disability worldwide. Epidemiological studies indicate that its global prevalence is rising, particularly among women, who often experience more severe disease than men. This sex disparity is most pronounced around menopause and is influenced by female-specific biological and hormonal factors, joint morphology, reproductive history, and sex-specific comorbidities that contribute to disease onset and progression. A mechanistic understanding of these factors is essential to identify individuals at risk, implement preventive strategies, enable early diagnosis, and mitigate complications, ultimately preserving function and quality of life. This review focuses on the determinants underlying the higher incidence and severity of OA in women, highlighting the interplay between hormonal changes, anatomy, and systemic factors.
DOI: https://doi.org/10.37349/eemd.2026.101466
Epiploic appendagitis is a rare, self-limiting inflammatory condition of the colonic epiploic appendages. It commonly presents with acute focal lower quadrant abdominal pain and may mimic appendicitis, colitis, or diverticulitis. Rapid weight loss has been proposed as a potential predisposing factor, although clinical evidence remains limited. This report describes a case of epiploic appendagitis occurring in temporal association with substantial and relatively rapid weight reduction during treatment with tirzepatide, a dual glucose-dependent insulinotropic polypeptide (GIP) and glucagon-like peptide-1 (GLP-1) receptor agonist. A 45-year-old individual with a history of obesity, prediabetes, hypertension, hypothyroidism, and inflammatory bowel syndrome presented to primary care with right lower quadrant abdominal pain. Initial evaluation attributed symptoms to constipation; however, pain progressed despite management. Computed tomography (CT) of the abdomen and pelvis with contrast was obtained due to concern for appendicitis and demonstrated imaging findings consistent with epiploic appendagitis localized to the cecum. The patient had experienced clinically significant and relatively rapid weight loss during tirzepatide dose escalation prior to presentation. Management was conservative with nonsteroidal anti-inflammatory drugs and supportive care, without surgical intervention. Symptoms resolved completely within two weeks, and tirzepatide therapy was continued without recurrence. Although epiploic appendagitis has not been identified as a safety signal in randomized trials, systematic reviews, or pharmacovigilance analyses of GLP-1/GIP receptor agonists, this case highlights epiploic appendagitis as an important diagnostic consideration in patients presenting with focal abdominal pain during periods of substantial weight loss. Awareness of this uncommon condition may help prevent misdiagnosis and unnecessary interventions as pharmacologic weight loss therapies become more widely used.
Epiploic appendagitis is a rare, self-limiting inflammatory condition of the colonic epiploic appendages. It commonly presents with acute focal lower quadrant abdominal pain and may mimic appendicitis, colitis, or diverticulitis. Rapid weight loss has been proposed as a potential predisposing factor, although clinical evidence remains limited. This report describes a case of epiploic appendagitis occurring in temporal association with substantial and relatively rapid weight reduction during treatment with tirzepatide, a dual glucose-dependent insulinotropic polypeptide (GIP) and glucagon-like peptide-1 (GLP-1) receptor agonist. A 45-year-old individual with a history of obesity, prediabetes, hypertension, hypothyroidism, and inflammatory bowel syndrome presented to primary care with right lower quadrant abdominal pain. Initial evaluation attributed symptoms to constipation; however, pain progressed despite management. Computed tomography (CT) of the abdomen and pelvis with contrast was obtained due to concern for appendicitis and demonstrated imaging findings consistent with epiploic appendagitis localized to the cecum. The patient had experienced clinically significant and relatively rapid weight loss during tirzepatide dose escalation prior to presentation. Management was conservative with nonsteroidal anti-inflammatory drugs and supportive care, without surgical intervention. Symptoms resolved completely within two weeks, and tirzepatide therapy was continued without recurrence. Although epiploic appendagitis has not been identified as a safety signal in randomized trials, systematic reviews, or pharmacovigilance analyses of GLP-1/GIP receptor agonists, this case highlights epiploic appendagitis as an important diagnostic consideration in patients presenting with focal abdominal pain during periods of substantial weight loss. Awareness of this uncommon condition may help prevent misdiagnosis and unnecessary interventions as pharmacologic weight loss therapies become more widely used.
DOI: https://doi.org/10.37349/eemd.2026.101465
