




 Previous
Of the approximately 40 million people living with human immunodeficiency virus (HIV) globally as of 2022, a clinically significant subset harbours multidrug-resistant (MDR) HIV-1, leaving them with few viable antiretroviral options. Ibalizumab (Trogarzo), a recombinant humanised IgG4 monoclonal antibody, received FDA approval in March 2018 as the first monoclonal antibody for HIV-1 therapy and the first agent of a novel mechanistic class approved in over a decade. This review critically appraises ibalizumab across its discovery, mechanism of action, pharmacology, clinical trial evidence, safety profile, special populations, and access considerations. A narrative review of peer-reviewed literature was conducted using PubMed and Embase, supplemented by data from ClinicalTrials.gov, FDA and European Medicines Agency (EMA) regulatory documents, and relevant conference proceedings published up to March 2026. Ibalizumab binds domain 2 (D2) of the extracellular CD4 receptor, sterically blocking post-attachment conformational changes required for co-receptor engagement without impairing MHC class II immune signalling. In the pivotal Phase III TMB-301 trial, 83% of heavily treatment-experienced adults achieved a clinically meaningful viral load reduction at week 24, while extended-access studies demonstrated durable virological suppression and sustained immunological recovery. The drug is generally well tolerated, with diarrhoea, headache, and nausea being the most frequently reported adverse events. Resistance develops rapidly when ibalizumab is used as monotherapy, underscoring the necessity of combining it with an optimised background antiretroviral regimen. Ibalizumab represents a genuine therapeutic advance for patients with MDR HIV-1 who have exhausted conventional regimens. Its unique mechanism, established efficacy, and favourable safety profile make it an indispensable salvage therapy component. Key barriers to broader uptake include intravenous administration, biweekly clinic attendance, high cost, and limited availability in resource-constrained settings. Long-acting formulations and bispecific antibody strategies offer promise for expanding its clinical reach.
Of the approximately 40 million people living with human immunodeficiency virus (HIV) globally as of 2022, a clinically significant subset harbours multidrug-resistant (MDR) HIV-1, leaving them with few viable antiretroviral options. Ibalizumab (Trogarzo), a recombinant humanised IgG4 monoclonal antibody, received FDA approval in March 2018 as the first monoclonal antibody for HIV-1 therapy and the first agent of a novel mechanistic class approved in over a decade. This review critically appraises ibalizumab across its discovery, mechanism of action, pharmacology, clinical trial evidence, safety profile, special populations, and access considerations. A narrative review of peer-reviewed literature was conducted using PubMed and Embase, supplemented by data from ClinicalTrials.gov, FDA and European Medicines Agency (EMA) regulatory documents, and relevant conference proceedings published up to March 2026. Ibalizumab binds domain 2 (D2) of the extracellular CD4 receptor, sterically blocking post-attachment conformational changes required for co-receptor engagement without impairing MHC class II immune signalling. In the pivotal Phase III TMB-301 trial, 83% of heavily treatment-experienced adults achieved a clinically meaningful viral load reduction at week 24, while extended-access studies demonstrated durable virological suppression and sustained immunological recovery. The drug is generally well tolerated, with diarrhoea, headache, and nausea being the most frequently reported adverse events. Resistance develops rapidly when ibalizumab is used as monotherapy, underscoring the necessity of combining it with an optimised background antiretroviral regimen. Ibalizumab represents a genuine therapeutic advance for patients with MDR HIV-1 who have exhausted conventional regimens. Its unique mechanism, established efficacy, and favourable safety profile make it an indispensable salvage therapy component. Key barriers to broader uptake include intravenous administration, biweekly clinic attendance, high cost, and limited availability in resource-constrained settings. Long-acting formulations and bispecific antibody strategies offer promise for expanding its clinical reach.
DOI: https://doi.org/10.37349/emed.2026.1001429
This article belongs to the special issue Global Perspectives on the Clinical Diagnosis, Treatment, and Functional Cure of HIV Infection in the Post-ART Era


Aim:
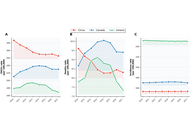
Chronic kidney disease (CKD) is a major global health burden. Emerging evidence links water quality with kidney outcomes, but ecological panel evidence remains limited and context dependent. We examined hypothesis-generating associations between surface water quality indicators and CKD burden in China, Canada, and Ireland during 2010–2017.
Methods:
We integrated age-standardized CKD rates from the Institute for Health Metrics and Evaluation (IHME) GBD Results Tool (DALYs, deaths, incidence, prevalence, years lived with disability (YLDs), and years of life lost (YLLs) per 100,000 population; country-year estimates were restricted to 2010–2017) for China, Canada, and Ireland with 284,965 surface water quality observations. The downloaded IHME citation identified the release as Global Burden of Disease Study 2023 (GBD 2023) Results, while the estimates used in this analysis were limited to 2010–2017. Country-specific ordinary least-squares regression was used for the primary analysis; random-effects meta-analysis was used only to summarize country-specific estimates, and restricted cubic spline (RCS) analyses explored non-linear patterns. Standardized beta coefficients were added to improve comparability across countries and water-quality scales.
Results:
CKD DALYs rates declined in China (–13.5%) and Ireland (–5.4%) but rose in Canada (+9.0%). In country-specific models, nitrate was inversely associated with CKD DALYs (beta = –12.10; 95% CI: –19.80 to –4.41; P = 0.002; standardized beta = –0.25) and deaths (beta = –0.94; P = 0.006; standardized beta = –0.26) in Ireland. Total nitrogen was inversely associated with CKD incidence in Canada (beta = –0.63; P = 0.006; standardized beta = –0.20). These associations occurred over narrow exposure ranges and should be interpreted cautiously. Random-effects pooled estimates were not statistically significant, and heterogeneity across outcomes ranged from none to substantial (I2: 0–78.4%).
Conclusions:
Surface water nitrate and nitrogen showed inconsistent, country-specific associations with CKD burden and did not yield robust pooled estimates. These hypothesis-generating ecological findings underscore the need for individual-level studies with measured drinking-water exposure, harmonized diagnostic information, and latency-aware designs.
DOI: https://doi.org/10.37349/emed.2026.1001428
Aim:
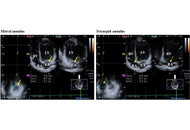
Hypocoagulability and associated alterations in myocardial mechanics seen in hemophilia could theoretically impact valvular geometry. Therefore, the purpose of the present study was to characterize mitral and tricuspid annular dimensions and functions in patients with hemophilia via 3D speckle-tracking echocardiography.
Methods:
Of the 17 hemophilia patients originally assessed, four were excluded due to inadequate image quality. The remaining cohort consisted of 13 males with hemophilia (mean age: 40.8 ± 16.3 years; 11 with hemophilia A and 2 with hemophilia B). Thirty age- and gender-matched healthy males (mean age: 40.4 ± 9.2 years) served as the control group.
Results:
Hemophilia patients presented with significant dilation of end-diastolic and end-systolic mitral annulus (MA) dimensions (diameter, area, and perimeter), leading to a reduction in MA fractional area change (MAFAC) compared with control subjects. In contrast, among the tricuspid annulus (TA) parameters, dilation was confined to end-diastolic values, while end-systolic dimensions were preserved.
Conclusions:
Dilated MA, along with its functional deterioration, is present in patients with hemophilia compared to matched controls. TA dilation seems less pronounced.
DOI: https://doi.org/10.37349/emed.2026.1001427
This article belongs to the special issue Assessment of Atrial and Ventricular Volumes and Functional Properties: Novel Insights
Aim:
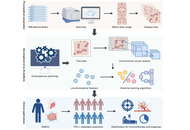
To investigate interobserver variability in programmed cell death ligand 1 (PD-L1) combined positive score (CPS) assessment in head and neck squamous cell carcinoma (HNSCC) and to develop an artificial intelligence (AI)-based model for predicting PD-L1 expression and patient prognosis from hematoxylin and eosin (H&E)-stained slides.
Methods:
Fifty HNSCC specimens were independently evaluated for PD-L1 by pathologists with different experience levels. Agreement was assessed using Fleiss’ and Cohen’s κ. Whole-slide images were processed into tiles for deep learning using DenseNet121. Tile-level features were integrated via two machine learning pipelines to construct whole-slide prediction models. Multiple algorithms were tested, with performance evaluated in validation and testing cohorts. Prognostic value was analyzed using AI-derived risk stratification.
Results:
Interobserver agreement was low (Fleiss’ κ = 0.34), indicating substantial variability in CPS assessment. DenseNet121 achieved moderate predictive performance (AUC 0.641 in validation, 0.616 in testing). AI models significantly improved prediction accuracy, with logistic regression demonstrating the best performance (AUC 0.900 in validation, 0.851 in testing). AI-derived prediction scores effectively stratified overall survival, with multiple models showing significant prognostic discrimination (P < 0.05).
Conclusions:
AI models integrating deep learning and machine learning can accurately predict PD-L1 expression and stratify prognosis in HNSCC, outperforming tile-level deep learning alone.
DOI: https://doi.org/10.37349/emed.2026.1001426
Background:
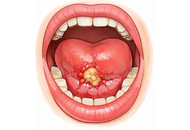
Ankyloglossia is a congenital condition characterized by restricted tongue mobility, which may influence oral functions such as speech, swallowing, and oral motor coordination. This systematic review aimed to evaluate oral functional outcomes following surgical and/or myofunctional interventions in individuals with lingual hypomobility. A secondary aim was to assess variability and consistency of functional improvements across different therapeutic approaches.
Methods:
This systematic review was conducted in accordance with PRISMA guidelines. PubMed, Scopus, and Web of Science were searched between 15 June 2025 and 10 August 2025. Eligible clinical studies (randomized controlled trials, cohort studies, and case series/reports) evaluated lingual frenotomy, frenulectomy, or frenuloplasty, alone or combined with orofacial myofunctional therapy, and reported oral functional outcomes, including tongue mobility, oral posture, swallowing-related tasks, neuromuscular measures, and patient-reported function. Risk of bias was assessed using validated tools (ROBINS-I and RoB 2). Due to heterogeneity in study design and outcome measures, a narrative synthesis was performed.
Results:
Ten studies involving more than 1,300 participants across pediatric, adolescent, and adult populations were included. The evidence comprised randomized controlled trials, observational studies, and case series. Surgical intervention alone was primarily associated with immediate anatomical and mobility-related improvements. In contrast, combined surgical and myofunctional approaches were more consistently associated with improvements in functional outcomes, including tongue mobility, resting posture, and swallowing-related functions. However, the consistency of these improvements varied across age groups, intervention protocols, and outcome assessment methods. Risk of bias was variable and frequently influenced by heterogeneous diagnostic criteria, nonstandardized interventions, and nonuniform outcome measures.
Discussion:
Combined surgical and myofunctional interventions appear to be associated with improvements in oral functional outcomes compared with stand-alone approaches. However, due to substantial methodological heterogeneity and limited high-quality evidence, these findings should be interpreted with caution and are primarily applicable to the specific functional domains evaluated.
DOI: https://doi.org/10.37349/emed.2026.1001425
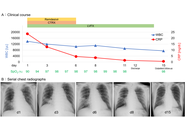
Bacterial co-infection in patients with coronavirus disease 2019 (COVID-19) can complicate diagnosis because of overlapping clinicoradiologic findings among pathogens. We report a case of suspected triple co-infection with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), Legionella pneumophila (L. pneumophila), and Streptococcus pneumoniae (S. pneumoniae) after hot-spring travel in a post-splenectomy patient. A man in his 70s with a history of subtotal esophagectomy and concomitant splenectomy for esophageal cancer was admitted with fever, worsening productive cough, and altered sensorium. He had recently traveled to a hot spring with a group that included his wife, who also developed a fever and was diagnosed with COVID-19. On admission, results of urinary antigen tests for L. pneumophila and S. pneumoniae were positive, a SARS-CoV-2 nucleic acid amplification test was positive, and sputum culture yielded S. pneumoniae. Chest computed tomography revealed multifocal bilateral ground-glass opacities, small bilateral pleural effusions, and relatively well-defined right middle-lobe consolidation with air bronchograms in a peribronchovascular distribution. These microbiological and radiological findings supported a suspected triple co-infection rather than COVID-19 alone. Treatment with remdesivir, ceftriaxone, and levofloxacin was initiated, and the patient’s condition improved, with better oxygenation and decreased inflammatory markers. Remdesivir and ceftriaxone were discontinued after 5 days, whereas levofloxacin was continued for 14 days. Follow-up imaging revealed marked improvement, and the patient was discharged. Public health investigations did not detect Legionella at the hot-spring facility or identify any additional linked cases. This case highlights the importance of prompt pathogen-directed evaluation when COVID-19 pneumonia is accompanied by a relevant exposure history, host risk factors, and atypical imaging findings.
Bacterial co-infection in patients with coronavirus disease 2019 (COVID-19) can complicate diagnosis because of overlapping clinicoradiologic findings among pathogens. We report a case of suspected triple co-infection with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), Legionella pneumophila (L. pneumophila), and Streptococcus pneumoniae (S. pneumoniae) after hot-spring travel in a post-splenectomy patient. A man in his 70s with a history of subtotal esophagectomy and concomitant splenectomy for esophageal cancer was admitted with fever, worsening productive cough, and altered sensorium. He had recently traveled to a hot spring with a group that included his wife, who also developed a fever and was diagnosed with COVID-19. On admission, results of urinary antigen tests for L. pneumophila and S. pneumoniae were positive, a SARS-CoV-2 nucleic acid amplification test was positive, and sputum culture yielded S. pneumoniae. Chest computed tomography revealed multifocal bilateral ground-glass opacities, small bilateral pleural effusions, and relatively well-defined right middle-lobe consolidation with air bronchograms in a peribronchovascular distribution. These microbiological and radiological findings supported a suspected triple co-infection rather than COVID-19 alone. Treatment with remdesivir, ceftriaxone, and levofloxacin was initiated, and the patient’s condition improved, with better oxygenation and decreased inflammatory markers. Remdesivir and ceftriaxone were discontinued after 5 days, whereas levofloxacin was continued for 14 days. Follow-up imaging revealed marked improvement, and the patient was discharged. Public health investigations did not detect Legionella at the hot-spring facility or identify any additional linked cases. This case highlights the importance of prompt pathogen-directed evaluation when COVID-19 pneumonia is accompanied by a relevant exposure history, host risk factors, and atypical imaging findings.
DOI: https://doi.org/10.37349/emed.2026.1001424
This article belongs to the special issue Legionellosis: From Environmental Exposure to Clinical Disease
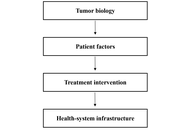
Breast cancer survival is shaped by a complex interaction of tumor-specific, biological, and patient-related factors. Stage at diagnosis remains the strongest predictor of outcome. Tumor size, nodal involvement, and histologic grade further aid in prognostic prediction by reflecting the biological aggressiveness of the disease. Since the early 2000s, molecular characteristics gained importance in risk stratification. Hormone receptor-positive cancers generally respond well to endocrine therapy, while HER2-positive tumors, once associated with poor outcomes, now benefit from targeted therapy. Newer agents and combinations such as CDK4/6 and PI3K/AKT/mTOR inhibitors are being investigated recently. Patient factors, including age, comorbidities, and overall health, also influence outcome and treatment tolerance. Cardiovascular toxicity from chemotherapy and radiotherapy has become an important consideration, particularly in the elderly. Although modern radiotherapy techniques have reduced cardiac risks, long-term cardiovascular mortality remains a competing cause of death in many survivors. Studies comparing breast-conserving therapy with mastectomy suggest improved overall survival with the former, partly due to reduced treatment morbidity. Early detection through mammography, ultrasound, and awareness campaigns greatly improves survival, yet access remains unequal in low-resource settings. Strengthening healthcare systems, tailoring treatments, expanding multidisciplinary care and improving public education are essential. Affordable personalized therapies, better infrastructure, and international collaboration can reduce disparities and enhance global breast cancer outcomes. Our international team researched literature information as well as summarizing up-to-date opinions from global experts, including those with limited resources and war-torn regions.
Breast cancer survival is shaped by a complex interaction of tumor-specific, biological, and patient-related factors. Stage at diagnosis remains the strongest predictor of outcome. Tumor size, nodal involvement, and histologic grade further aid in prognostic prediction by reflecting the biological aggressiveness of the disease. Since the early 2000s, molecular characteristics gained importance in risk stratification. Hormone receptor-positive cancers generally respond well to endocrine therapy, while HER2-positive tumors, once associated with poor outcomes, now benefit from targeted therapy. Newer agents and combinations such as CDK4/6 and PI3K/AKT/mTOR inhibitors are being investigated recently. Patient factors, including age, comorbidities, and overall health, also influence outcome and treatment tolerance. Cardiovascular toxicity from chemotherapy and radiotherapy has become an important consideration, particularly in the elderly. Although modern radiotherapy techniques have reduced cardiac risks, long-term cardiovascular mortality remains a competing cause of death in many survivors. Studies comparing breast-conserving therapy with mastectomy suggest improved overall survival with the former, partly due to reduced treatment morbidity. Early detection through mammography, ultrasound, and awareness campaigns greatly improves survival, yet access remains unequal in low-resource settings. Strengthening healthcare systems, tailoring treatments, expanding multidisciplinary care and improving public education are essential. Affordable personalized therapies, better infrastructure, and international collaboration can reduce disparities and enhance global breast cancer outcomes. Our international team researched literature information as well as summarizing up-to-date opinions from global experts, including those with limited resources and war-torn regions.
DOI: https://doi.org/10.37349/emed.2026.1001423
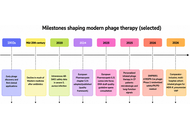
Antimicrobial resistance has intensified the search for alternatives to conventional antibiotics, particularly against multidrug-resistant bacterial pathogens that increasingly compromise treatment outcomes in hospitals and community settings. This narrative review examines bacteriophage therapy as an alternative for combating multidrug-resistant bacteria. Recent literature is discussed thematically, with emphasis on original studies, clinical datasets, translational experiments, and regulatory documents. The current evidence base consists predominantly of compassionate-use reports, small cohorts, and early-phase trials, including CRISPR-enhanced and inhaled phage platforms, which report safety observations, compartment-specific responses, and microbiome effects in individual studies. Mechanistic considerations discussed in the review include route-specific delivery, phage–host ecological interactions, resistance trade-offs, and phage–antibiotic synergy. While microbiological and clinical responses have been reported in individual studies, no confirmatory randomized trial has demonstrated clinical efficacy for any phage therapy indication. Manufacturing, standardization, and regulatory pathways for scaled deployment also remain unresolved. Regulatory developments in Europe, the United Kingdom, the United States, and Australia remain heterogeneous and predominantly access-based or compassionate-use-based rather than approval-based. Specific technical challenges include incomplete standardization of susceptibility testing and the need for robust monitoring of immune neutralization, endotoxin burden, and long-term ecological effects. Routine clinical adoption of phage therapy will ultimately depend on outcomes of adequately powered confirmatory trials, alongside resolution of manufacturing, regulatory, and standardization challenges.
Antimicrobial resistance has intensified the search for alternatives to conventional antibiotics, particularly against multidrug-resistant bacterial pathogens that increasingly compromise treatment outcomes in hospitals and community settings. This narrative review examines bacteriophage therapy as an alternative for combating multidrug-resistant bacteria. Recent literature is discussed thematically, with emphasis on original studies, clinical datasets, translational experiments, and regulatory documents. The current evidence base consists predominantly of compassionate-use reports, small cohorts, and early-phase trials, including CRISPR-enhanced and inhaled phage platforms, which report safety observations, compartment-specific responses, and microbiome effects in individual studies. Mechanistic considerations discussed in the review include route-specific delivery, phage–host ecological interactions, resistance trade-offs, and phage–antibiotic synergy. While microbiological and clinical responses have been reported in individual studies, no confirmatory randomized trial has demonstrated clinical efficacy for any phage therapy indication. Manufacturing, standardization, and regulatory pathways for scaled deployment also remain unresolved. Regulatory developments in Europe, the United Kingdom, the United States, and Australia remain heterogeneous and predominantly access-based or compassionate-use-based rather than approval-based. Specific technical challenges include incomplete standardization of susceptibility testing and the need for robust monitoring of immune neutralization, endotoxin burden, and long-term ecological effects. Routine clinical adoption of phage therapy will ultimately depend on outcomes of adequately powered confirmatory trials, alongside resolution of manufacturing, regulatory, and standardization challenges.
DOI: https://doi.org/10.37349/emed.2026.1001422
Aim:
Hypertension and obesity frequently coexist and increase cardiovascular risk through vascular dysfunction, autonomic imbalance, and metabolic dysregulation. This study investigated the effects of an 8-week mat Pilates program on body composition, blood pressure, vascular function, autonomic nervous system activity, and health-related physical fitness in obese men with elevated or stage 1 hypertension.
Methods:
Twenty-three men with elevated or stage 1 hypertension and a body mass index (BMI) ≥ 25 kg/m2 were initially recruited and randomly assigned to a control group (CON) or an experimental group (EXP). After withdrawal or loss to follow-up, 20 participants completed the study and were included in the final analysis (CON, n = 10; EXP, n = 10). The EXP performed mat Pilates three times per week for eight weeks, while CON maintained their usual lifestyle. Outcomes were assessed before and after the intervention.
Results:
Significant group × time interaction effects were observed for body weight, BMI, fat mass, hemodynamic variables, vascular indices, selected heart rate variability measures, and health-related physical fitness. Lean body mass and percent body fat improved significantly within the EXP, although the corresponding interaction effects were not significant. Overall, the EXP showed more favorable changes than the CON in several cardiometabolic and fitness-related outcomes.
Conclusions:
An 8-week mat Pilates program was associated with favorable changes in body composition, blood pressure and vascular function, autonomic nervous system indices, and health-related physical fitness in obese men with elevated or stage 1 hypertension. However, because body weight and fat mass also decreased and the sample size was small, these findings should be interpreted cautiously. This study cannot determine whether the changes resulted from the Pilates intervention itself, concurrent body composition changes, or their combined effects. Trial registration: KCT0010502; https://cris.nih.go.kr/cris/index/index.do.
DOI: https://doi.org/10.37349/emed.2026.1001421
Oxidative stress—an imbalance between reactive oxygen/nitrogen species and antioxidant defenses—contributes not only to the developmental origins of asthma but also to poor control, airway remodeling, and corticosteroid-resistant inflammation in children. Persistent oxidant exposure, nutritional insufficiency, and mitochondrial dysfunction sustain redox imbalance in pediatric asthma, suggesting potential roles for environmental, dietary, and nutraceutical strategies—defined here as natural bioactive compounds providing health benefits beyond basic nutrition, including polyphenols such as curcumin, quercetin, and resveratrol, and essential minerals such as zinc and selenium—that complement standard therapy. To summarize evidence on preventive and therapeutic approaches that modulate oxidative stress in pediatric asthma, focusing on environmental control, antioxidant-rich dietary patterns, single and multi-component nutraceuticals, and mitochondria-targeted interventions. A structured review of PubMed, Scopus, and Embase (1995–2025) identified peer-reviewed English-language epidemiologic studies, mechanistic models, and clinical trials evaluating oxidative stress, antioxidant status, and asthma outcomes in children and, when relevant, adults. Reference lists of major reviews were screened to identify additional studies. Interventions that reduce exposure to air pollutants and tobacco smoke, combined with antioxidant-rich diets such as high fruit/vegetable intake and Mediterranean-style patterns, are consistently associated with improved lung function, fewer symptoms, and reduced inflammation. Clinical trials of single antioxidants (vitamin D, vitamin E, zinc, selenium, magnesium) show modest, context-dependent benefits, primarily in children with baseline deficiencies. Emerging research suggests that multi-component nutraceuticals—including polyphenols and coordinated micronutrient formulations—may enhance redox balance and improve pulmonary or vascular outcomes, though current evidence is limited by small sample sizes and heterogeneity. Experimental data strongly support mitochondria-targeted mechanisms, but pediatric clinical validation remains sparse. Strategies that reduce oxidative burden or strengthen antioxidant defenses appear biologically plausible adjuncts to standard asthma therapy. Further large, biomarker-guided trials are needed to clarify efficacy, identify responsive phenotypes, and determine the role of multi-component approaches relative to single-nutrient supplementation.
Oxidative stress—an imbalance between reactive oxygen/nitrogen species and antioxidant defenses—contributes not only to the developmental origins of asthma but also to poor control, airway remodeling, and corticosteroid-resistant inflammation in children. Persistent oxidant exposure, nutritional insufficiency, and mitochondrial dysfunction sustain redox imbalance in pediatric asthma, suggesting potential roles for environmental, dietary, and nutraceutical strategies—defined here as natural bioactive compounds providing health benefits beyond basic nutrition, including polyphenols such as curcumin, quercetin, and resveratrol, and essential minerals such as zinc and selenium—that complement standard therapy. To summarize evidence on preventive and therapeutic approaches that modulate oxidative stress in pediatric asthma, focusing on environmental control, antioxidant-rich dietary patterns, single and multi-component nutraceuticals, and mitochondria-targeted interventions. A structured review of PubMed, Scopus, and Embase (1995–2025) identified peer-reviewed English-language epidemiologic studies, mechanistic models, and clinical trials evaluating oxidative stress, antioxidant status, and asthma outcomes in children and, when relevant, adults. Reference lists of major reviews were screened to identify additional studies. Interventions that reduce exposure to air pollutants and tobacco smoke, combined with antioxidant-rich diets such as high fruit/vegetable intake and Mediterranean-style patterns, are consistently associated with improved lung function, fewer symptoms, and reduced inflammation. Clinical trials of single antioxidants (vitamin D, vitamin E, zinc, selenium, magnesium) show modest, context-dependent benefits, primarily in children with baseline deficiencies. Emerging research suggests that multi-component nutraceuticals—including polyphenols and coordinated micronutrient formulations—may enhance redox balance and improve pulmonary or vascular outcomes, though current evidence is limited by small sample sizes and heterogeneity. Experimental data strongly support mitochondria-targeted mechanisms, but pediatric clinical validation remains sparse. Strategies that reduce oxidative burden or strengthen antioxidant defenses appear biologically plausible adjuncts to standard asthma therapy. Further large, biomarker-guided trials are needed to clarify efficacy, identify responsive phenotypes, and determine the role of multi-component approaches relative to single-nutrient supplementation.
DOI: https://doi.org/10.37349/emed.2026.1001420
This article belongs to the special issue Asthma in Children: Origins, Endotypes and Future Perspectives
Aim:
To determine the level of agreement between remote and in-person assessment for the Timed Up and Go test (TUG), the Lateral Step-Up test (LSU), the Five-Times-Sit-To-Stand test (FTSTS), and the Pediatric Balance Scale (PBS) in children with cerebral palsy (CP).
Methods:
Fifteen children diagnosed with unilateral and bilateral spastic CP and Gross Motor Function Classification System levels I–II underwent these four tests in two distinct environments. These assessments were conducted 24 to 48 hours apart, first in person at the physiotherapy clinic and then remotely at home via the VSee platform. Before the remote assessment, all parents attended a preliminary training session that covered technical proficiency with VSee, the proper setup of home equipment, and essential safety protocols.
Results:
Children had a median age of 7 (IQR = 6–10) years old. All children successfully finished all four tests in both the home and clinic settings without any reported safety issues. The agreement was good for the time of repetitions in the FTSTS: ICC = 0.884 (95% CI: 0.654 to 0.961; MD = –1.26 seconds, 95% CI: –2.81 to 0.28, p = 0.102), and excellent for the total time of the TUG: ICC = 0.998 (95% CI: 0.990 to 0.999; MD = –0.42 seconds, 95% CI: –0.76 to –0.08, p = 0.017), the total score in the PBS: ICC = 0.998 (95% CI: 0.992 to 0.999; MD = 0.26 units, 95% CI: 0.01 to 0.52, p = 0.041), and the total number of steps in the LSU: ICC = 0.988 (95% CI: 0.965 to 0.996; MD = 0.53 steps, 95% CI: –0.68 to 1.75, p = 0.364).
Conclusions:
Remote evaluation of the FTSTS, TUG, LSU, and PBS demonstrates good-to-excellent agreement with in-person assessment. However, wide limits of agreement indicated individual variability.
DOI: https://doi.org/10.37349/emed.2026.1001419
Acute wheeze is one of the most common paediatric presentations to emergency care. Although blood eosinophils (BEO) are an established biomarker of type 2 inflammation in stable asthma, their role in guiding acute management—particularly systemic corticosteroid use—remains unclear. The aim of this review was to map and synthesise the existing evidence on the measurement and clinical utility of BEO sampled during acute wheeze exacerbations in children. A scoping review was conducted in accordance with Joanna Briggs Institute methodology and Preferred Reporting Items for Systematic Reviews and Meta-Analysis extension for scoping reviews (PRISMA-ScR) guidelines. Medline, Embase, Cochrane Library and Web of Science were searched for studies published in the last 20 years involving children under 16 years presenting acutely with wheeze and undergoing eosinophil testing. Prospective and retrospective studies were included. Data were summarised descriptively according to eosinophil measurement methods, reported values, cut-offs and associations with characteristics and treatment response. Eight heterogeneous studies (n = 855) met inclusion criteria, comprising five observational or retrospective studies and three randomised controlled trials. BEO reporting varied widely, with inconsistent units, cut-offs and poorly described sampling timing. No study utilised point-of-care testing. Across studies, eosinophil dynamics differed by age, wheeze phenotype, disease severity and viral aetiology, preventing meaningful comparison. Evidence supporting eosinophil-guided corticosteroid use was limited. Two studies demonstrated improved outcomes with systemic corticosteroids in children with rhinovirus-associated wheeze and higher BEO, while lower BEO were observed in respiratory syncytial virus (RSV)-associated wheeze. There is a paucity of high-quality data describing BEO during acute wheeze exacerbations in children. Current evidence underpinning eosinophil-guided care is largely derived from stable outpatient cohorts and may not be directly applicable to acute settings. Prospective studies with standardised sampling of BEO during acute presentations are needed to inform precision-based corticosteroid use.
Acute wheeze is one of the most common paediatric presentations to emergency care. Although blood eosinophils (BEO) are an established biomarker of type 2 inflammation in stable asthma, their role in guiding acute management—particularly systemic corticosteroid use—remains unclear. The aim of this review was to map and synthesise the existing evidence on the measurement and clinical utility of BEO sampled during acute wheeze exacerbations in children. A scoping review was conducted in accordance with Joanna Briggs Institute methodology and Preferred Reporting Items for Systematic Reviews and Meta-Analysis extension for scoping reviews (PRISMA-ScR) guidelines. Medline, Embase, Cochrane Library and Web of Science were searched for studies published in the last 20 years involving children under 16 years presenting acutely with wheeze and undergoing eosinophil testing. Prospective and retrospective studies were included. Data were summarised descriptively according to eosinophil measurement methods, reported values, cut-offs and associations with characteristics and treatment response. Eight heterogeneous studies (n = 855) met inclusion criteria, comprising five observational or retrospective studies and three randomised controlled trials. BEO reporting varied widely, with inconsistent units, cut-offs and poorly described sampling timing. No study utilised point-of-care testing. Across studies, eosinophil dynamics differed by age, wheeze phenotype, disease severity and viral aetiology, preventing meaningful comparison. Evidence supporting eosinophil-guided corticosteroid use was limited. Two studies demonstrated improved outcomes with systemic corticosteroids in children with rhinovirus-associated wheeze and higher BEO, while lower BEO were observed in respiratory syncytial virus (RSV)-associated wheeze. There is a paucity of high-quality data describing BEO during acute wheeze exacerbations in children. Current evidence underpinning eosinophil-guided care is largely derived from stable outpatient cohorts and may not be directly applicable to acute settings. Prospective studies with standardised sampling of BEO during acute presentations are needed to inform precision-based corticosteroid use.
DOI: https://doi.org/10.37349/emed.2026.1001418
This article belongs to the special issue Asthma in Children: Origins, Endotypes and Future Perspectives
Aim:
Human Immunodeficiency Virus (HIV) and Acquired Immunodeficiency Syndrome (AIDS) have attained a manageable chronic status as more infected people experience increases in their life quality and expectancy. Health system factors affect adherence to Antiretroviral Therapy (ART) among persons living with HIV (PLHIV). Nonetheless, literature on health-system factors and ART adherence among PLHIV is sparse. This study therefore aimed to elucidate clinical and health system factors associated with ART adherence among PLHIV in Tamale Metropolis.
Methods:
We conducted a facility-based cross-sectional survey of 418 PLHIV in the Tamale Metropolis, selected by convenience sampling from three major ART centres. Each factor associated with ART adherence, considered statistically significant at a p-value of < 0.05 with a 95% confidence interval, was analysed using both binary and multivariate logistic regression. Adherence was assessed by self-report of missed doses in the past 30 days, categorised as good (≥ 95% of prescribed doses taken) or poor (< 95% of prescribed doses taken).
Results:
The overall ART adherence rate was 93.1% (95% CI: 90.3%–95.2%). Clinical and health system factors significantly associated with higher adherence included the absence of post-pill fatigue (AOR = 0.09; 95% CI: 0.02–0.37), absence of complaints regarding pill size (AOR = 3.71; 95% CI: 1.23–11.18), lower cost of accessing therapy (AOR = 0.27; 95% CI: 0.10–0.73), uninterrupted ART supply (AOR = 7.76; 95% CI: 1.02–59.30), and strong social support systems (AOR = 6.62; 95% CI: 1.18–37.21).
Conclusions:
An adherence rate of 93% was obtained which falls short of the 95% global benchmark. Clinical factors promoting adherence included the absence of fatigue and concerns related to pill size, while health system-related factors promoting adherence included reduced cost of access, consistent ART supply, and good social support. The Ghana AIDS Commission and its implementing partners are urged to strengthen community-based social support networks, expand ART distribution points, and develop targeted educational initiatives to improve therapy adherence and contribute to achieving epidemic control. Limitations of this study include the use of self-reported adherence (potential recall and social desirability bias) and the cross-sectional design, which precludes causal inference.
DOI: https://doi.org/10.37349/emed.2026.1001417
This article belongs to the special issue Global Perspectives on the Clinical Diagnosis, Treatment, and Functional Cure of HIV Infection in the Post-ART Era
Aim:
Diabetes mellitus is a growing non-communicable disease (NCD) imposing major health and economic burdens in Ethiopia. While prior national and subnational estimates have been published using Global Burden of Disease (GBD) 2019 data, this study provides novel, updated estimates reflecting newly delineated regional boundaries and recent socio-demographic shifts using GBD 2023 data. We aimed to estimate the national and subnational burden and trends of diabetes mellitus in Ethiopia from 1990 to 2023.
Methods:
This analysis is part of the GBD 2023 study, a collaborative effort between the Ethiopian Public Health Institute and the Institute for Health Metrics and Evaluation. Estimates were generated using standard GBD modeling tools [DisMod-MR 2.1 and Cause of Death Ensemble modeling (CODEm)] for incidence, prevalence, mortality, years of life lost (YLLs), years lived with disability (YLDs), and DALYs [with 95% uncertainty intervals (UI)] across Ethiopia’s regions and city administrations.
Results:
In 2023, Ethiopia’s age-standardized prevalence of all forms of diabetes mellitus (type 1 and type 2 combined) was 2,996.4 (95% UI: 2,704.8–3,269.5) cases per 100,000 population. Type 2 diabetes accounted for nearly 99% of cases. The Somali region had the lowest prevalence (2,243.1 per 100,000), about 45% lower than in Sidama (4,066.4 per 100,000), highlighting marked regional disparities. The age-standardized DALY rate was 1,124.2 per 100,000. While high fasting plasma glucose was the leading proximal risk factor, high body mass index ranked as the top upstream modifiable risk factor (264.1 DALYs per 100,000).
Conclusions:
This study highlights the substantial and unevenly distributed burden of diabetes mellitus in Ethiopia, driven predominantly by type 2 diabetes and modifiable metabolic risk factors. These findings call for tailored, region-specific strategies, such as targeted obesity prevention in high-prevalence urban centers and strengthened health system capacity in high-mortality pastoral regions to curb the future burden and align with global NCD targets.
DOI: https://doi.org/10.37349/emed.2026.1001416
Early-life oxidative stress, resulting from an imbalance between reactive oxygen species (ROS) and reactive nitrogen species (RNS) and antioxidant defenses, has increasingly been proposed as an important contributor to the developmental origins of childhood asthma. Prenatal and early postnatal exposures—including pollutants, tobacco smoke, maternal distress, nutritional imbalance, and allergen-derived oxidase activity—may disrupt epithelial integrity and redox-regulated immune pathways, potentially predisposing the developing lung to allergic inflammation. To synthesize current mechanistic and epidemiologic evidence on how oxidative stress during early life may contribute to asthma development, with particular focus on environmental drivers, redox–immune interactions, and gene-environment susceptibility. A structured review of PubMed, Scopus, and Embase identified peer-reviewed English-language studies from birth cohorts, mechanistic models, and biomarker analyses evaluating oxidative stress, antioxidant capacity, and asthma-related outcomes. Environmental oxidants and nutritional deficiencies may increase ROS production, promoting epithelial injury, activation of redox-sensitive pathways such as NF-κB and MAPK, and the release of epithelial alarmins including IL-33, IL-25, and thymic stromal lymphopoietin (TSLP). These signals can influence innate immune activation and antigen-presenting cell function, favoring Th2/Th17-biased immune responses. Genetic variants in antioxidant pathways, including GSTM1, GSTP1, and Nrf2, may further modify susceptibility to oxidant exposures. Epidemiologic studies from birth cohorts report associations between early-life oxidative exposures, reduced lung growth, wheezing, allergic sensitization, and asthma risk. Current mechanistic and epidemiologic evidence suggests that oxidative stress may represent an important biological pathway linking early-life environmental exposures with asthma susceptibility, although further studies are needed to clarify its role within the complex network of factors contributing to asthma development.
Early-life oxidative stress, resulting from an imbalance between reactive oxygen species (ROS) and reactive nitrogen species (RNS) and antioxidant defenses, has increasingly been proposed as an important contributor to the developmental origins of childhood asthma. Prenatal and early postnatal exposures—including pollutants, tobacco smoke, maternal distress, nutritional imbalance, and allergen-derived oxidase activity—may disrupt epithelial integrity and redox-regulated immune pathways, potentially predisposing the developing lung to allergic inflammation. To synthesize current mechanistic and epidemiologic evidence on how oxidative stress during early life may contribute to asthma development, with particular focus on environmental drivers, redox–immune interactions, and gene-environment susceptibility. A structured review of PubMed, Scopus, and Embase identified peer-reviewed English-language studies from birth cohorts, mechanistic models, and biomarker analyses evaluating oxidative stress, antioxidant capacity, and asthma-related outcomes. Environmental oxidants and nutritional deficiencies may increase ROS production, promoting epithelial injury, activation of redox-sensitive pathways such as NF-κB and MAPK, and the release of epithelial alarmins including IL-33, IL-25, and thymic stromal lymphopoietin (TSLP). These signals can influence innate immune activation and antigen-presenting cell function, favoring Th2/Th17-biased immune responses. Genetic variants in antioxidant pathways, including GSTM1, GSTP1, and Nrf2, may further modify susceptibility to oxidant exposures. Epidemiologic studies from birth cohorts report associations between early-life oxidative exposures, reduced lung growth, wheezing, allergic sensitization, and asthma risk. Current mechanistic and epidemiologic evidence suggests that oxidative stress may represent an important biological pathway linking early-life environmental exposures with asthma susceptibility, although further studies are needed to clarify its role within the complex network of factors contributing to asthma development.
DOI: https://doi.org/10.37349/emed.2026.1001415
This article belongs to the special issue Asthma in Children: Origins, Endotypes and Future Perspectives
Aim:
Tremor is one of the most common neurological movement disorders, arising from dysfunction in the neuromuscular system. However, comprehensive analyses of peripheral blood elements, red blood cells (RBC) and white blood cells (WBC) counts, as well as liver and kidney function in patients with tremor remain limited. This cross-sectional study investigated alterations in serum elements, complete blood counts, and liver function in patients with tremor. The study sought to identify independent risk factors and evaluate their diagnostic performance.
Methods:
Blood samples from 79 patients with tremor and 82 healthy controls were analyzed. Serum elements, RBC, WBC, platelet (PLT), liver function, and renal function were measured using the QL8000 element analyzer, XN 2800 automated hematology analyzer, and Roche Cobas 8000 system.
Results:
Serum copper (Cu) and lead (Pb) levels were significantly elevated in tremor patients. These patients also showed increased monocytes, decreased eosinophils, and impaired liver function, including elevated aspartate aminotransferase and globulin with reduced albumin.
Conclusions:
Tremor patients show distinct alterations in Cu, Pb, monocyte counts, eosinophil counts, and liver function markers. These findings suggest that these parameters may serve as potential diagnostic indicators and therapeutic targets. Cu and Pb were identified as independent risk factors, and their combination significantly improved diagnostic efficiency.
DOI: https://doi.org/10.37349/emed.2026.1001414
Artificial intelligence (AI) has rapidly advanced in radiology, demonstrating high performance across a wide range of diagnostic tasks. However, clinical adoption remains slower and more uneven than anticipated. This discrepancy reflects a fundamental gap between algorithm validation and clinical implementation. Current validation strategies primarily rely on controlled datasets and performance metrics such as accuracy and area under the curve, which often fail to capture the complexity of clinical environments. This article examines the nature of this “validation gap” and argues that it reflects a broader structural mismatch between how AI systems are evaluated and how clinical care operates. We propose a conceptual framework comprising three levels of validation: technical validity, workflow validity, and clinical validity. While most studies focus on technical performance, limited attention is given to integration into clinical workflows and impact on patient outcomes. Key factors contributing to this gap include limited generalizability across diverse populations and imaging protocols, poor alignment with clinical workflows, and the underrepresentation of uncertainty in model outputs. These limitations hinder effective implementation and may reduce trust in AI systems. Bridging this gap requires a shift toward more comprehensive validation strategies, including multicenter and prospective studies, improved workflow integration, and explicit incorporation of uncertainty and human–AI interaction. Ultimately, the clinical value of AI in radiology should be assessed not only by its performance in controlled settings but also by its ability to support decision-making and improve patient outcomes in real-world practice.
Artificial intelligence (AI) has rapidly advanced in radiology, demonstrating high performance across a wide range of diagnostic tasks. However, clinical adoption remains slower and more uneven than anticipated. This discrepancy reflects a fundamental gap between algorithm validation and clinical implementation. Current validation strategies primarily rely on controlled datasets and performance metrics such as accuracy and area under the curve, which often fail to capture the complexity of clinical environments. This article examines the nature of this “validation gap” and argues that it reflects a broader structural mismatch between how AI systems are evaluated and how clinical care operates. We propose a conceptual framework comprising three levels of validation: technical validity, workflow validity, and clinical validity. While most studies focus on technical performance, limited attention is given to integration into clinical workflows and impact on patient outcomes. Key factors contributing to this gap include limited generalizability across diverse populations and imaging protocols, poor alignment with clinical workflows, and the underrepresentation of uncertainty in model outputs. These limitations hinder effective implementation and may reduce trust in AI systems. Bridging this gap requires a shift toward more comprehensive validation strategies, including multicenter and prospective studies, improved workflow integration, and explicit incorporation of uncertainty and human–AI interaction. Ultimately, the clinical value of AI in radiology should be assessed not only by its performance in controlled settings but also by its ability to support decision-making and improve patient outcomes in real-world practice.
DOI: https://doi.org/10.37349/emed.2026.1001412
This article belongs to the special issue Artificial Intelligence in Precision Imaging: Innovations Shaping the Future of Clinical Diagnostics
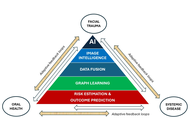
Artificial intelligence (AI) is transforming clinical decision-making across cranio-maxillofacial trauma, oral health, and systemic disease. These domains are increasingly recognised as biologically and clinically interconnected, yet they are often studied and managed independently. This perspective introduces the concept of an integrative triangle linking facial trauma, oral health, and systemic disease, with AI serving as the computational bridge that enables cross-domain modelling and coordinated care. AI applications within this framework include imaging-based fracture detection, patient-specific implant design, automated oral disease diagnosis, multimodal risk prediction, and longitudinal outcome modelling. By integrating imaging, clinical, laboratory, and behavioural data, AI can identify shared inflammatory and metabolic pathways influencing trauma recovery and chronic disease progression. This closed-loop paradigm supports continuous learning, allowing outcomes in one domain to inform prediction and intervention in the others. The integrative triangle provides a translational roadmap for precision medicine, moving from isolated prediction toward coordinated prevention and intervention. Future development will require multimodal data integration, prospective validation, and responsible governance to ensure explainable and equitable AI deployment. This framework positions facial trauma and oral health as central components of systemic precision medicine and highlights AI as a catalyst for integrated, patient-centred care.
Artificial intelligence (AI) is transforming clinical decision-making across cranio-maxillofacial trauma, oral health, and systemic disease. These domains are increasingly recognised as biologically and clinically interconnected, yet they are often studied and managed independently. This perspective introduces the concept of an integrative triangle linking facial trauma, oral health, and systemic disease, with AI serving as the computational bridge that enables cross-domain modelling and coordinated care. AI applications within this framework include imaging-based fracture detection, patient-specific implant design, automated oral disease diagnosis, multimodal risk prediction, and longitudinal outcome modelling. By integrating imaging, clinical, laboratory, and behavioural data, AI can identify shared inflammatory and metabolic pathways influencing trauma recovery and chronic disease progression. This closed-loop paradigm supports continuous learning, allowing outcomes in one domain to inform prediction and intervention in the others. The integrative triangle provides a translational roadmap for precision medicine, moving from isolated prediction toward coordinated prevention and intervention. Future development will require multimodal data integration, prospective validation, and responsible governance to ensure explainable and equitable AI deployment. This framework positions facial trauma and oral health as central components of systemic precision medicine and highlights AI as a catalyst for integrated, patient-centred care.
DOI: https://doi.org/10.37349/emed.2026.1001413
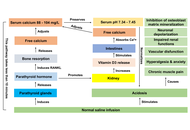
Recent studies argue that other physiological solutions are superior to normal saline, which is due to their physiological features, better outcomes in critical care, and lower risk of hyperchloremia and acidosis; nonetheless, it is still a mystery how normal saline has dominated the field of fluid therapy worldwide. Moreover, there is an ongoing debate on whether harm to human health may limit its spread in the future. Additionally, new evidence revealed some of the deleterious effects of normal saline, including coagulopathy, metabolic acidosis, acute kidney injury (AKI), and higher mortality in ICU. The predominant cause for these outcomes appears to be the excess chloride concentration of normal saline relative to plasma. Therefore, it appears relevant to suggest that a normal saline solution should be normalized to that of human serum to overcome these pitfalls. An ideal normal saline solution shall be similar to human serum in its pH, osmolarity, and content of sodium, chloride, and essential minerals.
Recent studies argue that other physiological solutions are superior to normal saline, which is due to their physiological features, better outcomes in critical care, and lower risk of hyperchloremia and acidosis; nonetheless, it is still a mystery how normal saline has dominated the field of fluid therapy worldwide. Moreover, there is an ongoing debate on whether harm to human health may limit its spread in the future. Additionally, new evidence revealed some of the deleterious effects of normal saline, including coagulopathy, metabolic acidosis, acute kidney injury (AKI), and higher mortality in ICU. The predominant cause for these outcomes appears to be the excess chloride concentration of normal saline relative to plasma. Therefore, it appears relevant to suggest that a normal saline solution should be normalized to that of human serum to overcome these pitfalls. An ideal normal saline solution shall be similar to human serum in its pH, osmolarity, and content of sodium, chloride, and essential minerals.
DOI: https://doi.org/10.37349/emed.2026.1001411
Aim:
To evaluate ultrasound-derived congestion phenotypes in acute decompensated heart failure with preserved ejection fraction (HFpEF) and their association with cardiac remodeling and in-hospital outcomes.
Methods:
This prospective study included 235 patients (median age 77.0 years, 75.3% women) with acute decompensated HFpEF. Within 2 hours of admission, all patients underwent echocardiography, lung ultrasound (B-lines), venous excess ultrasound score (VExUS) assessment, and bioimpedance analysis. Patients were classified into three phenotypes based on pulmonary (B-lines > 3) and systemic venous congestion (VExUS): low-low (no significant pulmonary or systemic congestion), pulmonary-dominant, and mixed severe. The primary endpoint was in-hospital mortality.
Results:
Moderate-to-severe venous congestion (VExUS grade 2–3) was present in 60.8% of patients. The mixed severe phenotype predominated (60.9%) and was associated with higher body mass index (BMI) and waist (p < 0.001). This group demonstrated more advanced cardiac dysfunction, including higher E/e’ (14.9 vs. 11.9; p < 0.001), greater left atrial remodeling (left atrial volume index 45.0 vs. 39.0 mL/m2; p < 0.001), and increased left ventricular mass index (p = 0.010). Right ventricular (RV) involvement was more pronounced, with lower TAPSE (18.0 vs. 20.0 mm; p < 0.001) and higher tricuspid regurgitation velocity (p < 0.001). Markers of congestion showed a gradient, with higher NT-proBNP (3,072.5 vs. 1,197.0 pg/mL; p < 0.001), increased extracellular water (129% vs. 101%; p < 0.001), and lower phase angle (4.9 vs. 5.5; p < 0.001). In-hospital mortality was highest in the mixed severe phenotype [11.2% vs. 3.0% and 1.7%; p = 0.039; odds ratio (OR) 5.67]. B-lines correlated with tricuspid regurgitation velocity, E/e’, and extracellular water (all r ≥ 0.50).
Conclusions:
Ultrasound-derived congestion phenotyping in HFpEF identifies distinct profiles associated with atrial and ventricular remodeling and worse in-hospital outcomes. Future studies are required to determine whether phenotype-guided decongestive strategies can improve outcomes beyond risk stratification.
DOI: https://doi.org/10.37349/emed.2026.1001410
This article belongs to the special issue Assessment of Atrial and Ventricular Volumes and Functional Properties: Novel Insights
