



 Previous
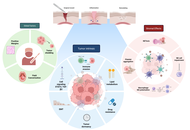
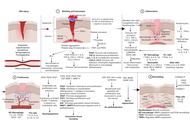
There is a growing body of evidence showing that the postoperative wound healing response shares molecular machinery with tumor pathways. Within larger surgical fields such as breast or colorectal cancer, strong preclinical and clinical evidence exists demonstrating a link between postoperative wound complications and cancer recurrence. Head and neck surgery represents a unique landscape with high rates of surgical site infections (SSIs; 20–30%), driven in part by inherent wound contamination from the aerodigestive tract, in addition to prolonged operative times, malnutrition, smoking, and poor overall health. Despite this, studies addressing postoperative wound healing and head and neck cancer (HNC) recurrence remain fragmented at best, with studies demonstrating significant heterogeneity and conflicting results. A thorough understanding of the oncologic implications of wound complications in HNC is vitally important to improve patient outcomes and identify novel therapeutic strategies. This narrative review seeks to synthesize preclinical and clinical studies linking the postoperative wound environment to HNC recurrence. We also seek to highlight emerging approaches to optimize postoperative wound healing for an oncologic benefit, including the role of surgical drain fluid as a novel bioresource, alternative reconstructive hardware, the role of neoadjuvant immunotherapy, and emerging biomaterials.
There is a growing body of evidence showing that the postoperative wound healing response shares molecular machinery with tumor pathways. Within larger surgical fields such as breast or colorectal cancer, strong preclinical and clinical evidence exists demonstrating a link between postoperative wound complications and cancer recurrence. Head and neck surgery represents a unique landscape with high rates of surgical site infections (SSIs; 20–30%), driven in part by inherent wound contamination from the aerodigestive tract, in addition to prolonged operative times, malnutrition, smoking, and poor overall health. Despite this, studies addressing postoperative wound healing and head and neck cancer (HNC) recurrence remain fragmented at best, with studies demonstrating significant heterogeneity and conflicting results. A thorough understanding of the oncologic implications of wound complications in HNC is vitally important to improve patient outcomes and identify novel therapeutic strategies. This narrative review seeks to synthesize preclinical and clinical studies linking the postoperative wound environment to HNC recurrence. We also seek to highlight emerging approaches to optimize postoperative wound healing for an oncologic benefit, including the role of surgical drain fluid as a novel bioresource, alternative reconstructive hardware, the role of neoadjuvant immunotherapy, and emerging biomaterials.
DOI: https://doi.org/10.37349/etat.2026.1002405


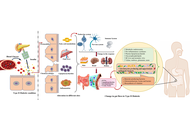
Type 2 diabetes mellitus (T2DM) is a complex metabolic disorder characterized by insulin resistance, impaired glucose regulation, and chronic low-grade inflammation. Over the past decade, the gut microbiota (GM) has emerged as an important determinant of metabolic health, with increasing evidence showing that gut microbial dysbiosis and its associated metabolites influence intestinal barrier function, immune regulation, insulin sensitivity, and glucose homeostasis. Although previous studies have examined either GM, dietary interventions, or probiotic supplementation in T2DM, a comprehensive study linking microbial metabolites with personalized nutrition (PN) and emerging microbiota-based therapeutic strategies remains lacking. This review addresses this gap by discussing the mechanistic roles of important gut microbial metabolites, such as short-chain fatty acids (SCFAs), lipopolysaccharides (LPS), trimethylamine-N-oxide, indolepropionic acid (IPA), and bile acids (BAs), in the development and progression of T2DM. It further describes how dietary strategies, including high-fiber and prebiotic-rich diets, probiotics, synbiotics, polyphenol-rich foods, and PN, improve glycemic control and metabolic health. Recent advances in microbiota-targeted interventions, including postbiotics, next-generation probiotics, engineered probiotics, and fecal microbiota, are also discussed along with their therapeutic potential and existing clinical limitations. By combining mechanistic insights with nutritional and therapeutic perspectives, this review provides a single framework for understanding the diet-GM-host metabolic axis and offers future directions for developing microbiome-informed precision nutrition strategies for the prevention and management of T2DM.
Type 2 diabetes mellitus (T2DM) is a complex metabolic disorder characterized by insulin resistance, impaired glucose regulation, and chronic low-grade inflammation. Over the past decade, the gut microbiota (GM) has emerged as an important determinant of metabolic health, with increasing evidence showing that gut microbial dysbiosis and its associated metabolites influence intestinal barrier function, immune regulation, insulin sensitivity, and glucose homeostasis. Although previous studies have examined either GM, dietary interventions, or probiotic supplementation in T2DM, a comprehensive study linking microbial metabolites with personalized nutrition (PN) and emerging microbiota-based therapeutic strategies remains lacking. This review addresses this gap by discussing the mechanistic roles of important gut microbial metabolites, such as short-chain fatty acids (SCFAs), lipopolysaccharides (LPS), trimethylamine-N-oxide, indolepropionic acid (IPA), and bile acids (BAs), in the development and progression of T2DM. It further describes how dietary strategies, including high-fiber and prebiotic-rich diets, probiotics, synbiotics, polyphenol-rich foods, and PN, improve glycemic control and metabolic health. Recent advances in microbiota-targeted interventions, including postbiotics, next-generation probiotics, engineered probiotics, and fecal microbiota, are also discussed along with their therapeutic potential and existing clinical limitations. By combining mechanistic insights with nutritional and therapeutic perspectives, this review provides a single framework for understanding the diet-GM-host metabolic axis and offers future directions for developing microbiome-informed precision nutrition strategies for the prevention and management of T2DM.
DOI: https://doi.org/10.37349/eff.2026.1010193
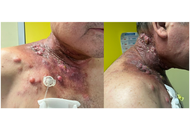
Nasopharyngeal carcinoma (NPC) with cutaneous metastases (lethalides) is an exceedingly rare event associated with an aggressive clinical course and poor prognosis, making the management of plurirefractory disease a significant challenge in the evolving landscape of immunotherapy. Here, we report the case of a 59-year-old male diagnosed with stage IVA Epstein–Barr virus (EBV)-positive non-keratinizing NPC who achieved a complete response after induction chemotherapy and concurrent chemoradiotherapy. Twenty-six months later, the patient developed multifocal cutaneous metastases and locoregional recurrence. Over the course of approximately two and a half years, he received six lines of therapy, including platinum-based regimens, pembrolizumab, and cetuximab-paclitaxel, before enrolling in the phase I/II ABILITY-1 trial, where he received the novel interleukin-2 (IL-2) superkine MDNA11 plus pembrolizumab. Despite transient stabilization, the disease progressed, and the patient died 62 months after initial diagnosis. Throughout his clinical course, plasma EBV DNA acted as a precise real-time surrogate of tumor burden, consistently anticipating radiologic progression. This case underscores the aggressive nature of cutaneous NPC and the pivotal role of serial EBV DNA monitoring in guiding therapeutic transitions. Furthermore, the lack of response to multiple agents, including next-generation IL-2 variants, highlights the profound immune exhaustion in late-stage NPC and emphasizes the urgent need for novel targeted strategies, such as antibody-drug conjugates and adoptive T-cell therapies, in the post-immunotherapy setting.
Nasopharyngeal carcinoma (NPC) with cutaneous metastases (lethalides) is an exceedingly rare event associated with an aggressive clinical course and poor prognosis, making the management of plurirefractory disease a significant challenge in the evolving landscape of immunotherapy. Here, we report the case of a 59-year-old male diagnosed with stage IVA Epstein–Barr virus (EBV)-positive non-keratinizing NPC who achieved a complete response after induction chemotherapy and concurrent chemoradiotherapy. Twenty-six months later, the patient developed multifocal cutaneous metastases and locoregional recurrence. Over the course of approximately two and a half years, he received six lines of therapy, including platinum-based regimens, pembrolizumab, and cetuximab-paclitaxel, before enrolling in the phase I/II ABILITY-1 trial, where he received the novel interleukin-2 (IL-2) superkine MDNA11 plus pembrolizumab. Despite transient stabilization, the disease progressed, and the patient died 62 months after initial diagnosis. Throughout his clinical course, plasma EBV DNA acted as a precise real-time surrogate of tumor burden, consistently anticipating radiologic progression. This case underscores the aggressive nature of cutaneous NPC and the pivotal role of serial EBV DNA monitoring in guiding therapeutic transitions. Furthermore, the lack of response to multiple agents, including next-generation IL-2 variants, highlights the profound immune exhaustion in late-stage NPC and emphasizes the urgent need for novel targeted strategies, such as antibody-drug conjugates and adoptive T-cell therapies, in the post-immunotherapy setting.
DOI: https://doi.org/10.37349/emed.2026.1001431
Aim:
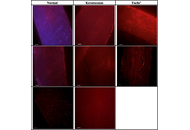
This preliminary study aims to evaluate the expression of high mobility group box 1 (HMGB-1) in keratoconic corneas, normal corneas, and corneas from donors with Fuchs’ corneal dystrophy using immunohistochemistry.
Methods:
Under a Loyola University Institutional Review Board (IRB) approved protocol (LU#219768), archived paraffin-embedded corneal tissues were obtained from the Loyola University Medical Center Department of Pathology. The study included three keratoconic corneas, three normal donor corneas, and three Fuchs’ dystrophy corneas. Tissue sections were deparaffinized in 100% xylene, rehydrated through a graded ethanol series, and subjected to antigen retrieval. Sections were stained with an HMGB-1 primary antibody, followed by a fluorescently conjugated anti-rabbit IgG secondary antibody and 4',6-diamidino-2-phenylindole (DAPI) nuclear counterstain. Immunofluorescence imaging and deconvolution analysis were performed using a Nikon Eclipse Ti2 microscope equipped with a digital camera. Two prespecified comparisons, keratoconus versus normal and Fuchs’ dystrophy versus normal, were evaluated using Welch’s independent-samples t tests with Holm adjustment for multiple testing. Statistical analyses were performed using IBM SPSS Statistics.
Results:
HMGB-1 expression was increased in corneal tissues from patients with keratoconus and Fuchs’ corneal dystrophy compared with normal controls. The increased levels of HMGB-1 suggest enhanced activation of pro-inflammatory and tissue-remodeling pathways. Increased HMGB-1 expression in keratoconus may be associated with cellular stress, inflammation, and extracellular matrix remodeling.
Conclusions:
These preliminary findings suggest that HMGB-1 expression may be increased in keratoconus; however, due to the small sample size of n = 3 per group, larger studies are needed to confirm this association and clarify its potential role in disease pathogenesis. These findings suggest that HMGB-1 may be associated with corneal cellular stress and inflammatory signaling present in keratoconic corneas and warrant further investigation and validation.
DOI: https://doi.org/10.37349/emed.2026.1001430
Aim:
Childhood stress can alter adolescent stress responses, predisposing individuals to neurochemical imbalances associated with psychosis later in life. Antipsychotic treatments are limited by extrapyramidal and metabolic side effects with insignificant impact on stress-related abnormalities in schizophrenia. Flavonoids such as apigenin may offer a safer therapeutic alternative with broader neuroprotective effects. This study evaluated the effects of apigenin on serotonin and noradrenaline (NA) systems and psychotic-like behaviours in a two-hit neurodevelopmental rat model of psychosis.
Methods:
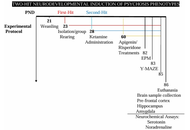
Sixty-four male rats at postnatal day (PND) 21 were assigned to either group-housed or isolation-reared conditions from PND 23–85 and divided into eight groups (n = 8). From PND 28–85, animals received saline (0.9% NaCl) or ketamine (16 mg/kg, i.p.). Apigenin (8 mg/kg, i.p.) or risperidone (0.5 mg/kg, i.p.) was administered from PND 60–85. Anxiety-like behaviour and working memory were assessed using the Elevated Plus Maze (EPM) and Y-Maze on PND 82 and 83, respectively. On PND 86, animals were sacrificed, and the amygdala, hippocampus, and prefrontal cortex were analyzed for serotonin and NA levels using ELISA (enzyme-linked immunosorbent assay).
Results:
Apigenin increased time spent and entries into the closed arms of the EPM, indicating anxiogenic effects. Although ketamine and isolation rearing produced no significant difference in the Y-maze test compared to vehicle, apigenin improved spontaneous alternation in both housing conditions. In group-housed rats, apigenin significantly (p < 0.05) increased serotonin and NA levels in the amygdala and hippocampus, while in the prefrontal, it increased serotonin levels with no significant effect on NA levels when compared to ketamine only control. In isolation-reared rats, it produced a marked increase in serotonin levels in all the examined brain regions, including increased NA levels in the amygdala with differential reduction in NA levels in both hippocampus and pre-frontal cortex when compared with ketamine control.
Conclusions:
Apigenin exerted anxiogenic effects while improving working memory and enhancing monoaminergic neurotransmission, suggesting potential therapeutic benefits for negative symptoms associated with schizophrenia.
DOI: https://doi.org/10.37349/en.2026.1006151
Type 2 diabetes is an error in the glycemic control system caused by insulin resistance. Self-organizing control systems use artificial intelligence to monitor and correct how they function and are used in modern applications of robotics. The development of type 2 diabetes is gradual and reversible through lifestyle changes, and this is consistent with insulin resistance being formed through a self-organizing or intelligent control system rather than the traditional control system on which current biomedical control systems are modelled. Lifestyles that induce high levels of glycemic variation would, in an intelligent control system, be detected as excessive oscillation, and an intelligent system can reduce oscillation by reducing the amplification. Insulin resistance represents low amplification in the glycemic control system. Intelligent control system functioning requires a network architecture, so if the glycemic control system is self-organizing, then it should be part of a network system that provides intelligent functioning for other control systems, and error in the glycemic control system would contribute to errors in other control systems and to a state of general network dysregulation. Intelligent systems theory explains how the comorbidities of type 2 diabetes and obesity would form through the dysregulation of a network of metabolic, immune, endocrine, and neurological pathways. The theory predicts that medical and lifestyle interventions for type 2 diabetes could improve comorbidities, but that comorbidities would reduce the effectiveness of those interventions. Studies are proposed to test this new theory that provides a non-blaming narrative for patients and could form a prequel to patient education.
Type 2 diabetes is an error in the glycemic control system caused by insulin resistance. Self-organizing control systems use artificial intelligence to monitor and correct how they function and are used in modern applications of robotics. The development of type 2 diabetes is gradual and reversible through lifestyle changes, and this is consistent with insulin resistance being formed through a self-organizing or intelligent control system rather than the traditional control system on which current biomedical control systems are modelled. Lifestyles that induce high levels of glycemic variation would, in an intelligent control system, be detected as excessive oscillation, and an intelligent system can reduce oscillation by reducing the amplification. Insulin resistance represents low amplification in the glycemic control system. Intelligent control system functioning requires a network architecture, so if the glycemic control system is self-organizing, then it should be part of a network system that provides intelligent functioning for other control systems, and error in the glycemic control system would contribute to errors in other control systems and to a state of general network dysregulation. Intelligent systems theory explains how the comorbidities of type 2 diabetes and obesity would form through the dysregulation of a network of metabolic, immune, endocrine, and neurological pathways. The theory predicts that medical and lifestyle interventions for type 2 diabetes could improve comorbidities, but that comorbidities would reduce the effectiveness of those interventions. Studies are proposed to test this new theory that provides a non-blaming narrative for patients and could form a prequel to patient education.
DOI: https://doi.org/10.37349/eemd.2026.101483
Aim:
Increased awareness of environmentally friendly and biodegradable packaging materials and the need to reduce negative and harmful interactions of food with packaging materials have driven research efforts towards edible packaging using combinations of food-based polymeric substances. Such edible packaging materials, including protein-based, carbohydrate-based, lipid-based compounds and their combinations, have revolutionised packaging perception. In this study, protein-lipid films produced from the extract obtained via hydrothermal treatment of Bambara groundnut flour were essentially modified.
Methods:
The effects of chemical modification (using formaldehyde as a cross-linking agent) and exposure to ultraviolet (UV) light on the film-forming solutions were investigated. Films from the modified and pure solutions were analysed for their barrier and mechanical properties, including water vapour permeability and elongation at break, among others. Also colour parameters of the protein-lipid films were examined.
Results:
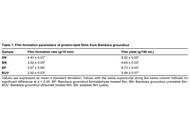
The findings revealed that the values for mechanical and barrier properties of the formed films were comparable to those of other composite films, and also presented an improvement over polysaccharide, protein, or lipid-only films. The film formation rate ranged from 2.92 ± 0.03 to 4.43 ± 0.03 g/10 min, while the film yield ranged from 5.46 ± 0.07 to 8.92 ± 0.02 g/100 mL. Water vapour permeability of the Bambara groundnut films ranged from 0.49–0.63 gm–1s–1Pa–1. The films had high opacity values. Elongation at break values for the UV-modified film (44.37) were higher than those of the unmodified film (43.07).
Conclusions:
The Bambara groundnut films had better mechanical strength compared to the reference soybean film. This indicates a possible use in the coating of brittle and light-sensitive foods.
DOI: https://doi.org/10.37349/eff.2026.1010192
Aim:
Asthma is a heterogeneous airway disease comprising distinct inflammatory phenotypes with variable clinical characteristics and treatment responses. Increasing evidence suggests that obesity-related metabolic dysfunction contributes to asthma pathogenesis; however, its relationship with eosinophilic asthma remains incompletely understood. This study aimed to evaluate metabolic dysfunction in patients with asthma and investigate its association with the eosinophilic phenotype using multiple insulin resistance-related metabolic indices.
Methods:
In this retrospective cross-sectional study, 90 patients with asthma and 131 healthy controls were included. Metabolic dysfunction was assessed using body mass index (BMI), homeostatic model assessment for insulin resistance (HOMA-IR), triglyceride-glucose (TyG) index, cholesterol-glucose (CHG) index, and metabolic score for insulin resistance (METS-IR). Eosinophilic asthma was defined as a peripheral blood eosinophil count ≥ 300 cells/µL. Group comparisons and multivariable logistic regression analyses were performed to identify factors associated with eosinophilic asthma.
Results:
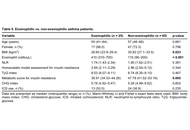
Compared with healthy controls, patients with asthma demonstrated significantly higher BMI, HOMA-IR, METS-IR, peripheral eosinophil counts, and neutrophil-to-lymphocyte ratio (NLR), indicating greater metabolic dysfunction and systemic inflammation. Among patients with asthma, 27.8% were classified as having eosinophilic asthma. Patients with eosinophilic asthma had significantly lower BMI and METS-IR values than those with non-eosinophilic asthma. In the multivariable logistic regression analysis, METS-IR showed an inverse but non-significant association with eosinophilic asthma after adjustment for age, sex, inhaled corticosteroid (ICS) use, and NLR.
Conclusions:
Metabolic dysfunction was more prevalent in patients with asthma than in healthy individuals. Although eosinophilic asthma was associated with lower BMI and METS-IR values in univariate analyses, these associations were not confirmed after adjustment for potential confounders. These findings suggest that metabolic dysfunction may contribute to asthma phenotypic heterogeneity and warrant confirmation in larger prospective studies.
DOI: https://doi.org/10.37349/eaa.2026.1009136
This article belongs to the special issue The Complex Interactions Between Lifestyles and Asthma
Axillary staging has traditionally been performed routinely in early breast cancer to provide prognostic information and guide adjuvant therapy. In the era of targeted anti-tumor therapy and biology-driven treatment selection, however, the therapeutic relevance of nodal status has diminished in selected patients with clinically node-negative disease. Recent randomized trials, including Sentinel node vs. Observation after axillary UltraSouND (SOUND), INtergroup SEntinel MAmma trial (INSEMA), and Dutch Breast Cancer Research Group (BOrstkanker Onderzoek Groep; BOOG) 2013-08, have demonstrated that omission of sentinel lymph node biopsy (SLNB) in carefully selected patients undergoing breast-conserving surgery with planned whole-breast radiotherapy (WBRT) does not compromise local or distant disease control and rarely alters adjuvant systemic or radiotherapy management. The most robust evidence applies to postmenopausal women aged ≥ 50 years with ductal tumors ≤ 2 cm, grade 1–2, hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative and clinically node-negative disease. In this biologically favorable population, the therapeutic impact of nodal findings is limited as systemic therapy and radiotherapy decisions are predominantly driven by tumor subtype and genomic risk stratification rather than minimal nodal involvement. Based on evidence from recent randomized trials and current guidelines, this position paper proposes a practical four-step framework for decision-making regarding omission of SLNB. Redefining the axilla in this context represents a precision-oncology approach to surgical de-escalation, aligning local treatment intensity with biological risk while preserving oncologic safety.
Axillary staging has traditionally been performed routinely in early breast cancer to provide prognostic information and guide adjuvant therapy. In the era of targeted anti-tumor therapy and biology-driven treatment selection, however, the therapeutic relevance of nodal status has diminished in selected patients with clinically node-negative disease. Recent randomized trials, including Sentinel node vs. Observation after axillary UltraSouND (SOUND), INtergroup SEntinel MAmma trial (INSEMA), and Dutch Breast Cancer Research Group (BOrstkanker Onderzoek Groep; BOOG) 2013-08, have demonstrated that omission of sentinel lymph node biopsy (SLNB) in carefully selected patients undergoing breast-conserving surgery with planned whole-breast radiotherapy (WBRT) does not compromise local or distant disease control and rarely alters adjuvant systemic or radiotherapy management. The most robust evidence applies to postmenopausal women aged ≥ 50 years with ductal tumors ≤ 2 cm, grade 1–2, hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative and clinically node-negative disease. In this biologically favorable population, the therapeutic impact of nodal findings is limited as systemic therapy and radiotherapy decisions are predominantly driven by tumor subtype and genomic risk stratification rather than minimal nodal involvement. Based on evidence from recent randomized trials and current guidelines, this position paper proposes a practical four-step framework for decision-making regarding omission of SLNB. Redefining the axilla in this context represents a precision-oncology approach to surgical de-escalation, aligning local treatment intensity with biological risk while preserving oncologic safety.
DOI: https://doi.org/10.37349/etat.2026.1002404
This article belongs to the special issue Breaking Boundaries in Breast Cancer Care: Emerging Controversies and Innovation in Surgical and Medical Approaches
Aim:
Rheumatoid arthritis (RA) is a chronic autoimmune disease characterized by systemic inflammation. Following the expiry of the patent for innovator tofacitinib (Xeljanz), generic tofacitinib formulations such as Tozib have become available. This study evaluated the impact of a non-medical switch from innovator tofacitinib to generic tofacitinib on disease activity and flare rates over 3 months in patients with RA.
Methods:
This retrospective multicenter observational study in Malaysia included 36 patients with RA in remission or low disease activity who underwent a non-medical switch from innovator to generic tofacitinib. Disease activity was assessed at baseline and 3 months using the Disease Activity Score-28 erythrocyte sedimentation rate (DAS28-ESR). Flare was defined as an increase in DAS28-ESR of ≥ 1.2, or ≥ 0.6 if the concurrent DAS28-ESR was ≥ 3.2.
Results:
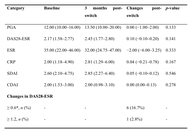
Thirty-six patients with RA who switched from reference medication to generic tofacitinib were included; 88.9% were female, with a mean age of 64.1 ± 9.4 years. Patients had longstanding disease, with a median disease duration of 15.5 years (IQR 8.8–19.0), and had received originator tofacitinib for a mean duration of 3.48 ± 1.71 years prior to switching. At 3 months post-switch, disease activity remained stable, with no significant change in median DAS28-ESR from 2.17 (IQR 1.19) to 2.45 (IQR 1.03) (p = 0.141). Although 16.7% of patients showed a DAS28-ESR increase of ≥ 0.6, none had DAS28-ESR ≥ 3.2 at 3 months. Only one patient demonstrated a DAS28-ESR change ≥ 1.2 after switching, with no new safety concerns observed.
Conclusions:
Our findings suggest that non-medical switching from reference medication to generic tofacitinib did not significantly affect short-term disease control or safety in RA patients over a 3-month follow-up period. These results provide preliminary real-world evidence supporting generic substitution; however, further studies with larger sample sizes and longer follow-up are warranted.
DOI: https://doi.org/10.37349/emd.2026.1007137
Aim:
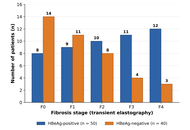
The natural history of chronic hepatitis B (CHB) is governed by hepatitis B e-antigen (HBeAg) status, viral replication, and host immunity. Reliable non-invasive markers of hepatic fibrosis and necroinflammation remain limited. The present study aimed to quantify serum interleukin-6 (IL-6), IL-8, IL-10, interferon-gamma (IFN-γ), tumor necrosis factor-alpha (TNF-α), transforming growth factor-beta (TGF-β), and microRNA-122 (miR-122) across stages of fibro-inflammatory progression in CHB, evaluate their association with HBeAg status and hepatic injury, and compare their diagnostic accuracy with conventional non-invasive indices.
Methods:
In a cross-sectional case-control study, 90 CHB patients and 100 healthy controls were enrolled at three Iraqi tertiary centers (November 2024–June 2025). Biomarkers were quantified and correlated with HBeAg status and liver stiffness measured by transient elastography (FibroScan), and compared with aspartate aminotransferase/platelet ratio index (APRI) and fibrosis-4 index (FIB-4).
Results:
Hepatitis B virus (HBV) DNA (6.5 ± 1.8 vs. 2.8 ± 1.2 log10 IU/mL; P < 0.001), the proportion with advanced fibrosis (F3–F4: 46% vs. 18%; P = 0.004), and liver stiffness (9.8 ± 5.2 vs. 7.5 ± 4.8 kPa; P = 0.04) were greater in HBeAg-positive than in HBeAg-negative patients (
Conclusions:
Persistent HBeAg expression, elevated pro-inflammatory cytokines, and suppressed miR-122 constitute an integrated molecular signature of fibro-inflammatory severity in CHB. This multi-marker panel offers an accurate, accessible, non-invasive tool for fibrosis risk stratification, particularly in resource-limited settings.
DOI: https://doi.org/10.37349/ei.2026.1003270
Background:
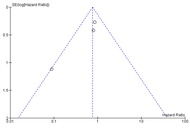
Preliminary findings from this study were previously published as a conference abstract (https://doi.org/10.1158/2326-6074.IO2025-B039). Immune checkpoint inhibitors (ICIs) have shown activity in nasopharyngeal carcinoma (NPC), but their efficacy and safety when integrated with standard chemoradiotherapy (CRT) for locally advanced NPC remain under investigation. We performed a systematic review and meta-analysis of randomized controlled trials evaluating the efficacy and safety of integrating ICIs with standard CRT-based treatment in patients with locally advanced NPC.
Methods:
MEDLINE and EMBASE were searched from inception through September 1, 2025, for English-language phase II or III randomized controlled trials evaluating ICIs plus standard therapy. Eligible studies reported efficacy outcomes, including progression-free/event-free survival (PFS/EFS), overall survival (OS), distant metastasis-free survival (DMFS), and locoregional recurrence-free survival (LRFS), and/or safety outcomes. Hazard ratios (HRs) were pooled using the generic inverse variance method, and risk ratios (RRs) for adverse events were pooled using the Mantel-Haenszel method. Fixed-effect models were used, with heterogeneity assessed using I2 statistics.
Results:
Three trials randomized 1,022 patients: CONTINUUM (n = 423), DIPPER (n = 450), and a phase II toripalimab trial (n = 149). The pooled safety population included 998 patients. ICIs significantly improved PFS/EFS [HR 0.54; 95% confidence interval (CI): 0.40–0.72; P < 0.0001], DMFS (HR 0.52; 95% CI: 0.36–0.75; P = 0.0005), and LRFS (HR 0.47; 95% CI: 0.31–0.71; P = 0.0003). OS favored the ICI arm but was not statistically significant (HR 0.77; 95% CI: 0.49–1.20; P = 0.24). ICIs increased immune related adverse events, whereas most CRT-associated locoregional and hematologic toxicities were not significantly increased.
Discussion:
Adding ICIs to standard CRT based therapy significantly improved disease control outcomes, including PFS/EFS, DMFS, and LRFS, without broadly worsening the overall CRT associated toxicity profile. Longer follow up is needed to determine whether these early disease control benefits translate into a statistically significant OS advantage.
DOI: https://doi.org/10.37349/etat.2026.1002403
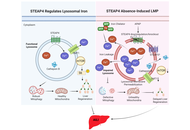
Acetaminophen (APAP) overdose is a leading cause of liver failure in Western countries and a major clinical challenge because effective treatment options remain limited for patients who present after the optimal early therapeutic window. Iron is distributed among several subcellular compartments, such as cytosol, mitochondria, ferritin, and endosomes/lysosomes. Emerging evidence indicates that intracellular iron homeostasis and organelle function may be critical during the regeneration phase for repairing liver damage. Our recent work identified the metalloreductase six-transmembrane epithelial antigen of the prostate 4 (STEAP4) as a critical regulator of lysosomal iron homeostasis and membrane integrity during the regeneration phase following APAP overdose. Hepatic STEAP4 deficiency promoted lysosomal iron accumulation and impaired hepatocyte proliferation, whereas deferiprone-mediated iron chelation restored lysosomal function and promoted liver regeneration. In this perspective, we discuss the potential of targeting lysosomal iron to promote liver repair after APAP overdose-induced liver injury, as well as the limitations and challenges.
Acetaminophen (APAP) overdose is a leading cause of liver failure in Western countries and a major clinical challenge because effective treatment options remain limited for patients who present after the optimal early therapeutic window. Iron is distributed among several subcellular compartments, such as cytosol, mitochondria, ferritin, and endosomes/lysosomes. Emerging evidence indicates that intracellular iron homeostasis and organelle function may be critical during the regeneration phase for repairing liver damage. Our recent work identified the metalloreductase six-transmembrane epithelial antigen of the prostate 4 (STEAP4) as a critical regulator of lysosomal iron homeostasis and membrane integrity during the regeneration phase following APAP overdose. Hepatic STEAP4 deficiency promoted lysosomal iron accumulation and impaired hepatocyte proliferation, whereas deferiprone-mediated iron chelation restored lysosomal function and promoted liver regeneration. In this perspective, we discuss the potential of targeting lysosomal iron to promote liver repair after APAP overdose-induced liver injury, as well as the limitations and challenges.
DOI: https://doi.org/10.37349/edd.2026.1005138
Aim:
The objective of this study is to enhance the flavor of bio-yogurt through the addition of threonine at various concentrations, and to evaluate its influence on the physicochemical, microbiological, and sensory characteristics of the product.
Methods:
To prepare bio-yogurt from cow’s milk, a probiotic starter culture comprising Bifidobacterium bifidum (Bb-12), Lactobacillus acidophilus (La-5), and Streptococcus thermophilus (ST) was used, both with and without the addition of the amino acid threonine at three concentrations: 1, 5, and 10 mg/100 mL milk. The bio-yogurt samples were then subjected to various physical, chemical, microbiological, and sensory analyses, and compared against a threonine-free control sample.
Results:
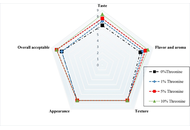
On the first day, the logarithmic counts of the probiotic starter cultures were 8.55–8.58, 8.33–8.34, and 8.53–8.57 log CFU/g for Bb-12, La-5, and ST, respectively; these values decreased to 7.01–7.03, 7.52–7.56, and 7.82–7.89 log CFU/g after 21 days. The concentrations of volatile compounds (acetaldehyde, acetoin, and diacetyl) in the threonine-enriched bio-yogurt ranged from 42.12 µg/kg to 49.40 µg/kg, 25.11 µg/kg to 29.02 µg/kg, and 3.09 µg/kg to 3.97 µg/kg, respectively, compared to the control sample, which exhibited concentrations of 38.23 µg/kg, 22.50 µg/kg, and 2.55 µg/kg, respectively. Sensory evaluation results indicated that the sample supplemented with 10 mg of threonine received the highest scores compared to the other samples.
Conclusions:
Our findings provide evidence of the value of supplementing bio-yogurt with threonine, as it does not alter its physicochemical properties. Furthermore, it does not adversely affect the total viable counts of probiotic bacteria but significantly improves the flavor profile and enhances consumer acceptability.
DOI: https://doi.org/10.37349/eff.2026.1010191
Diabetic foot ulcer (DFU) is a chronic inflammatory disease because of persistent hyperglycemia. The pathophysiology of DFUs is mediated by chronic inflammation, decreased angiogenesis, and altered extracellular matrix (ECM) remodeling. Impaired immune response halts the DFUs in the inflammatory phase of healing without progressing them to the resolution phase, resulting in delayed healing. This suggests that immunomodulation of the DFU microenvironment may be beneficial in promoting wound healing by subsiding chronic inflammation, promoting angiogenesis, and ECM remodeling. This narrative review focuses on summarizing the upcoming strategies and research in immunomodulation to promote healing in DFUs in recent years. The review has discussed the role of small molecules, exosomes, hydrogels, and natural compounds tested in preclinical trials to promote wound healing, followed by the limitations and future directions.
Diabetic foot ulcer (DFU) is a chronic inflammatory disease because of persistent hyperglycemia. The pathophysiology of DFUs is mediated by chronic inflammation, decreased angiogenesis, and altered extracellular matrix (ECM) remodeling. Impaired immune response halts the DFUs in the inflammatory phase of healing without progressing them to the resolution phase, resulting in delayed healing. This suggests that immunomodulation of the DFU microenvironment may be beneficial in promoting wound healing by subsiding chronic inflammation, promoting angiogenesis, and ECM remodeling. This narrative review focuses on summarizing the upcoming strategies and research in immunomodulation to promote healing in DFUs in recent years. The review has discussed the role of small molecules, exosomes, hydrogels, and natural compounds tested in preclinical trials to promote wound healing, followed by the limitations and future directions.
DOI: https://doi.org/10.37349/ei.2026.1003269
The precise risk factors contributing to the onset of primary biliary cholangitis (PBC) are still unclear. Although numerous findings indicate that genetic and environmental factors may contribute to PBC by disrupting immune tolerance, recent data also indicate a potential concomitance between PBC and metabolic syndrome, as well as metabolic dysfunction-associated steatotic liver disease (MASLD). In this review, we present a comprehensive examination of the available evidence on the prevalence, pathogenesis, and impact of the coexistence of PBC with MASLD and/or metabolic syndrome. Histologic observations have reported simultaneous occurrences of MASLD and PBC, and the detection of anti-mitochondrial antibodies in MASLD raises concerns about a potential underlying pathophysiologic connection. Conflicting data exist regarding the effect of coexistence of PBC and MASLD: smaller histology-based studies suggest worsened biliary damage and long-term outcomes, whereas the largest available cohorts find no independent adverse effect. Emerging evidence indicates that the cumulative burden of metabolic syndrome, rather than hepatic steatosis alone, may be the primary driver of fibrosis progression in PBC. Evidence suggests a correlation of PBC and metabolic syndrome-related conditions, such as obesity, hyperlipidemia, insulin resistance, and hypertension. This review synthesizes current knowledge on the complex interplay among these conditions and identifies key knowledge gaps that warrant further investigation, with the goal of informing screening strategies and clinical management in patients with overlapping diagnoses.
The precise risk factors contributing to the onset of primary biliary cholangitis (PBC) are still unclear. Although numerous findings indicate that genetic and environmental factors may contribute to PBC by disrupting immune tolerance, recent data also indicate a potential concomitance between PBC and metabolic syndrome, as well as metabolic dysfunction-associated steatotic liver disease (MASLD). In this review, we present a comprehensive examination of the available evidence on the prevalence, pathogenesis, and impact of the coexistence of PBC with MASLD and/or metabolic syndrome. Histologic observations have reported simultaneous occurrences of MASLD and PBC, and the detection of anti-mitochondrial antibodies in MASLD raises concerns about a potential underlying pathophysiologic connection. Conflicting data exist regarding the effect of coexistence of PBC and MASLD: smaller histology-based studies suggest worsened biliary damage and long-term outcomes, whereas the largest available cohorts find no independent adverse effect. Emerging evidence indicates that the cumulative burden of metabolic syndrome, rather than hepatic steatosis alone, may be the primary driver of fibrosis progression in PBC. Evidence suggests a correlation of PBC and metabolic syndrome-related conditions, such as obesity, hyperlipidemia, insulin resistance, and hypertension. This review synthesizes current knowledge on the complex interplay among these conditions and identifies key knowledge gaps that warrant further investigation, with the goal of informing screening strategies and clinical management in patients with overlapping diagnoses.
DOI: https://doi.org/10.37349/edd.2026.1005137
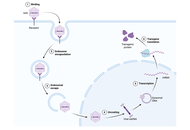
Metabolic diseases including obesity, type 2 diabetes mellitus (T2DM), and metabolic dysfunction-associated steatotic liver disease (MASLD) are increasing rapidly worldwide and contribute substantially to morbidity, mortality, and healthcare costs. Current therapies, including glucagon-like peptide-1 receptor agonists (GLP-1RAs), have transformed metabolic disease management but remain limited by high costs, adverse effects, treatment discontinuation, and the need for chronic administration. Duodenal mucosal resurfacing (DMR) and gene therapy represent potential long-term strategies for metabolic disease modulation. DMR is a minimally invasive endoscopic procedure that ablates and regenerates the duodenal mucosa, with clinical studies demonstrating improvements in glycemic control, insulin sensitivity, and liver fibrosis markers in patients with T2DM and MASLD. Although the precise mechanisms remain incompletely understood, recent evidence suggests that DMR may induce significant genetic, enteroendocrine, and gut microbiota changes involving pathways associated with glucose uptake, intestinal differentiation, and metabolic signaling. In parallel, advances in gene therapy using adeno-associated viral (AAV) vectors and lipid nanoparticles (LNPs) have shown potential in sustained modulation of insulin secretion, GLP-1 signaling, and β-cell regeneration. These approaches may overcome several limitations of conventional pharmacotherapy by providing longer-lasting therapeutic effects with fewer pharmacokinetic fluctuations. This review highlights the biological rationale underlying DMR and gene therapy, evaluates current preclinical and clinical evidence, and discusses limitations related to safety, efficacy, delivery specificity, manufacturing scalability, and ethical accessibility. Additionally, it explores the potential intersection between DMR and gene therapy, proposing that genes identified through DMR-mediated metabolic remodeling may serve as future therapeutic targets. This review also hypothesizes how DMR and gene therapy could be used together to have long-lasting complementary effects. Together, these technologies represent promising and potentially complementary strategies that could reshape the therapeutic landscape for obesity, diabetes, and MASLD.
Metabolic diseases including obesity, type 2 diabetes mellitus (T2DM), and metabolic dysfunction-associated steatotic liver disease (MASLD) are increasing rapidly worldwide and contribute substantially to morbidity, mortality, and healthcare costs. Current therapies, including glucagon-like peptide-1 receptor agonists (GLP-1RAs), have transformed metabolic disease management but remain limited by high costs, adverse effects, treatment discontinuation, and the need for chronic administration. Duodenal mucosal resurfacing (DMR) and gene therapy represent potential long-term strategies for metabolic disease modulation. DMR is a minimally invasive endoscopic procedure that ablates and regenerates the duodenal mucosa, with clinical studies demonstrating improvements in glycemic control, insulin sensitivity, and liver fibrosis markers in patients with T2DM and MASLD. Although the precise mechanisms remain incompletely understood, recent evidence suggests that DMR may induce significant genetic, enteroendocrine, and gut microbiota changes involving pathways associated with glucose uptake, intestinal differentiation, and metabolic signaling. In parallel, advances in gene therapy using adeno-associated viral (AAV) vectors and lipid nanoparticles (LNPs) have shown potential in sustained modulation of insulin secretion, GLP-1 signaling, and β-cell regeneration. These approaches may overcome several limitations of conventional pharmacotherapy by providing longer-lasting therapeutic effects with fewer pharmacokinetic fluctuations. This review highlights the biological rationale underlying DMR and gene therapy, evaluates current preclinical and clinical evidence, and discusses limitations related to safety, efficacy, delivery specificity, manufacturing scalability, and ethical accessibility. Additionally, it explores the potential intersection between DMR and gene therapy, proposing that genes identified through DMR-mediated metabolic remodeling may serve as future therapeutic targets. This review also hypothesizes how DMR and gene therapy could be used together to have long-lasting complementary effects. Together, these technologies represent promising and potentially complementary strategies that could reshape the therapeutic landscape for obesity, diabetes, and MASLD.
DOI: https://doi.org/10.37349/eemd.2026.101482
This article belongs to the special issue Innovative Strategies for Diabetes and Metabolic Disorders: Current and Future Directions
This expert position paper was developed by experts from nine Italian scientific societies with the aim of addressing in an integrated and multidisciplinary way the complex interactions between environmental and occupational exposures, climate change, and the onset of respiratory allergic diseases in the adult and paediatric population.
Air pollution is the leading environmental risk factor for human health worldwide and in Italy. According to the State of Global Air 2025, it caused 7.9 million deaths in 2023, making it the second leading risk factor for mortality. In response to growing scientific evidence, the World Health Organization (WHO) updated its Air Quality guidelines in 2021, recommending substantially lower pollutant limits than those established by previous European legislation. The new European Ambient Air Quality Directive (2024/2881/EU), which entered into force in December 2024, introduces stricter air quality standards to be achieved by 2030, while strengthening monitoring systems and public access to air quality information.
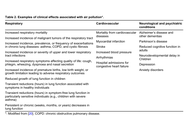
Italian epidemiological studies have consistently shown that exposure to particulate matter [PM: atmospheric PM with a diameter ≤ 10 μm (PM10) and atmospheric PM with a diameter ≤ 2.5 μm (PM2.5)], nitrogen dioxide (NO2), and ozone (O3) is associated with increased odds of rhinitis, asthma, chronic obstructive pulmonary disease (COPD), respiratory hospitalizations, and mortality both in the short and long term. These effects are mediated by inflammatory responses, oxidative stress, and molecular and epigenetic mechanisms. Children, particularly those living in densely populated urban areas with poor air quality, are among the most vulnerable populations.
Climate change, which originates from the same anthropogenic emissions driving air pollution, i.e., from energy, transport, heating, cooling, and agriculture, is further aggravating the burden of respiratory disease through more frequent heatwaves, extreme weather events, and changes in the distribution and flowering seasons of allergenic plants. Rising pollen production, combined with air pollution, enhances allergen exposure and worsens allergic respiratory diseases. Therefore, integrated monitoring of pollen, air pollutants, and meteorological conditions is essential for improving disease prediction and prevention. Particular concern is raised by thunderstorm asthma, characterized by sudden outbreaks of severe asthma following thunderstorms.
Indoor air pollution is also emerging as a major public health concern because of the growing use of chemicals and the high fraction of time spent indoors. Passive smoking, combustion products from cooking and heating, volatile organic compounds, and inadequate ventilation are associated with respiratory symptoms and impaired lung function. Schools are of particular concern, as elevated levels of carbon dioxide and PM are frequently reported in classrooms.
Occupational exposure to dust, fumes and gases remains an important cause of occupational asthma and respiratory impairment.
This document promotes operational proposals for risk prevention and mitigation, encourages scientific research and fosters the dialogue with public health and environmental authorities, in order to strengthen respiratory health protection policies.
DOI: https://doi.org/10.37349/eaa.2026.1009135
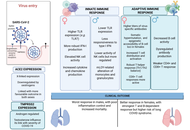
Sex- and gender-related differences profoundly influence immune responses to SARS-CoV-2 infection and vaccination but remain insufficiently considered in research and public health strategies. This review explores how sex, gender, age, and the exposome interact to shape susceptibility to coronavirus-19 disease (COVID-19), disease severity, Long COVID, and vaccine-induced immunity. Males experience higher rates of severe disease, hospitalisation, and mortality, whereas females generally mount stronger innate and adaptive immune responses, contributing to greater resilience. These differences arise from a complex interplay between biological factors and gender-related determinants, including occupational exposures, healthcare access, health-related behaviours, socioeconomic conditions, and the microbiota, which contribute to the individual exposome. This review also highlights the impact of ageing on SARS-CoV-2 immunity, highlighting the preserved immune regulation observed in centenarians, which may contribute to protection against severe COVID-19 despite advanced age. Current evidence on Long COVID is discussed, including its higher prevalence among females and the sex-specific immunological pathways that may underlie persistent symptoms. We examine age-, sex-, and gender-related differences in vaccine response, distinguishing efficacy from effectiveness. Although females generally mount stronger antibody responses, this advantage does not necessarily translate into greater clinical protection. The relative benefit of vaccination appears greater in males because of their higher baseline risk of severe disease. Finally, we discuss how exposomic factors, including lifestyle, microbiota composition, and environmental and social determinants, influence vaccine responsiveness and hesitancy. Integrating sex, gender, age, and the exposome perspectives is essential for developing more equitable and personalised strategies to prevent and manage COVID-19 and future emerging diseases.
Sex- and gender-related differences profoundly influence immune responses to SARS-CoV-2 infection and vaccination but remain insufficiently considered in research and public health strategies. This review explores how sex, gender, age, and the exposome interact to shape susceptibility to coronavirus-19 disease (COVID-19), disease severity, Long COVID, and vaccine-induced immunity. Males experience higher rates of severe disease, hospitalisation, and mortality, whereas females generally mount stronger innate and adaptive immune responses, contributing to greater resilience. These differences arise from a complex interplay between biological factors and gender-related determinants, including occupational exposures, healthcare access, health-related behaviours, socioeconomic conditions, and the microbiota, which contribute to the individual exposome. This review also highlights the impact of ageing on SARS-CoV-2 immunity, highlighting the preserved immune regulation observed in centenarians, which may contribute to protection against severe COVID-19 despite advanced age. Current evidence on Long COVID is discussed, including its higher prevalence among females and the sex-specific immunological pathways that may underlie persistent symptoms. We examine age-, sex-, and gender-related differences in vaccine response, distinguishing efficacy from effectiveness. Although females generally mount stronger antibody responses, this advantage does not necessarily translate into greater clinical protection. The relative benefit of vaccination appears greater in males because of their higher baseline risk of severe disease. Finally, we discuss how exposomic factors, including lifestyle, microbiota composition, and environmental and social determinants, influence vaccine responsiveness and hesitancy. Integrating sex, gender, age, and the exposome perspectives is essential for developing more equitable and personalised strategies to prevent and manage COVID-19 and future emerging diseases.
DOI: https://doi.org/10.37349/ei.2026.1003268
Aim:
Antinuclear antibodies (ANAs) are important in diagnosing systemic autoimmune rheumatic diseases (SARDs), and the HEp-2 cell indirect immunofluorescence assay (HEp-2 IFA) remains the gold standard for their detection. This study evaluates the utility and optimal cutoff of the EliA connective tissue disease Screen (CTD Screen), an enzyme immunoassay, as a complementary automated method for ANA detection.
Methods:
A total of 694 samples (347 HEp-2 IFA positive and 347 HEp-2 IFA negative) were analysed using the CTD Screen assay. Samples that were positive by both methods were further tested using a line immunoassay (LIA) to detect specific ANAs. Diagnostic accuracy was assessed with a 95% confidence interval (95% CI) using sensitivity, specificity, predictive values, Cohen’s kappa (κ), and receiver operating characteristic (ROC) analysis.
Results:
With the manufacturer’s cutoff, CTD Screen sensitivity and specificity were 73.9% (95% CI 69.0–78.3) and 92.6% (95% CI 89.2–95.0), respectively. The optimized in-house cutoff improved sensitivity to 81.5% (95% CI 77.1–85.3) and specificity to 85.6% (95% CI 81.4–89.0). The assay demonstrated substantial agreement with HEp-2 IFA (κ = 0.683) and an area under the ROC curve of 0.845 (95% CI 0.814–0.876). LIA confirmed the presence of antibodies in 89.9% of CTD Screen-positive samples. Disease-specific analysis demonstrated the highest sensitivity for systemic sclerosis (97.4%) and the best accuracy for mixed CTD [area under the curve (AUC) = 0.900].
Conclusions:
CTD Screen shows substantial agreement with HEp-2 IFA and good diagnostic accuracy; however, it is best used within a tiered diagnostic approach that incorporates confirmatory assays and clinical correlation rather than as a standalone test.
DOI: https://doi.org/10.37349/ei.2026.1003267
