


 Previous
Aim:
Asthma is a heterogeneous airway disease comprising distinct inflammatory phenotypes with variable clinical characteristics and treatment responses. Increasing evidence suggests that obesity-related metabolic dysfunction contributes to asthma pathogenesis; however, its relationship with eosinophilic asthma remains incompletely understood. This study aimed to evaluate metabolic dysfunction in patients with asthma and investigate its association with the eosinophilic phenotype using multiple insulin resistance-related metabolic indices.
Methods:
In this retrospective cross-sectional study, 90 patients with asthma and 131 healthy controls were included. Metabolic dysfunction was assessed using body mass index (BMI), homeostatic model assessment for insulin resistance (HOMA-IR), triglyceride-glucose (TyG) index, cholesterol-glucose (CHG) index, and metabolic score for insulin resistance (METS-IR). Eosinophilic asthma was defined as a peripheral blood eosinophil count ≥ 300 cells/µL. Group comparisons and multivariable logistic regression analyses were performed to identify factors associated with eosinophilic asthma.
Results:
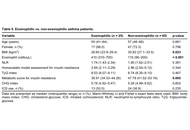
Compared with healthy controls, patients with asthma demonstrated significantly higher BMI, HOMA-IR, METS-IR, peripheral eosinophil counts, and neutrophil-to-lymphocyte ratio (NLR), indicating greater metabolic dysfunction and systemic inflammation. Among patients with asthma, 27.8% were classified as having eosinophilic asthma. Patients with eosinophilic asthma had significantly lower BMI and METS-IR values than those with non-eosinophilic asthma. In the multivariable logistic regression analysis, METS-IR showed an inverse but non-significant association with eosinophilic asthma after adjustment for age, sex, inhaled corticosteroid (ICS) use, and NLR.
Conclusions:
Metabolic dysfunction was more prevalent in patients with asthma than in healthy individuals. Although eosinophilic asthma was associated with lower BMI and METS-IR values in univariate analyses, these associations were not confirmed after adjustment for potential confounders. These findings suggest that metabolic dysfunction may contribute to asthma phenotypic heterogeneity and warrant confirmation in larger prospective studies.
DOI: https://doi.org/10.37349/eaa.2026.1009136
This article belongs to the special issue The Complex Interactions Between Lifestyles and Asthma


This expert position paper was developed by experts from nine Italian scientific societies with the aim of addressing in an integrated and multidisciplinary way the complex interactions between environmental and occupational exposures, climate change, and the onset of respiratory allergic diseases in the adult and paediatric population.
Air pollution is the leading environmental risk factor for human health worldwide and in Italy. According to the State of Global Air 2025, it caused 7.9 million deaths in 2023, making it the second leading risk factor for mortality. In response to growing scientific evidence, the World Health Organization (WHO) updated its Air Quality guidelines in 2021, recommending substantially lower pollutant limits than those established by previous European legislation. The new European Ambient Air Quality Directive (2024/2881/EU), which entered into force in December 2024, introduces stricter air quality standards to be achieved by 2030, while strengthening monitoring systems and public access to air quality information.
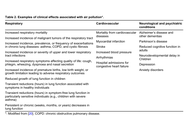
Italian epidemiological studies have consistently shown that exposure to particulate matter [PM: atmospheric PM with a diameter ≤ 10 μm (PM10) and atmospheric PM with a diameter ≤ 2.5 μm (PM2.5)], nitrogen dioxide (NO2), and ozone (O3) is associated with increased odds of rhinitis, asthma, chronic obstructive pulmonary disease (COPD), respiratory hospitalizations, and mortality both in the short and long term. These effects are mediated by inflammatory responses, oxidative stress, and molecular and epigenetic mechanisms. Children, particularly those living in densely populated urban areas with poor air quality, are among the most vulnerable populations.
Climate change, which originates from the same anthropogenic emissions driving air pollution, i.e., from energy, transport, heating, cooling, and agriculture, is further aggravating the burden of respiratory disease through more frequent heatwaves, extreme weather events, and changes in the distribution and flowering seasons of allergenic plants. Rising pollen production, combined with air pollution, enhances allergen exposure and worsens allergic respiratory diseases. Therefore, integrated monitoring of pollen, air pollutants, and meteorological conditions is essential for improving disease prediction and prevention. Particular concern is raised by thunderstorm asthma, characterized by sudden outbreaks of severe asthma following thunderstorms.
Indoor air pollution is also emerging as a major public health concern because of the growing use of chemicals and the high fraction of time spent indoors. Passive smoking, combustion products from cooking and heating, volatile organic compounds, and inadequate ventilation are associated with respiratory symptoms and impaired lung function. Schools are of particular concern, as elevated levels of carbon dioxide and PM are frequently reported in classrooms.
Occupational exposure to dust, fumes and gases remains an important cause of occupational asthma and respiratory impairment.
This document promotes operational proposals for risk prevention and mitigation, encourages scientific research and fosters the dialogue with public health and environmental authorities, in order to strengthen respiratory health protection policies.
DOI: https://doi.org/10.37349/eaa.2026.1009135
Aim:
Asthma exacerbations are associated with significant morbidity and mortality, yet identifying individuals at high risk of an exacerbation remains challenging in community settings. Pharmacists, with access to pharmacy dispensing systems, are well positioned to address this gap. This study aimed to determine whether the utilization of pharmacy electronic communication can assist community pharmacists in identifying people with asthma, within the patient cohort, who are at high risk of exacerbation.
Methods:
A retrospective analysis of de-identified data from 45 community pharmacies in Australia and New Zealand was conducted using data from reCare software. Patients with a respiratory medication dispensed in the previous 12 months who had consented to electronic communication were invited to complete a five-item questionnaire. Patients who visited a General Practitioner (GP)/hospital, used oral corticosteroid (OCS), or purchased ≥ 3 short-acting beta-agonist (SABA) inhalers for their asthma in the past year were considered at high risk of exacerbation. Responses were linked to patients’ dispensing records for pharmacist review and referral.
Results:
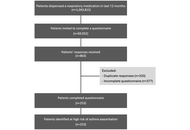
Of 1,043,815 eligible patients, 69,932 received invitations; 863 responded, and 253 completed the questionnaire fully. All those who completed the questionnaire met the criteria for being at high risk of asthma exacerbation. Among these, 55.7% reported GP/hospital visits, 100% used OCS, and 69.5% purchased ≥ 3 SABA inhalers. Poor adherence was reported by 58.1%. SABA overuse was significantly associated with GP/hospital visits (p < 0.01) and poor adherence (p < 0.01).
Conclusions:
Electronic communication integrated with data in pharmacy dispensing systems can support pharmacists in understanding individuals’ exacerbation risk and the need to refer people with asthma. Patient consultation regarding preferred communication methods is critical before broader implementation; validation of screening tools is also recommended.
DOI: https://doi.org/10.37349/eaa.2026.1009134
This article belongs to the special issue Allergy and Asthma in the Digital Age
Chronic spontaneous urticaria (CSU) is a debilitating condition characterized by recurrent wheals and/or angioedema lasting more than six weeks without identifiable triggers. The global prevalence is increasing, and patients with resistance to antihistamine therapies experience a significantly reduced quality of life (QoL). Omalizumab, a monoclonal anti-IgE antibody, represents the cornerstone of second-line therapy in antihistamine-refractory CSU. With the expiration of the originator patent, biosimilar versions of omalizumab are being developed and introduced, potentially improving access and reducing healthcare costs. This narrative review critically summarizes the currently available evidence on Omlyclo® (omalizumab-igec; CT-P39, Celltrion), including analytical comparability studies, regulatory evidence and the pivotal phase III clinical trial in CSU, while discussing regulatory, clinical and pharmacoeconomic implications. Available evidence supports comparable efficacy, safety and immunogenicity to reference omalizumab, although long-term real-world data remain limited. This review discusses the emerging role of omalizumab biosimilars in CSU, highlighting current evidence, remaining knowledge gaps and future perspectives.
Chronic spontaneous urticaria (CSU) is a debilitating condition characterized by recurrent wheals and/or angioedema lasting more than six weeks without identifiable triggers. The global prevalence is increasing, and patients with resistance to antihistamine therapies experience a significantly reduced quality of life (QoL). Omalizumab, a monoclonal anti-IgE antibody, represents the cornerstone of second-line therapy in antihistamine-refractory CSU. With the expiration of the originator patent, biosimilar versions of omalizumab are being developed and introduced, potentially improving access and reducing healthcare costs. This narrative review critically summarizes the currently available evidence on Omlyclo® (omalizumab-igec; CT-P39, Celltrion), including analytical comparability studies, regulatory evidence and the pivotal phase III clinical trial in CSU, while discussing regulatory, clinical and pharmacoeconomic implications. Available evidence supports comparable efficacy, safety and immunogenicity to reference omalizumab, although long-term real-world data remain limited. This review discusses the emerging role of omalizumab biosimilars in CSU, highlighting current evidence, remaining knowledge gaps and future perspectives.
DOI: https://doi.org/10.37349/eaa.2026.1009133
This article belongs to the special issue Bridging Experimental and Translational Allergology
Biologic therapies have transformed care for people with severe asthma, yet treatment response has traditionally been assessed using clinician-derived measures, including lung function, exacerbation rates, and oral corticosteroid use. These metrics, while clinically important, frequently fail to capture what matters most to patients: their ability to participate in daily life, maintain relationships, and sustain work and social roles. The publication of the Core Outcome Measures Set for Severe Asthma (COMSA) and the subsequent CompOsite iNdexes For Response in asthMa (CONFiRM) composite score mark a shift towards patient-centred measurement of treatment response in severe asthma. Rheumatoid arthritis (RA) and inflammatory bowel disease (IBD) travelled this path decades earlier. Both conditions adopted composite scoring tools, such as the Disease Activity Score-28 (DAS28) and the Mayo Score, that incorporated Patient-Reported Outcome Measures (PROMs) alongside objective markers. Initiatives like Outcome Measures in Rheumatology (OMERACT) in RA and Selecting Therapeutic Targets in Inflammatory Bowel Disease (STRIDE) in IBD demonstrate that sustained, multidisciplinary collaboration between patients, clinicians, regulators, and industry can successfully embed PROMs into clinical trials and routine care. We argue that timely integration of health-related quality of life measures into clinical trials and practice requires electronic data collection, regulatory endorsement of PROMs as co-primary endpoints, and genuine patient partnership in research, beyond tokenism. By learning from parallel specialties, the asthma community can build a model of care that reflects what truly matters to those living with the disease.
Biologic therapies have transformed care for people with severe asthma, yet treatment response has traditionally been assessed using clinician-derived measures, including lung function, exacerbation rates, and oral corticosteroid use. These metrics, while clinically important, frequently fail to capture what matters most to patients: their ability to participate in daily life, maintain relationships, and sustain work and social roles. The publication of the Core Outcome Measures Set for Severe Asthma (COMSA) and the subsequent CompOsite iNdexes For Response in asthMa (CONFiRM) composite score mark a shift towards patient-centred measurement of treatment response in severe asthma. Rheumatoid arthritis (RA) and inflammatory bowel disease (IBD) travelled this path decades earlier. Both conditions adopted composite scoring tools, such as the Disease Activity Score-28 (DAS28) and the Mayo Score, that incorporated Patient-Reported Outcome Measures (PROMs) alongside objective markers. Initiatives like Outcome Measures in Rheumatology (OMERACT) in RA and Selecting Therapeutic Targets in Inflammatory Bowel Disease (STRIDE) in IBD demonstrate that sustained, multidisciplinary collaboration between patients, clinicians, regulators, and industry can successfully embed PROMs into clinical trials and routine care. We argue that timely integration of health-related quality of life measures into clinical trials and practice requires electronic data collection, regulatory endorsement of PROMs as co-primary endpoints, and genuine patient partnership in research, beyond tokenism. By learning from parallel specialties, the asthma community can build a model of care that reflects what truly matters to those living with the disease.
DOI: https://doi.org/10.37349/eaa.2026.1009132
This article belongs to the special issue Allergic Asthma - New Insights
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS)/toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP), are T-cell-mediated hypersensitivity reactions. Although their causative agents and acute manifestations are well characterized, limited data exist regarding their long-term sequelae, particularly the subsequent development of autoimmune disease. A comprehensive literature review was conducted using PubMed. Given the limited published evidence regarding autoimmune sequelae following SCARs, the search strategy was intentionally broad and included studies published from the 1980s through 2025. Among SCARs, DRESS demonstrated the strongest association with autoimmune disease, including type 1 diabetes mellitus, thyroiditis, bullous pemphigoid, thrombotic thrombocytopenic purpura, autoimmune hemolytic anemia, vitiligo, and systemic lupus erythematosus. Proposed pathogenic mechanisms include viral reactivation and persistent immune dysregulation. SJS/TEN has also been associated with fulminant type 1 diabetes mellitus, autoimmune thyroid disease, systemic lupus erythematosus, Sjögren’s syndrome, and the development of positive antinuclear antibodies. In contrast, evidence linking AGEP to autoimmune disease remains limited and conflicting, although associations with CARD14 mutations and polyarteritis nodosa have been reported. Evidence supporting post-SCAR autoimmunity, particularly following DRESS, is growing but remains largely based on case reports and small observational studies. SCARs, particularly DRESS and to a lesser extent SJS/TEN, may predispose patients to autoimmune disease through persistent immune dysregulation and viral reactivation. In contrast, no clear association has been established between AGEP and autoimmune disease. Clinicians should remain vigilant for potential long-term autoimmune sequelae following SCARs and consider multidisciplinary follow-up when clinically appropriate. Further prospective studies are needed to better characterize the underlying mechanisms, incidence, and optimal long-term surveillance strategies associated with these conditions.
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS)/toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP), are T-cell-mediated hypersensitivity reactions. Although their causative agents and acute manifestations are well characterized, limited data exist regarding their long-term sequelae, particularly the subsequent development of autoimmune disease. A comprehensive literature review was conducted using PubMed. Given the limited published evidence regarding autoimmune sequelae following SCARs, the search strategy was intentionally broad and included studies published from the 1980s through 2025. Among SCARs, DRESS demonstrated the strongest association with autoimmune disease, including type 1 diabetes mellitus, thyroiditis, bullous pemphigoid, thrombotic thrombocytopenic purpura, autoimmune hemolytic anemia, vitiligo, and systemic lupus erythematosus. Proposed pathogenic mechanisms include viral reactivation and persistent immune dysregulation. SJS/TEN has also been associated with fulminant type 1 diabetes mellitus, autoimmune thyroid disease, systemic lupus erythematosus, Sjögren’s syndrome, and the development of positive antinuclear antibodies. In contrast, evidence linking AGEP to autoimmune disease remains limited and conflicting, although associations with CARD14 mutations and polyarteritis nodosa have been reported. Evidence supporting post-SCAR autoimmunity, particularly following DRESS, is growing but remains largely based on case reports and small observational studies. SCARs, particularly DRESS and to a lesser extent SJS/TEN, may predispose patients to autoimmune disease through persistent immune dysregulation and viral reactivation. In contrast, no clear association has been established between AGEP and autoimmune disease. Clinicians should remain vigilant for potential long-term autoimmune sequelae following SCARs and consider multidisciplinary follow-up when clinically appropriate. Further prospective studies are needed to better characterize the underlying mechanisms, incidence, and optimal long-term surveillance strategies associated with these conditions.
DOI: https://doi.org/10.37349/eaa.2026.1009131
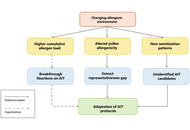
Climate change is reshaping the epidemiology and severity of allergic disease through mechanisms that extend beyond increased pollen exposure. Pollen seasons are lengthening, annual allergen loads are rising, and tropospheric ozone is chemically modifying pollen proteins in ways that enhance their allerginicity. The geographic expansion of allergenic plant species is generating new sensitization patterns in populations with no prior exposure history, and extreme meteorological events are precipitating acute asthma in individuals who previously had only rhinitis. In this evolving landscape, allergen immunotherapy (AIT), the only intervention capable of modifying the natural course of IgE-mediated allergic disease, becomes not less relevant, but more. Climate change strengthens the case for earlier and broader AIT prescription, calls for updated patient selection criteria and maintenance protocols, and demands investment in extract standardization. We argue that climate change is not merely a contextual backdrop for allergy practice but an active clinical variable that elevates the role of AIT as both an individual treatment and a population-level prevention strategy. A focused research agenda at the climate-immunotherapy interface is both timely and necessary, given a disease burden that is projected to grow.
Climate change is reshaping the epidemiology and severity of allergic disease through mechanisms that extend beyond increased pollen exposure. Pollen seasons are lengthening, annual allergen loads are rising, and tropospheric ozone is chemically modifying pollen proteins in ways that enhance their allerginicity. The geographic expansion of allergenic plant species is generating new sensitization patterns in populations with no prior exposure history, and extreme meteorological events are precipitating acute asthma in individuals who previously had only rhinitis. In this evolving landscape, allergen immunotherapy (AIT), the only intervention capable of modifying the natural course of IgE-mediated allergic disease, becomes not less relevant, but more. Climate change strengthens the case for earlier and broader AIT prescription, calls for updated patient selection criteria and maintenance protocols, and demands investment in extract standardization. We argue that climate change is not merely a contextual backdrop for allergy practice but an active clinical variable that elevates the role of AIT as both an individual treatment and a population-level prevention strategy. A focused research agenda at the climate-immunotherapy interface is both timely and necessary, given a disease burden that is projected to grow.
DOI: https://doi.org/10.37349/eaa.2026.1009130
This article belongs to the special issue Climate Change, Allergy, and Immunotherapy
Aim:
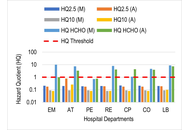
Indoor air quality (IAQ) is a critical component of occupational health in hospitals, where healthcare workers face exposure to particulates and clinical chemical vapours. Prolonged exposure to these environments is linked to an increased incidence of chronic respiratory conditions. This study aimed to quantify the indoor concentrations of particulate matter (PM2.5 and PM10), formaldehyde (HCHO), and total volatile organic compounds (TVOCs) in public and private tertiary healthcare facilities in Benin City, Nigeria, and to evaluate the associated non−carcinogenic and carcinogenic health risks for personnel.
Methods:
IAQ was monitored in triplicate at high-occupancy sampling points over an eight-week period using handheld digital monitors. Health risks were assessed using hazard quotient (HQ) and incremental lifetime cancer risk (ILCR) models. Additionally, a structured questionnaire was administered to 152 hospital workers to correlate environmental data with self-reported respiratory symptoms.
Results:
The PM2.5 and TVOC levels frequently exceeded the WHO guidelines in both facilities. The private facility exhibited alarming HCHO concentrations, particularly in the emergency (HQ = 10.04) and laboratory (HQ = 8.86) units, indicating risks up to ten times the safety threshold. Similarly, the ILCR exceeded the 1.0 × 10⁻⁴ threshold at the highest exposure site, reaching a peak of 1.49 × 10⁻⁴. Coughing (78.3%) was the most prevalent symptom. Notably, compared with workers in the private sector, workers in public hospitals faced significantly greater respiratory burdens, with an adjusted odds ratio (AOR) of 3.009 (95% CI: 1.277–7.088) for persistent cough and an AOR of 2.681 (95% CI: 1.093–6.578) for chest pain.
Conclusions:
Hospital indoor air poses severe toxicological and carcinogenic risks. Immediate implementation of advanced mechanical ventilation and specialized filtration is needed to safeguard healthcare personnel.
DOI: https://doi.org/10.37349/eaa.2026.1009129
This article belongs to the special issue Environment, Infectious Diseases, and Allergy
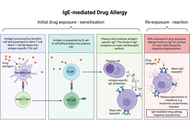
Drug allergies are reported in 10% of children, with non-steroidal anti-inflammatory drugs (NSAIDs) and β-lactam antibiotics being the most frequently implicated; while antibiotic allergy is more commonly reported in early childhood, NSAIDs are the leading cause of confirmed drug hypersensitivity in older children and adolescents. Paracetamol and ibuprofen are widely used in paediatrics for their analgesic, anti-pyretic, and anti-inflammatory effects via their inhibitory action on cyclooxygenase (COX) enzymes. Whilst considered generally safe, hypersensitivity reactions (HSR) to NSAIDs are the leading causes of drug-induced hypersensitivity in children and the most frequent cause of anaphylaxis. NSAID hypersensitivity is classified into immunologic (allergic) and non-immunologic (non-allergic) reactions, typically occurring in selective responders who react to a single NSAID or structurally related group without cross-intolerance. Reactions may be immediate (within one hour with urticaria, angioedema, anaphylaxis), or delayed (hours to days later). Paediatric presentations overlap with adult but pose unique diagnostic and management challenges, compounded by limited paediatric-specific evidence and variable international practice. In 2018, the European Network of Drug Allergy and the European Academy of Allergy and Clinical Immunology published a consensus-based position paper outlining recommendations for diagnosis and management in children and adolescents. A review of 12 recent paediatric studies supports current classification frameworks and reinforces oral provocation testing as the diagnostic gold standard, with prospective study designs and multicentre recruitment that enhance validity and generalisability, highlighting that cutaneous symptoms were the most common presentation and supervised graded drug challenges shown to be safe and clinically informative. Despite these advances, significant global variability persists, and current approaches are still largely guided by expert consensus rather than robust, standardised evidence. This highlights the need for internationally harmonised guidelines, large prospective studies, improved risk stratification, and the development of reliable adjunctive diagnostic tools, particularly given the limited utility and validation of skin testing in this population.
Drug allergies are reported in 10% of children, with non-steroidal anti-inflammatory drugs (NSAIDs) and β-lactam antibiotics being the most frequently implicated; while antibiotic allergy is more commonly reported in early childhood, NSAIDs are the leading cause of confirmed drug hypersensitivity in older children and adolescents. Paracetamol and ibuprofen are widely used in paediatrics for their analgesic, anti-pyretic, and anti-inflammatory effects via their inhibitory action on cyclooxygenase (COX) enzymes. Whilst considered generally safe, hypersensitivity reactions (HSR) to NSAIDs are the leading causes of drug-induced hypersensitivity in children and the most frequent cause of anaphylaxis. NSAID hypersensitivity is classified into immunologic (allergic) and non-immunologic (non-allergic) reactions, typically occurring in selective responders who react to a single NSAID or structurally related group without cross-intolerance. Reactions may be immediate (within one hour with urticaria, angioedema, anaphylaxis), or delayed (hours to days later). Paediatric presentations overlap with adult but pose unique diagnostic and management challenges, compounded by limited paediatric-specific evidence and variable international practice. In 2018, the European Network of Drug Allergy and the European Academy of Allergy and Clinical Immunology published a consensus-based position paper outlining recommendations for diagnosis and management in children and adolescents. A review of 12 recent paediatric studies supports current classification frameworks and reinforces oral provocation testing as the diagnostic gold standard, with prospective study designs and multicentre recruitment that enhance validity and generalisability, highlighting that cutaneous symptoms were the most common presentation and supervised graded drug challenges shown to be safe and clinically informative. Despite these advances, significant global variability persists, and current approaches are still largely guided by expert consensus rather than robust, standardised evidence. This highlights the need for internationally harmonised guidelines, large prospective studies, improved risk stratification, and the development of reliable adjunctive diagnostic tools, particularly given the limited utility and validation of skin testing in this population.
DOI: https://doi.org/10.37349/eaa.2026.1009128
This article belongs to the special issue Asthma, Allergies, and Respiratory Infections in Pediatric Age
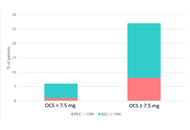
Eosinophilic granulomatosis with polyangiitis (EGPA) is a rare systemic vasculitis with heterogeneous clinical manifestations. Identifying reliable biomarkers is crucial to predicting disease evolution and guiding therapy. We analyzed clinical, biological, and functional data from 33 patients with EGPA in the vasculitic phase. Blood eosinophil count (BEC), eosinophilic cationic protein (ECP), antineutrophil cytoplasmic antibodies (ANCAs), specific IgE to staphylococcal enterotoxins (SE-IgE), and serum free light chains (FLCs) were evaluated. Severe eosinophilic asthma (SEA) and chronic rhinosinusitis with nasal polyps (CRSwNPs) were present in 100% and 88.5% of patients, respectively. Median BEC was 1950 cells/mm3, with elevated ECP (60.0 µg/L). SE-IgE was detected in 54.2% of patients. A significant negative correlation emerged between λ FLCs and oral corticosteroid (OCS) dose (r = –0.58, p = 0.009). Forced expiratory volume in 1 second (FEV1) was significantly lower in C-ANCA+ patients (p = 0.006). ECP and SE-IgE may serve as markers of eosinophilic activity and epithelial barrier damage in EGPA. λ FLCs might be a useful indicator of OCS exposure and treatment response. These biomarkers could support the evaluation of disease evolution and treatment response.
Eosinophilic granulomatosis with polyangiitis (EGPA) is a rare systemic vasculitis with heterogeneous clinical manifestations. Identifying reliable biomarkers is crucial to predicting disease evolution and guiding therapy. We analyzed clinical, biological, and functional data from 33 patients with EGPA in the vasculitic phase. Blood eosinophil count (BEC), eosinophilic cationic protein (ECP), antineutrophil cytoplasmic antibodies (ANCAs), specific IgE to staphylococcal enterotoxins (SE-IgE), and serum free light chains (FLCs) were evaluated. Severe eosinophilic asthma (SEA) and chronic rhinosinusitis with nasal polyps (CRSwNPs) were present in 100% and 88.5% of patients, respectively. Median BEC was 1950 cells/mm3, with elevated ECP (60.0 µg/L). SE-IgE was detected in 54.2% of patients. A significant negative correlation emerged between λ FLCs and oral corticosteroid (OCS) dose (r = –0.58, p = 0.009). Forced expiratory volume in 1 second (FEV1) was significantly lower in C-ANCA+ patients (p = 0.006). ECP and SE-IgE may serve as markers of eosinophilic activity and epithelial barrier damage in EGPA. λ FLCs might be a useful indicator of OCS exposure and treatment response. These biomarkers could support the evaluation of disease evolution and treatment response.
DOI: https://doi.org/10.37349/eaa.2026.1009127
This article belongs to the special issue Environment, Infectious Diseases, and Allergy
Aim:
This study aimed to assess the prevalence and patterns of aeroallergen sensitisation in steroid-naïve, newly diagnosed adult patients with bronchial asthma using skin prick test (SPT), and to examine its association with lung function parameters measured by oscillometry and spirometry.
Methods:
Consecutive adult patients with bronchial asthma who were naïve to systemic and inhaled corticosteroids were recruited. Following a detailed clinical history and blood investigations, lung function was assessed using oscillometry and spirometry. SPT was performed using a panel of 13 aeroallergens in accordance with established guidelines. Based on SPT results, patients were stratified into two groups: atopic asthma (sensitisation to ≥ 1 allergen) and non-atopic asthma (no sensitisation). Demographic characteristics, blood parameters, and lung function parameters were compared between the two groups.
Results:
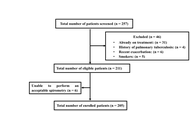
Of 257 patients screened, 205 were enrolled (59% men; mean age 36.9 years). Allergic rhinitis was present in 58% of patients, and 69.8% had atopic asthma (95% CI 62.9–75.6). Sensitisation was most common to house dust mites (47.8%), followed by cockroach (37.6%) and weed pollen (29.8%). Atopy was more prevalent in men than in women and was associated with higher serum total IgE levels. Peripheral blood eosinophil counts, oscillometric parameters, severity of airflow obstruction, and bronchodilator responses did not differ significantly between atopic and non-atopic patients.
Conclusions:
The majority of asthma patients exhibited sensitisation to one or more aeroallergens. Despite differences in immunopathogenesis, no significant differences in oscillometric parameters were observed between atopic and non-atopic asthma, suggesting that atopic status has a limited influence on the severity of small airway dysfunction.
DOI: https://doi.org/10.37349/eaa.2026.1009126
Netherton syndrome (NS) is a rare autosomal recessive disorder caused by SPINK5 mutations, leading to impaired skin barrier function and severe atopic manifestations. Hereditary angioedema due to C1 inhibitor deficiency (HAE-C1-INH) is a rare autosomal dominant disorder characterised by recurrent bradykinin-mediated angioedema. Their coexistence has not previously been reported, and evidence on combined biologic therapy is lacking. We report a 30-year-old woman with confirmed NS and long-standing HAE-C1-INH presenting with severe pruritus, xerosis, widespread eczema, elevated IgE, eosinophilia, and trichorrhexis invaginata. Dupilumab was initiated to target T helper (Th)2-mediated inflammation. Due to persistent angioedema attacks despite prior prophylaxis, lanadelumab was introduced. Dupilumab improved eczema severity, hyperkeratosis, and hair abnormalities over 13 months. Lanadelumab reduced angioedema attacks by 88.50%, allowing dose spacing while maintaining disease control. No adverse effects or drug interactions were observed. This is the first reported case of NS and HAE-C1-INH successfully treated with dual biologic therapy. Targeting distinct immunological pathways simultaneously may represent an effective and safe strategy for complex rare disease phenotypes.
Netherton syndrome (NS) is a rare autosomal recessive disorder caused by SPINK5 mutations, leading to impaired skin barrier function and severe atopic manifestations. Hereditary angioedema due to C1 inhibitor deficiency (HAE-C1-INH) is a rare autosomal dominant disorder characterised by recurrent bradykinin-mediated angioedema. Their coexistence has not previously been reported, and evidence on combined biologic therapy is lacking. We report a 30-year-old woman with confirmed NS and long-standing HAE-C1-INH presenting with severe pruritus, xerosis, widespread eczema, elevated IgE, eosinophilia, and trichorrhexis invaginata. Dupilumab was initiated to target T helper (Th)2-mediated inflammation. Due to persistent angioedema attacks despite prior prophylaxis, lanadelumab was introduced. Dupilumab improved eczema severity, hyperkeratosis, and hair abnormalities over 13 months. Lanadelumab reduced angioedema attacks by 88.50%, allowing dose spacing while maintaining disease control. No adverse effects or drug interactions were observed. This is the first reported case of NS and HAE-C1-INH successfully treated with dual biologic therapy. Targeting distinct immunological pathways simultaneously may represent an effective and safe strategy for complex rare disease phenotypes.
DOI: https://doi.org/10.37349/eaa.2026.1009125
Obesity is a determinant of the risk of developing various diseases, including asthma. It can also contribute to asthma severity. Obvious determinants of the risk of developing obesity and conditions associated with obesity are the diet an individual consumes and their energy expenditure, as determined by activity. Therefore, diet and exercise are important non-pharmacological components in the management and prevention of many diseases. Several individual elements in diet, including certain fatty acids and vitamins, as well as types of diets, notably the Mediterranean diet, have been studied in asthmatic patients, but the literature is not consistent. This review explores the relationship between asthma and obesity, exercise, and multiple dietary components and regimens, including the Mediterranean diet; polyunsaturated fats; vitamins A, C, D, and E; flavonoids; probiotics; and sodium intake in the published randomized clinical trials. Overall, the data have many shortcomings, but there is no single component of diet that is consistently associated with improved asthma outcomes, nor any component found to be clearly harmful. However, a diet that helps an individual lose weight may indirectly improve their lung function and asthma control, even if the diet itself does not impact asthma outcomes. Exercise, now known to be safe and widely recommended in asthma, has various forms. This review looked at meta-analyses, as well as recently published data addressing this question, categorizing exercise as aerobic activity, pulmonary rehabilitation, and yoga. The most evidence for benefit is for aerobic exercise, but yoga also has potential for modest improvement in asthma symptoms. There is conflicting data as to whether supervised exercise programs are superior to unsupervised physical activity. Overall, exercise is helpful in asthma, but it is still unclear how much exercise should be done, and this should be tailored to each individual.
Obesity is a determinant of the risk of developing various diseases, including asthma. It can also contribute to asthma severity. Obvious determinants of the risk of developing obesity and conditions associated with obesity are the diet an individual consumes and their energy expenditure, as determined by activity. Therefore, diet and exercise are important non-pharmacological components in the management and prevention of many diseases. Several individual elements in diet, including certain fatty acids and vitamins, as well as types of diets, notably the Mediterranean diet, have been studied in asthmatic patients, but the literature is not consistent. This review explores the relationship between asthma and obesity, exercise, and multiple dietary components and regimens, including the Mediterranean diet; polyunsaturated fats; vitamins A, C, D, and E; flavonoids; probiotics; and sodium intake in the published randomized clinical trials. Overall, the data have many shortcomings, but there is no single component of diet that is consistently associated with improved asthma outcomes, nor any component found to be clearly harmful. However, a diet that helps an individual lose weight may indirectly improve their lung function and asthma control, even if the diet itself does not impact asthma outcomes. Exercise, now known to be safe and widely recommended in asthma, has various forms. This review looked at meta-analyses, as well as recently published data addressing this question, categorizing exercise as aerobic activity, pulmonary rehabilitation, and yoga. The most evidence for benefit is for aerobic exercise, but yoga also has potential for modest improvement in asthma symptoms. There is conflicting data as to whether supervised exercise programs are superior to unsupervised physical activity. Overall, exercise is helpful in asthma, but it is still unclear how much exercise should be done, and this should be tailored to each individual.
DOI: https://doi.org/10.37349/eaa.2026.1009124
This article belongs to the special issue The Complex Interactions Between Lifestyles and Asthma
Pollen-related allergic diseases, including allergic rhinoconjunctivitis and asthma, affect a growing proportion of the population and have substantial consequences for quality of life and healthcare systems. Conventional pollen forecasts, which rely on fixed pollen traps and meteorological data, are limited in spatial granularity, real-time responsiveness, and individual relevance. Recent advances in artificial intelligence (AI) and machine learning (ML) offer a paradigm shift in the modelling of pollen release, forecast exposure, and alert allergic patients. This article provides a comprehensive overview of ML-based pollen forecasting systems, clarifying their underlying principles in accessible terms for clinicians and presenting practical and published tools that allergologists can integrate into routine practice. By combining aerobiological data, meteorological models, and patient-reported outcomes, ML enables more personalized, precise, and timely allergy management. We review the fundamental mechanisms of pollen release and dispersion and illustrate how ML models can improve predictive accuracy. Key platforms are compared in terms of clinical usability. We present real-world use cases showing how ML-driven alerts can help optimize treatment plans and support patient education. Practical insights are provided on the evaluation, implementation, and limitations of these tools. ML is not a distant technology—it is already transforming pollen forecasting and allergy alerts. This article aims to equip allergologists with the knowledge needed to evaluate and adopt these tools, enabling a more proactive and personalized approach to managing pollen allergies.
Pollen-related allergic diseases, including allergic rhinoconjunctivitis and asthma, affect a growing proportion of the population and have substantial consequences for quality of life and healthcare systems. Conventional pollen forecasts, which rely on fixed pollen traps and meteorological data, are limited in spatial granularity, real-time responsiveness, and individual relevance. Recent advances in artificial intelligence (AI) and machine learning (ML) offer a paradigm shift in the modelling of pollen release, forecast exposure, and alert allergic patients. This article provides a comprehensive overview of ML-based pollen forecasting systems, clarifying their underlying principles in accessible terms for clinicians and presenting practical and published tools that allergologists can integrate into routine practice. By combining aerobiological data, meteorological models, and patient-reported outcomes, ML enables more personalized, precise, and timely allergy management. We review the fundamental mechanisms of pollen release and dispersion and illustrate how ML models can improve predictive accuracy. Key platforms are compared in terms of clinical usability. We present real-world use cases showing how ML-driven alerts can help optimize treatment plans and support patient education. Practical insights are provided on the evaluation, implementation, and limitations of these tools. ML is not a distant technology—it is already transforming pollen forecasting and allergy alerts. This article aims to equip allergologists with the knowledge needed to evaluate and adopt these tools, enabling a more proactive and personalized approach to managing pollen allergies.
DOI: https://doi.org/10.37349/eaa.2026.1009123
This article belongs to the special issue Climate Change, Allergy, and Immunotherapy
Aim:
Dysfunctional breathing (DB) is a common comorbidity in asthma, yet its objective characterisation remains challenging due to reliance on subjective questionnaires. This study aimed to determine whether quantifiable breathing pattern parameters can be used to characterise asthma patients with perceived DB from those without DB.
Methods:
This observational cross-sectional study involved 122 adults with physician-diagnosed asthma (GINA Steps 2–5). Participants completed the Nijmegen Questionnaire (NQ) to determine DB (NQ > 23) or non-DB (NDB). Resting breathing was recorded for 5 minutes using structured light plethysmography (SLP), a contactless optical motion-analysis system that quantifies thoracoabdominal displacement. Extracted parameters included respiratory rate (RR), inspiration time (Ti), expiration time (Te), Ti/total breath cycle duration (Ttot), and the ratio of ribcage to abdominal displacement during the inspiration phase (RCampinsp/ABampinsp). Both absolute values and within-subject variability [coefficient of variation expressed in percentage (CoV%)] were estimated. Between-group comparisons used Mann-Whitney U tests. Two binary logistic regression models evaluated the predictive value of mean parameters and their variability for characterising DB.
Results:
Of the 122 participants, 38 asthmatic patients were determined with DB. The DB group showed significantly higher RR and lower Ti and Te, but no differences in Ti/Ttot or RCampinsp/ABampinsp. In contrast, within-subject variability across all parameters was significantly greater in the DB group. The regression model using absolute values showed limited predictive power (R2 = 0.251). The model incorporating variability demonstrated substantially improved predictive power (R2 = 0.540), with CoV% RR, Te, Ti/Ttot, and RCampinsp/ABampinsp emerging as significant predictors.
Conclusions:
Asthma patients with DB exhibit breathing-pattern alterations, most notably increased within-subject variability of timing and TA movement parameters. Breathing pattern variability may be a promising surrogate marker to characterise DB, highlighting the value of dynamic objective physiological assessment of breathing beyond conventional symptom-based assessments of DB.
DOI: https://doi.org/10.37349/eaa.2026.1009122
Non-steroidal anti-inflammatory drug (NSAID)-exacerbated respiratory disease (N-ERD) is a respiratory illness characterized by chronic eosinophilic airway inflammation. Although a typical clinical history of asthma, chronic rhinosinusitis with nasal polyps (CRSwNP), and respiratory reactions to NSAIDs may strongly suggest the diagnosis, history alone is often unreliable due to NSAID avoidance, atypical reactions, or incomplete symptom recognition. In this context, aspirin provocation tests remain the diagnostic gold standard for confirming N-ERD. Beyond diagnostic confirmation, aspirin provocation testing provides critical insights into disease heterogeneity and phenotyping. Different challenge routes—nasal, bronchial, and oral—allow assessment of organ-specific sensitivity and inflammatory dominance. Nasal aspirin provocation primarily reflects upper airway involvement and is particularly informative in patients with severe CRSwNP, whereas inhalational lysine-aspirin challenges highlight lower-airway bronchial hyperresponsiveness. Oral aspirin provocation, through systemic exposure, captures the full spectrum of respiratory and extra-respiratory responses and therefore best reflects global disease severity. The pattern, timing, and intensity of reactions observed during provocation testing contribute to the identification of clinically relevant N-ERD subphenotypes, such as upper-airway-dominant disease, bronchial-predominant disease, or blended reactions involving both compartments. These phenotypic distinctions have direct therapeutic implications, influencing the selection of targeted treatments, including aspirin desensitization, biologic therapies, or surgical interventions. Moreover, provocation testing remains essential prior to aspirin desensitization to ensure both diagnostic accuracy and patient safety. Aspirin provocation tests are not merely confirmatory tools but represent a cornerstone of precision-based evaluation of N-ERD, enabling refined phenotyping, risk stratification, and individualized treatment planning in this complex and heterogeneous disease.
Non-steroidal anti-inflammatory drug (NSAID)-exacerbated respiratory disease (N-ERD) is a respiratory illness characterized by chronic eosinophilic airway inflammation. Although a typical clinical history of asthma, chronic rhinosinusitis with nasal polyps (CRSwNP), and respiratory reactions to NSAIDs may strongly suggest the diagnosis, history alone is often unreliable due to NSAID avoidance, atypical reactions, or incomplete symptom recognition. In this context, aspirin provocation tests remain the diagnostic gold standard for confirming N-ERD. Beyond diagnostic confirmation, aspirin provocation testing provides critical insights into disease heterogeneity and phenotyping. Different challenge routes—nasal, bronchial, and oral—allow assessment of organ-specific sensitivity and inflammatory dominance. Nasal aspirin provocation primarily reflects upper airway involvement and is particularly informative in patients with severe CRSwNP, whereas inhalational lysine-aspirin challenges highlight lower-airway bronchial hyperresponsiveness. Oral aspirin provocation, through systemic exposure, captures the full spectrum of respiratory and extra-respiratory responses and therefore best reflects global disease severity. The pattern, timing, and intensity of reactions observed during provocation testing contribute to the identification of clinically relevant N-ERD subphenotypes, such as upper-airway-dominant disease, bronchial-predominant disease, or blended reactions involving both compartments. These phenotypic distinctions have direct therapeutic implications, influencing the selection of targeted treatments, including aspirin desensitization, biologic therapies, or surgical interventions. Moreover, provocation testing remains essential prior to aspirin desensitization to ensure both diagnostic accuracy and patient safety. Aspirin provocation tests are not merely confirmatory tools but represent a cornerstone of precision-based evaluation of N-ERD, enabling refined phenotyping, risk stratification, and individualized treatment planning in this complex and heterogeneous disease.
DOI: https://doi.org/10.37349/eaa.2026.1009121
This article belongs to the special issue Update on Chronic Rhinosinusitis
Occupational allergens are an important cause of diseases emerging in the workplace, both indoor and outdoor, causing conditions such as allergic asthma, dermatitis, and rhinitis. Numerous national and international institutions focus on sensitizing agents able to induce allergies in workplaces, which are also considered by the International Classification of Diseases (ICD)-11, underlining their increasing worldwide importance. There is thus the need to develop and implement new, multidisciplinary approaches to study and monitor these agents, taking into account different sources of exposure, environmental concentrations, co-factors of exposure, and individual susceptibility. This includes the integration between traditional and innovative methodologies applied to environmental and biological matrices, as well as the use of “omic” techniques. In this picture, information, training, and communication emerge as fundamental for workers. This kind of approach will permit us to attain a better management of exposure to allergens in the workplace, improving the well-being of workers worldwide.
Occupational allergens are an important cause of diseases emerging in the workplace, both indoor and outdoor, causing conditions such as allergic asthma, dermatitis, and rhinitis. Numerous national and international institutions focus on sensitizing agents able to induce allergies in workplaces, which are also considered by the International Classification of Diseases (ICD)-11, underlining their increasing worldwide importance. There is thus the need to develop and implement new, multidisciplinary approaches to study and monitor these agents, taking into account different sources of exposure, environmental concentrations, co-factors of exposure, and individual susceptibility. This includes the integration between traditional and innovative methodologies applied to environmental and biological matrices, as well as the use of “omic” techniques. In this picture, information, training, and communication emerge as fundamental for workers. This kind of approach will permit us to attain a better management of exposure to allergens in the workplace, improving the well-being of workers worldwide.
DOI: https://doi.org/10.37349/eaa.2026.1009120
This article belongs to the special issue Environment, Infectious Diseases, and Allergy
Climate change is reshaping the aeroallergen landscape, with rising temperatures, elevated CO2, shifting precipitation, and land-use change extending pollen seasons, increasing pollen loads and allergenicity, and expanding the geographic range of allergenic plants. These changes are accompanied by escalating air pollution from fossil fuel combustion and wildfires that act as an adjuvant with co-exposure with allergen exacerbate allergic airway disease. Vulnerable populations—particularly those in socioeconomically disadvantaged and marginalized communities in the US—experience disproportionate exposure to pollutants and allergens due to structural inequities that result in some populations being exposed to more environmental hazards than other groups. Climate-amplified aeroallergen exposure and air pollution are associated with higher sensitization, symptom burden, exacerbations, and healthcare use. Structural inequities magnify exposures to allergens and air pollution, while also influencing the social environment through concentration of poverty and diminished access to resources. This review synthesizes evidence linking climate change-related effects on aeroallergens and air pollution with allergic disease risk and the modification of this relationship by social vulnerability, with a focus on Europe and North America. We also highlight established and emerging strategies to mitigate the effects of climate change on allergic disease prevalence and morbidity, including anticipatory guidance, digital forecasting, community adaptation measures, and local, regional, and national policies that promote responsible land use, healthy housing, and equity-focused public health initiatives.
Climate change is reshaping the aeroallergen landscape, with rising temperatures, elevated CO2, shifting precipitation, and land-use change extending pollen seasons, increasing pollen loads and allergenicity, and expanding the geographic range of allergenic plants. These changes are accompanied by escalating air pollution from fossil fuel combustion and wildfires that act as an adjuvant with co-exposure with allergen exacerbate allergic airway disease. Vulnerable populations—particularly those in socioeconomically disadvantaged and marginalized communities in the US—experience disproportionate exposure to pollutants and allergens due to structural inequities that result in some populations being exposed to more environmental hazards than other groups. Climate-amplified aeroallergen exposure and air pollution are associated with higher sensitization, symptom burden, exacerbations, and healthcare use. Structural inequities magnify exposures to allergens and air pollution, while also influencing the social environment through concentration of poverty and diminished access to resources. This review synthesizes evidence linking climate change-related effects on aeroallergens and air pollution with allergic disease risk and the modification of this relationship by social vulnerability, with a focus on Europe and North America. We also highlight established and emerging strategies to mitigate the effects of climate change on allergic disease prevalence and morbidity, including anticipatory guidance, digital forecasting, community adaptation measures, and local, regional, and national policies that promote responsible land use, healthy housing, and equity-focused public health initiatives.
DOI: https://doi.org/10.37349/eaa.2026.1009119
This article belongs to the special issue Climate Change, Allergy, and Immunotherapy
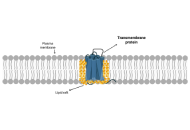
The composition and biophysical characteristics of the plasma membrane are pivotal in regulating mast cell immune functions by influencing receptor distribution, activation, and intracellular signaling pathways. This article highlights the impact of plasma membrane components, such as cholesterol and lipid rafts, on the function of the Mas-related G protein-coupled receptor X2 (MRGPRX2), a key mediator of IgE-independent mast cell activation and pseudoallergic reactions. We discuss how variations in membrane fluidity, lipid composition, and microdomain organization influence MRGPRX2 conformational dynamics, ligand accessibility, and downstream signaling efficiency. These membrane-driven effects may help explain the heterogeneity of mast cell responsiveness across tissues and disease states. Integrating insights from structural biology, biophysics, and clinical immunology emphasizes that plasma membrane composition and dynamics regulate MRGPRX2-mediated signaling, positioning the membrane environment as a promising therapeutic target for modulating mast-cell hyperreactivity. By outlining this conceptual framework, we introduce a unifying hypothesis that membrane-driven regulation is a critical, yet underrecognized, determinant of MRGPRX2 responsiveness in different tissues and disease states.
The composition and biophysical characteristics of the plasma membrane are pivotal in regulating mast cell immune functions by influencing receptor distribution, activation, and intracellular signaling pathways. This article highlights the impact of plasma membrane components, such as cholesterol and lipid rafts, on the function of the Mas-related G protein-coupled receptor X2 (MRGPRX2), a key mediator of IgE-independent mast cell activation and pseudoallergic reactions. We discuss how variations in membrane fluidity, lipid composition, and microdomain organization influence MRGPRX2 conformational dynamics, ligand accessibility, and downstream signaling efficiency. These membrane-driven effects may help explain the heterogeneity of mast cell responsiveness across tissues and disease states. Integrating insights from structural biology, biophysics, and clinical immunology emphasizes that plasma membrane composition and dynamics regulate MRGPRX2-mediated signaling, positioning the membrane environment as a promising therapeutic target for modulating mast-cell hyperreactivity. By outlining this conceptual framework, we introduce a unifying hypothesis that membrane-driven regulation is a critical, yet underrecognized, determinant of MRGPRX2 responsiveness in different tissues and disease states.
DOI: https://doi.org/10.37349/eaa.2026.1009118
This article belongs to the special issue Bridging Experimental and Translational Allergology
APPaRENT2 was a multi-country, cross-sectional, online survey of patients with asthma and physicians conducted in five countries (Argentina, Brazil, France, Mexico, and Italy), aimed at assessing physicians’ and patients’ preferred treatment strategies and goals. Education level, age, and place of residence differed between European and Latin American patients; furthermore, most Italian doctors worked within the Public Health Service. For the purpose of identifying the critical issues in the management of asthma in Italy, the data were analysed in greater detail, comparing those collected in Italy with those from Latin American countries and those provided by Italian patients and doctors. The data are reported as frequencies or means. The differences found in comparing data were not analysed for statistical significance, given the absence of any a priori hypothesis in the original paper. The Italian results were consistently within the range of the Latin American countries’ results. In Italy, despite the physicians’ prioritization of symptom control, many patients had poor asthma control but gave a surprisingly optimistic evaluation of their disease, given the high frequency of symptoms and limitations in everyday life. Physicians and patients had quite different evaluations of symptoms and outcomes of asthma. Finally, the combination of ICS/LABA with SABA as needed was the preferred treatment compared with the maintenance and reliever therapy (MART) strategy, suggested as preferential in the Global Initiative for Asthma (GINA) document. In conclusion, the absence of shared assessments and expectations between doctors and patients appears to be the primary issue to address in order to improve asthma treatment in Italy.
APPaRENT2 was a multi-country, cross-sectional, online survey of patients with asthma and physicians conducted in five countries (Argentina, Brazil, France, Mexico, and Italy), aimed at assessing physicians’ and patients’ preferred treatment strategies and goals. Education level, age, and place of residence differed between European and Latin American patients; furthermore, most Italian doctors worked within the Public Health Service. For the purpose of identifying the critical issues in the management of asthma in Italy, the data were analysed in greater detail, comparing those collected in Italy with those from Latin American countries and those provided by Italian patients and doctors. The data are reported as frequencies or means. The differences found in comparing data were not analysed for statistical significance, given the absence of any a priori hypothesis in the original paper. The Italian results were consistently within the range of the Latin American countries’ results. In Italy, despite the physicians’ prioritization of symptom control, many patients had poor asthma control but gave a surprisingly optimistic evaluation of their disease, given the high frequency of symptoms and limitations in everyday life. Physicians and patients had quite different evaluations of symptoms and outcomes of asthma. Finally, the combination of ICS/LABA with SABA as needed was the preferred treatment compared with the maintenance and reliever therapy (MART) strategy, suggested as preferential in the Global Initiative for Asthma (GINA) document. In conclusion, the absence of shared assessments and expectations between doctors and patients appears to be the primary issue to address in order to improve asthma treatment in Italy.
DOI: https://doi.org/10.37349/eaa.2026.1009117
