

 Previous
Lung cancer is the leading cause of cancer-related deaths worldwide. The main risk factor for lung cancer is exposure to chemicals present in cigarettes and atmospheric pollutants, which, among other mechanisms, can increase the risk of cancer by inducing pulmonary inflammation. Among the complex features of inflammatory processes, the role of inflammasomes has attracted increasing attention due to their role in different stages of carcinogenesis. Inflammasomes are intracellular multiprotein complexes that when activated promote the maturation of interleukin-1beta (IL-1β) and IL-18, pro-inflammatory cytokines involved in the promotion, progression, epithelial-mesenchymal transition, metastasis, and resistance to therapy of lung cancer. In this way, this review summarizes the recent findings of inflammasome research in different stages of lung cancer, with a focus on non-small cell lung carcinoma (NSCLC), and highlights these multiprotein complexes as promising targets for cancer therapy.
Lung cancer is the leading cause of cancer-related deaths worldwide. The main risk factor for lung cancer is exposure to chemicals present in cigarettes and atmospheric pollutants, which, among other mechanisms, can increase the risk of cancer by inducing pulmonary inflammation. Among the complex features of inflammatory processes, the role of inflammasomes has attracted increasing attention due to their role in different stages of carcinogenesis. Inflammasomes are intracellular multiprotein complexes that when activated promote the maturation of interleukin-1beta (IL-1β) and IL-18, pro-inflammatory cytokines involved in the promotion, progression, epithelial-mesenchymal transition, metastasis, and resistance to therapy of lung cancer. In this way, this review summarizes the recent findings of inflammasome research in different stages of lung cancer, with a focus on non-small cell lung carcinoma (NSCLC), and highlights these multiprotein complexes as promising targets for cancer therapy.
DOI: https://doi.org/10.37349/ei.2023.00090


The infection of COVID-19 is directly linked to the destruction of lung epithelial cells, and the cyclic guanosine monophosphate-adenosine monophosphate synthase-stimulator of interferon genes (cGAS-STING) system has been implicated in the pathology of respiratory infections. This study aimed to systematize the relationship between the pathophysiology of COVID-19 and the cGAS-STING system’s activation in the lungs. Severe acute respiratory syndrome coronavirus type 2 (SARS-CoV-2) is an RNA virus that belongs to the Coronaviridae family whose genetic material is produced by a single positive RNA molecule (RNA+). The cGAS-STING signaling pathway has emerged as a key mediator of injury caused by infection and cellular or tissue stress. The cGAS-STING cyclic pathway is part of innate immunity and is activated from cytosolic DNA responses present in newly formed syncytia, by cell-to-cell fusion, in target of angiotensin-converting enzyme 2 (ACE2) expression and SARS-CoV-2 Spike protein. Although this pathway is canonically understood to be responsive to both pathogen-derived and host-derived DNA, it has been demonstrated to cross-communicate with the retinoic acid-inducible gene I (RIG-I)-like receptors (RLRs). cGAS-STING activation is significant to interferon production, mainly type-I interferons (IFN-I), in a SARS-CoV-2 infection scenario, indicating a major antiviral role of the cGAS-STING pathway. It was identified that in SARS-CoV-2 the cGAS-STING axis is activated, but the inflammatory response could be specific for nuclear factor-κB (NF-κB) in infected cells, and that this axis is potentiated by a cytokine storm produced by the immune system’s cells.
The infection of COVID-19 is directly linked to the destruction of lung epithelial cells, and the cyclic guanosine monophosphate-adenosine monophosphate synthase-stimulator of interferon genes (cGAS-STING) system has been implicated in the pathology of respiratory infections. This study aimed to systematize the relationship between the pathophysiology of COVID-19 and the cGAS-STING system’s activation in the lungs. Severe acute respiratory syndrome coronavirus type 2 (SARS-CoV-2) is an RNA virus that belongs to the Coronaviridae family whose genetic material is produced by a single positive RNA molecule (RNA+). The cGAS-STING signaling pathway has emerged as a key mediator of injury caused by infection and cellular or tissue stress. The cGAS-STING cyclic pathway is part of innate immunity and is activated from cytosolic DNA responses present in newly formed syncytia, by cell-to-cell fusion, in target of angiotensin-converting enzyme 2 (ACE2) expression and SARS-CoV-2 Spike protein. Although this pathway is canonically understood to be responsive to both pathogen-derived and host-derived DNA, it has been demonstrated to cross-communicate with the retinoic acid-inducible gene I (RIG-I)-like receptors (RLRs). cGAS-STING activation is significant to interferon production, mainly type-I interferons (IFN-I), in a SARS-CoV-2 infection scenario, indicating a major antiviral role of the cGAS-STING pathway. It was identified that in SARS-CoV-2 the cGAS-STING axis is activated, but the inflammatory response could be specific for nuclear factor-κB (NF-κB) in infected cells, and that this axis is potentiated by a cytokine storm produced by the immune system’s cells.
DOI: https://doi.org/10.37349/ei.2023.00089
Tumor necrosis factor receptor (TNFR)-associated factors (TRAFs) are a family of intracellular signaling adaptors that associate with the cytoplasmic tails of a diverse range of lymphocyte receptors, including members of the TNFR superfamily, the Toll-like receptor (TLR)/interleukin-1 (IL-1) receptor superfamily, and the IL-6 receptor family that are major targets for therapeutic intervention for inflammatory diseases. TRAF5 is one of the seven family members of the TRAF family and is highly expressed by B- and T-lymphocytes. As compared to other family members, the biological and pathophysiological functions of TRAF5 have remained ambiguous since its discovery. TRAF5 promotes lymphocyte signaling for the TNFR family molecules such as glucocorticoid-induced TNFR family-related protein (GITR), CD27, and CD40. In contrast, TRAF5 limits the activity of the common signaling receptor subunit glycoprotein 130 kDa (gp130) in CD4+ T cells that requires signaling by IL-6 and IL-27. TRAF5 also restrains TLR signaling in B cells. Thus, TRAF5 regulates lymphocyte signaling in both positive and negative ways. This review will summarize the findings of recent studies of TRAF5 in terms of how TRAF5 regulates signaling in lymphocytes and other cell types and how TRAF5 expression contributes to inflammatory and autoimmune diseases in mice and humans.
Tumor necrosis factor receptor (TNFR)-associated factors (TRAFs) are a family of intracellular signaling adaptors that associate with the cytoplasmic tails of a diverse range of lymphocyte receptors, including members of the TNFR superfamily, the Toll-like receptor (TLR)/interleukin-1 (IL-1) receptor superfamily, and the IL-6 receptor family that are major targets for therapeutic intervention for inflammatory diseases. TRAF5 is one of the seven family members of the TRAF family and is highly expressed by B- and T-lymphocytes. As compared to other family members, the biological and pathophysiological functions of TRAF5 have remained ambiguous since its discovery. TRAF5 promotes lymphocyte signaling for the TNFR family molecules such as glucocorticoid-induced TNFR family-related protein (GITR), CD27, and CD40. In contrast, TRAF5 limits the activity of the common signaling receptor subunit glycoprotein 130 kDa (gp130) in CD4+ T cells that requires signaling by IL-6 and IL-27. TRAF5 also restrains TLR signaling in B cells. Thus, TRAF5 regulates lymphocyte signaling in both positive and negative ways. This review will summarize the findings of recent studies of TRAF5 in terms of how TRAF5 regulates signaling in lymphocytes and other cell types and how TRAF5 expression contributes to inflammatory and autoimmune diseases in mice and humans.
DOI: https://doi.org/10.37349/ei.2023.00088
This article belongs to the special issue The Role of Adaptor Proteins in Lymphoid Cell Signaling
Coronavirus disease caused by the recently emerged severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) represents a major public health that has submerged the world into a crisis unprecedented in the modern era. A better understanding of the innate immune response could help to fight this pandemic and be better prepared for potential future outbreaks. Interestingly, innate immune cells can develop a non-specific memory termed trained immunity. This review details recent evidence concerning the interaction of SARS-CoV-2 with innate immune cells, in particular those in which the trained immunity activity has been demonstrated.
Coronavirus disease caused by the recently emerged severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) represents a major public health that has submerged the world into a crisis unprecedented in the modern era. A better understanding of the innate immune response could help to fight this pandemic and be better prepared for potential future outbreaks. Interestingly, innate immune cells can develop a non-specific memory termed trained immunity. This review details recent evidence concerning the interaction of SARS-CoV-2 with innate immune cells, in particular those in which the trained immunity activity has been demonstrated.
DOI: https://doi.org/10.37349/ei.2023.00087
This article belongs to the special issue Immunology, Immunopathology and Genomics of SARS-COV-2
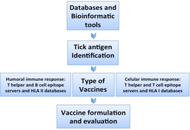
Immunoinformatics is an emerging area focused on development and applications of methods used to facilitate vaccine development. There is a growing interest in the field of vaccinology centered on the new omic science named ‘vaccinomics’. However, this approach has not succeeded to provide a solution against major infections affecting both animals and humans, since tick vaccines are still being developed based on conventional biochemical or immunological methods to dissect the molecular structure of the pathogen, looking for a candidate antigen. The availability of complete genomes and the novel advanced technologies, such as data mining, bioinformatics, microarrays, and proteomics, have revolutionized the approach to vaccine development and provided a new impulse to tick research. The aim of this review is to explore how modern vaccinology will contribute to the discovery of new candidate antigens and to understand the research process to improve existing vaccines. Under this concept, the omic age of ticks will make it possible to design vaccines starting from a prediction based on the in silico analysis of gene sequences obtained by data mining using computer algorithms, without the need to keep the pathogen growing in vitro. This new genome-based approach has been named “reverse vaccinology 3.0” or “vaccinomics 1.0” and can be applied to ticks.
Immunoinformatics is an emerging area focused on development and applications of methods used to facilitate vaccine development. There is a growing interest in the field of vaccinology centered on the new omic science named ‘vaccinomics’. However, this approach has not succeeded to provide a solution against major infections affecting both animals and humans, since tick vaccines are still being developed based on conventional biochemical or immunological methods to dissect the molecular structure of the pathogen, looking for a candidate antigen. The availability of complete genomes and the novel advanced technologies, such as data mining, bioinformatics, microarrays, and proteomics, have revolutionized the approach to vaccine development and provided a new impulse to tick research. The aim of this review is to explore how modern vaccinology will contribute to the discovery of new candidate antigens and to understand the research process to improve existing vaccines. Under this concept, the omic age of ticks will make it possible to design vaccines starting from a prediction based on the in silico analysis of gene sequences obtained by data mining using computer algorithms, without the need to keep the pathogen growing in vitro. This new genome-based approach has been named “reverse vaccinology 3.0” or “vaccinomics 1.0” and can be applied to ticks.
DOI: https://doi.org/10.37349/ei.2023.00085
Human cytomegalovirus (HCMV), whose genome is around 235 kb, is a ubiquitous human herpesvirus that infects between 40% and 95% of the population. Though HCMV infection is commonly asymptomatic and leads to subtle clinical symptoms, it can promote robust immune responses and establish lifelong latency. In addition, in immunocompromised hosts, including individuals with acquired immunodeficiency syndrome (AIDS), transplant recipients, and developing fetuses it can lead to severe diseases. Immunosenescence, well-defined as the alterations in the immune system, is linked mainly to aging and has been recently gathering considerable attention. Senescence was characterized by an elevated inflammation and hence considered a powerful contributor to “inflammaging” that is measured mainly by tumor necrosis factor-α (TNF-α), interleukin-6 (IL-6), and C-reactive protein (CRP) levels as well as latent viral infections, for instance, cytomegalovirus (CMV). Inflammaging resulted in a senescence-associated secretory phenotype (SASP). HCMV is markedly associated with accelerated aging of the immune system as well as several age-associated diseases that accumulate and subsequently deteriorate the immune responses, thus have been linked to mortality, declined vaccine efficacy, serious diseases, and tumors in the elderly. HCMV triggers or exacerbates immunosenescence; on the other hand, the weakened immune responses and inflammaging favor viral reactivation and highlight the role of HCMV in aging as well as viral-associated tumors. HCMV reactivation resulting in sequential lytic and latent viral cycles could contribute to HCMV genomic variability. Besides the oncomodulatory role and transforming capacities of HCMV, the immune-privileged tumor microenvironment has been considered the main element in tumor progression and aggressiveness. Therefore, the interplay between HCMV, immunosenescence, and cancer will aid in discovering new therapeutic approaches that target HCMV and act as immune response boosters mainly to fight cancers of poor prognosis, particularly in the elderly population.
Human cytomegalovirus (HCMV), whose genome is around 235 kb, is a ubiquitous human herpesvirus that infects between 40% and 95% of the population. Though HCMV infection is commonly asymptomatic and leads to subtle clinical symptoms, it can promote robust immune responses and establish lifelong latency. In addition, in immunocompromised hosts, including individuals with acquired immunodeficiency syndrome (AIDS), transplant recipients, and developing fetuses it can lead to severe diseases. Immunosenescence, well-defined as the alterations in the immune system, is linked mainly to aging and has been recently gathering considerable attention. Senescence was characterized by an elevated inflammation and hence considered a powerful contributor to “inflammaging” that is measured mainly by tumor necrosis factor-α (TNF-α), interleukin-6 (IL-6), and C-reactive protein (CRP) levels as well as latent viral infections, for instance, cytomegalovirus (CMV). Inflammaging resulted in a senescence-associated secretory phenotype (SASP). HCMV is markedly associated with accelerated aging of the immune system as well as several age-associated diseases that accumulate and subsequently deteriorate the immune responses, thus have been linked to mortality, declined vaccine efficacy, serious diseases, and tumors in the elderly. HCMV triggers or exacerbates immunosenescence; on the other hand, the weakened immune responses and inflammaging favor viral reactivation and highlight the role of HCMV in aging as well as viral-associated tumors. HCMV reactivation resulting in sequential lytic and latent viral cycles could contribute to HCMV genomic variability. Besides the oncomodulatory role and transforming capacities of HCMV, the immune-privileged tumor microenvironment has been considered the main element in tumor progression and aggressiveness. Therefore, the interplay between HCMV, immunosenescence, and cancer will aid in discovering new therapeutic approaches that target HCMV and act as immune response boosters mainly to fight cancers of poor prognosis, particularly in the elderly population.
DOI: https://doi.org/10.37349/ei.2023.00086
This article belongs to the special issue Immunosenescence: Mechanisms and Its Impact
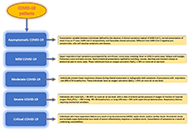
The severe acute respiratory syndrome coronavirus-2 (SARS-CoV-2) infection in the human host can lead to various clinical manifestations, from symptomless carriers to mild to moderate to severe/critical illness. Therefore, the clinical classification of SARS-CoV-2 disease, based on severity, is a reliable way to predict disease states in SARS-CoV-2 infection. Recent studies on genomics, transcriptomics, epigenomics, and immunogenomics, along with spatial analysis of immune cells have delineated and defined the categorization of these disease groups using these high throughout technologies. These technologies hold the promise of providing not only a detailed but a holistic view of SARS-CoV-2-led pathogenesis. The main genomic, cellular, and immunologic features of each disease category, and what separates them spatially and molecularly are discussed in this brief review to provide a foundational spatial understanding of SARS-CoV-2 immunopathogenesis.
The severe acute respiratory syndrome coronavirus-2 (SARS-CoV-2) infection in the human host can lead to various clinical manifestations, from symptomless carriers to mild to moderate to severe/critical illness. Therefore, the clinical classification of SARS-CoV-2 disease, based on severity, is a reliable way to predict disease states in SARS-CoV-2 infection. Recent studies on genomics, transcriptomics, epigenomics, and immunogenomics, along with spatial analysis of immune cells have delineated and defined the categorization of these disease groups using these high throughout technologies. These technologies hold the promise of providing not only a detailed but a holistic view of SARS-CoV-2-led pathogenesis. The main genomic, cellular, and immunologic features of each disease category, and what separates them spatially and molecularly are discussed in this brief review to provide a foundational spatial understanding of SARS-CoV-2 immunopathogenesis.
DOI: https://doi.org/10.37349/ei.2022.00084
This article belongs to the special issue Immunology, Immunopathology and Genomics of SARS-COV-2
Aim:
As the primary response antibody with increasing use as a therapeutic immunoglobulin (Ig) format, IgM is also the largest antibody structure among the five major human isotypes. Spontaneously formed pentamers and hexamers of IgM have avidity effects that could compensate for weaker interactions in monomeric Igs. However, this advantage is counterbalanced by potential steric clashes when binding to multiple large antigens. Recent findings have challenged the expected canonical independence of Fc receptor (FcR) binding at the heavy chain constant (C)-region where the heavy chain C-region isotypes affected antigen binding at the variable (V)-regions, and the variable heavy (VH) families of the V-region affected FcR engagement at the antibody C-regions. With such effects found on other Ig isotypes, IgM candidates need to be investigated with regards to such effects, especially when considering its natural oligomerisation at the C-region that can amplify or modulate such allosteric effects.
Methods:
Through a panel of 14 recombinant complementarity determining regions (CDRs)-grafted trastuzumab and pertuzumab VH1-7 IgMs subjected to bio-layer interferometry measurements, the interactions with the antigen human epidermal growth factor receptor 2 (Her2), Fc-mu receptor (FcμR), and superantigen Protein L (PpL) were investigated.
Results:
Significant effects from the V-regions to mitigate FcμR binding and the IgM C-region bidirectional effect modulating Her2 antigen engagements at the V-regions were found. Additional modulatory effects from superantigen PpL binding on the V-region of the kappa chain (Vκ) mitigating antigen binding were also found, revealing possible novel mechanisms of antibody superantigens that can be moderated by the antibody VH frameworks.
Conclusions:
These findings show that the oligomerisation of IgMs plays a significant role in FcμR, antigen, and superantigen binding that made IgM distinct from the other antibody isotypes and how these features should be considered during further development and protein engineering of IgM therapeutics.
DOI: https://doi.org/10.37349/ei.2022.00083
Immune responses are orchestrated by controlling the initiation, magnitude, and duration of various signaling pathways. Adaptor proteins act as positive or negative regulators by targeting critical molecules of signaling cascades. Signal-transducing adaptor protein-2 (STAP-2) contains typical features of adaptor proteins, like a pleckstrin homology (PH) domain in the N-terminal region and a Src homology 2 (SH2) domain in the central region. STAP-2 binds to a variety of signaling or transcriptional molecules to control multiple steps of inflammatory/immune responses. STAP-2 enhances T-cell receptor (TCR)-mediated signaling via the association with TCR-proximal CD3ζ immunoreceptor tyrosine-based activation motifs (ITAMs) and lymphocyte-specific protein tyrosine kinase (Lck). STAP-2 decreases adherence of T-cells to fibronectin (FN) through an association with focal adhesion kinase (Fak) and Casitas B-lineage Lymphoma (c-Cbl), and increases chemotaxis of T-cells toward stromal cell-derived factor-1α (SDF-1α) through interactions with Vav1 and Ras-related C3 botulinum toxin substrate 1 (Rac1). STAP-2 positively regulates activation-induced cell deathrough the association with Fas and caspase-8. This review describes the current knowledge of the roles of STAP-2 in T-cell-dependent immune responses and the possible clinical utility of STAP-2-targeting therapies.
Immune responses are orchestrated by controlling the initiation, magnitude, and duration of various signaling pathways. Adaptor proteins act as positive or negative regulators by targeting critical molecules of signaling cascades. Signal-transducing adaptor protein-2 (STAP-2) contains typical features of adaptor proteins, like a pleckstrin homology (PH) domain in the N-terminal region and a Src homology 2 (SH2) domain in the central region. STAP-2 binds to a variety of signaling or transcriptional molecules to control multiple steps of inflammatory/immune responses. STAP-2 enhances T-cell receptor (TCR)-mediated signaling via the association with TCR-proximal CD3ζ immunoreceptor tyrosine-based activation motifs (ITAMs) and lymphocyte-specific protein tyrosine kinase (Lck). STAP-2 decreases adherence of T-cells to fibronectin (FN) through an association with focal adhesion kinase (Fak) and Casitas B-lineage Lymphoma (c-Cbl), and increases chemotaxis of T-cells toward stromal cell-derived factor-1α (SDF-1α) through interactions with Vav1 and Ras-related C3 botulinum toxin substrate 1 (Rac1). STAP-2 positively regulates activation-induced cell deathrough the association with Fas and caspase-8. This review describes the current knowledge of the roles of STAP-2 in T-cell-dependent immune responses and the possible clinical utility of STAP-2-targeting therapies.
DOI: https://doi.org/10.37349/ei.2022.00082
This article belongs to the special issue The Role of Adaptor Proteins in Lymphoid Cell Signaling
Psoriasis is a skin disease characterized by scaly erythema, parakeratosis, and epidermal hyperplasia. Application of imiquimod (IMQ), a ligand for Toll-like receptor 7, produces a mouse model for psoriasis. IMQ application induces scaling, erythema, and thickness in skin lesions, and the symptoms are milder in interleukin-23 p19 (Il23p19)-deficient and Il17a-deficient mice than in wild-type mice; this suggests that the interleukin-23 (IL-23)/T helper 17 (Th17) axis and Th17 cell-secreting cytokines play essential roles in the IMQ-induced psoriasis model. It is notable that a genome-wide association study identified the human tyrosine kinase 2 (TYK2) gene within the psoriasis susceptibility locus. After IMQ application, mice lacking Tyk2, a mouse homologue of the human TYK2 gene, exhibited significantly lower symptom scores of psoriasis and diminished inflammatory cell infiltration in the skin lesions. Tyk2-deficient mice also failed to increase CD4+IL-17+ or CD4+ interferon-γ+ (IFN-γ+) T cells in the draining lymph nodes or to produce Th17 cell-related cytokines after IMQ application. Furthermore, Tyk2 deficiency led to diminished skin inflammation induced by IL-23 and IL-22 injections. These results indicate that Tyk2-mediated signals in mice contribute to multiple steps of immune and inflammatory responses during the development of psoriasis; therefore, TYK2 targeting may be a promising strategy to treat patients with psoriasis. Recent clinical trials have shown that TYK2 inhibitors have a high overall response rate with good tolerability in the management of psoriasis. This review describes the fundamental mechanisms of Tyk2 inhibition in immune/inflammatory diseases.
Psoriasis is a skin disease characterized by scaly erythema, parakeratosis, and epidermal hyperplasia. Application of imiquimod (IMQ), a ligand for Toll-like receptor 7, produces a mouse model for psoriasis. IMQ application induces scaling, erythema, and thickness in skin lesions, and the symptoms are milder in interleukin-23 p19 (Il23p19)-deficient and Il17a-deficient mice than in wild-type mice; this suggests that the interleukin-23 (IL-23)/T helper 17 (Th17) axis and Th17 cell-secreting cytokines play essential roles in the IMQ-induced psoriasis model. It is notable that a genome-wide association study identified the human tyrosine kinase 2 (TYK2) gene within the psoriasis susceptibility locus. After IMQ application, mice lacking Tyk2, a mouse homologue of the human TYK2 gene, exhibited significantly lower symptom scores of psoriasis and diminished inflammatory cell infiltration in the skin lesions. Tyk2-deficient mice also failed to increase CD4+IL-17+ or CD4+ interferon-γ+ (IFN-γ+) T cells in the draining lymph nodes or to produce Th17 cell-related cytokines after IMQ application. Furthermore, Tyk2 deficiency led to diminished skin inflammation induced by IL-23 and IL-22 injections. These results indicate that Tyk2-mediated signals in mice contribute to multiple steps of immune and inflammatory responses during the development of psoriasis; therefore, TYK2 targeting may be a promising strategy to treat patients with psoriasis. Recent clinical trials have shown that TYK2 inhibitors have a high overall response rate with good tolerability in the management of psoriasis. This review describes the fundamental mechanisms of Tyk2 inhibition in immune/inflammatory diseases.
DOI: https://doi.org/10.37349/ei.2022.00081
This article belongs to the special issue Cytokines and Skin Diseases
Aim:
Human leukocyte antigen (HLA) population genetics has been a historical field centralizing data resource. HLA genetics databases typically facilitate access to frequencies of allele, haplotype, and genotype format information. Among many resources, the Allele Frequency Net Database (AFND) is a typical centralized repository that allows users to research and analyze immune gene frequencies in different populations around the world. With the massive increase in medical data and the strengthening of data governance laws, the proposal for a new distributed and secure model for the historical centralization method in population genetics has become important. In this paper, a new model of HLA population genetic resources, an alternative distributed version of HLA databases has been developed. It allows users to perform the same research and analysis with other remote sites without sharing their original data and monitoring data access.
Methods:
This new version uses the Master/Worker distributed model and offers distributed algorithms for the calculation of allelic frequencies, haplotypic frequencies and for individual genotypic calculations. The new model was evaluated on a distributed testbed for experiment-driven research Grid’5000 and has obtained good results of accuracy and execution time compared to the original centralized scheme used by researchers.
Results:
The results show that distributed algorithm applied to HLA population genetics resources enables usage control and enables enforcing the security framework of the data-owning institution. It gives the same results for all counting methods in population immunogenetics. With the same frequencies’ estimations, it yields a much quicker computation time in many cases, in particular for large samples.
Conclusions:
Distributing previously centralized resources is an interesting perspective enhancing better control of data sharing.
DOI: https://doi.org/10.37349/ei.2022.00080
Microbiome research has enormous potential in cancer research and the use of formalin-fixed paraffin-embedded (FFPE) tissues could offer many advantages. The tumor microenvironment represents a suitable niche for specific microbes and evidence proves the presence of an endogenous tumor microbiota, here referred to as oncobiota. Awareness of the oncobiota role in tumorigenesis could have a large influence on cancer care, in terms of diagnosis, prevention, and treatment. Moreover, understanding the microbial-related tumor microenvironment, and its influence on tumor immune response and cancer cells will help define important pathogenetic mechanisms in cancer starting or progression. Routine collection of histopathological FFPE samples provides a large availability of specimens essential for affordable and impactful retrospective analyses and for getting robust statistical results. The FFPE tissues are common in the analysis of tumor biopsies including the tumor microbiota characterization which has an important role in the modulation of our immune system and consequently of tumor cells. However, the microbiota analysis starting from FFPE tissues presents methodological pitfalls and limits that may negatively affect the oncobiota research. After examining the methodological and analytical difficulties of this approach, this work seeks to offer workable solutions to promote that research area.
Microbiome research has enormous potential in cancer research and the use of formalin-fixed paraffin-embedded (FFPE) tissues could offer many advantages. The tumor microenvironment represents a suitable niche for specific microbes and evidence proves the presence of an endogenous tumor microbiota, here referred to as oncobiota. Awareness of the oncobiota role in tumorigenesis could have a large influence on cancer care, in terms of diagnosis, prevention, and treatment. Moreover, understanding the microbial-related tumor microenvironment, and its influence on tumor immune response and cancer cells will help define important pathogenetic mechanisms in cancer starting or progression. Routine collection of histopathological FFPE samples provides a large availability of specimens essential for affordable and impactful retrospective analyses and for getting robust statistical results. The FFPE tissues are common in the analysis of tumor biopsies including the tumor microbiota characterization which has an important role in the modulation of our immune system and consequently of tumor cells. However, the microbiota analysis starting from FFPE tissues presents methodological pitfalls and limits that may negatively affect the oncobiota research. After examining the methodological and analytical difficulties of this approach, this work seeks to offer workable solutions to promote that research area.
DOI: https://doi.org/10.37349/ei.2022.00078
The absence of advancement in finding efficient vaccines for several human viruses, such as hepatitis C virus (HCV), human immunodeficiency virus type 1 (HIV-1), and herpes simplex viruses (HSVs) despite 30, 40, and even 60 years of research, respectively, is unnerving. Among objective reasons for such failure are the highly glycosylated nature of proteins used as primary vaccine targets against these viruses and the presence of neotopes and cryptotopes, as well as high mutation rates of the RNA viruses HCV and HIV-1 and the capability to establish latency by HSVs. However, the lack of success in utilization of the structure-based reverse vaccinology for these viruses is likely to be related to the presence of highly flexible and intrinsically disordered regions in human antibodies (Abs) and the major immunogens of HIV-1, HCV, and HSVs, their surface glycoproteins. This clearly calls for moving from the rational structure-based vaccinology to the unstructural vaccinology based on the utilization of tools designed for the analysis of disordered and flexible proteins, while looking at intrinsically disordered viral antigens and their interactions with intrinsically disordered/flexible Abs.
The absence of advancement in finding efficient vaccines for several human viruses, such as hepatitis C virus (HCV), human immunodeficiency virus type 1 (HIV-1), and herpes simplex viruses (HSVs) despite 30, 40, and even 60 years of research, respectively, is unnerving. Among objective reasons for such failure are the highly glycosylated nature of proteins used as primary vaccine targets against these viruses and the presence of neotopes and cryptotopes, as well as high mutation rates of the RNA viruses HCV and HIV-1 and the capability to establish latency by HSVs. However, the lack of success in utilization of the structure-based reverse vaccinology for these viruses is likely to be related to the presence of highly flexible and intrinsically disordered regions in human antibodies (Abs) and the major immunogens of HIV-1, HCV, and HSVs, their surface glycoproteins. This clearly calls for moving from the rational structure-based vaccinology to the unstructural vaccinology based on the utilization of tools designed for the analysis of disordered and flexible proteins, while looking at intrinsically disordered viral antigens and their interactions with intrinsically disordered/flexible Abs.
DOI: https://doi.org/10.37349/ei.2022.00079
This article belongs to the special issue Old and New Paradigms in Viral Vaccinology
Natural killer (NK) cells have a dual role in human reproduction for maternal-fetal tolerance and protection from infection. During the ovarian cycle and pregnancy, peripheral NK (pNK) and uterine NK (uNK) cells dynamically change their proportions and cytotoxicities to prepare and accommodate invading trophoblast and maintain pregnancy. However, dysregulated pNK and uNK cell proportions and cytotoxic activities have been associated with aberrant spiral artery remodeling and trophoblast invasion, leading to implantation failures and recurrent pregnancy losses (RPLs). This review will focus on the role of NK cells in RPLs reviewing the ontogeny of NK cells, changes in pNK and uNK cell levels, and activities during the ovarian cycle, normal pregnancy, and RPL. In addition, the immunopathological role of NK cells in endometrial/decidual vascular development and killer immunoglobin-like receptor (KIR) and human leukocyte antigen (HLA)-C interactions are discussed.
Natural killer (NK) cells have a dual role in human reproduction for maternal-fetal tolerance and protection from infection. During the ovarian cycle and pregnancy, peripheral NK (pNK) and uterine NK (uNK) cells dynamically change their proportions and cytotoxicities to prepare and accommodate invading trophoblast and maintain pregnancy. However, dysregulated pNK and uNK cell proportions and cytotoxic activities have been associated with aberrant spiral artery remodeling and trophoblast invasion, leading to implantation failures and recurrent pregnancy losses (RPLs). This review will focus on the role of NK cells in RPLs reviewing the ontogeny of NK cells, changes in pNK and uNK cell levels, and activities during the ovarian cycle, normal pregnancy, and RPL. In addition, the immunopathological role of NK cells in endometrial/decidual vascular development and killer immunoglobin-like receptor (KIR) and human leukocyte antigen (HLA)-C interactions are discussed.
DOI: https://doi.org/10.37349/ei.2022.00077
This article belongs to the special issue Human Reproduction: Involvement of the Immune System
Menopause signals the end of the reproductive period in women. However, fertility and fecundity decrease with increasing age prior to menopause demonstrating that changes in the premenopausal female reproductive tract (FRT) are already occurring that negatively impact reproductive success. The effects of age on the endometrium are poorly understood, in contrast to the ovary where changes occur with increasing age that negatively affect successful reproduction. The endometrial immune system is essential for generating a receptive endometrium, but the link between the immune and reproductive systems in the endometrium in the years prior to menopause has not been well-defined. Since the endometrial immune system is tightly regulated to maximize reproductive success and pathogen protection, changes in immune function with increasing premenopausal age have the potential to impact reproduction.
Menopause signals the end of the reproductive period in women. However, fertility and fecundity decrease with increasing age prior to menopause demonstrating that changes in the premenopausal female reproductive tract (FRT) are already occurring that negatively impact reproductive success. The effects of age on the endometrium are poorly understood, in contrast to the ovary where changes occur with increasing age that negatively affect successful reproduction. The endometrial immune system is essential for generating a receptive endometrium, but the link between the immune and reproductive systems in the endometrium in the years prior to menopause has not been well-defined. Since the endometrial immune system is tightly regulated to maximize reproductive success and pathogen protection, changes in immune function with increasing premenopausal age have the potential to impact reproduction.
DOI: https://doi.org/10.37349/ei.2022.00076
This article belongs to the special issue Human Reproduction: Involvement of the Immune System
Sepsis was defined in 1991 by the systemic inflammatory response syndrome (SIRS) criteria which consisted mostly of physiologic responses to infection or inflammation (fever, tachycardia, tachypnea, and leukocytosis). These criteria were initially proposed to identify patients with gram-negative bloodstream infection (BSI). However, most patients with BSI are not critically ill at initial presentation using objective clinical scores for acute severity of illness, such as the Pitt bacteremia score (PBS). Lack of specificity and low positive predictive value (PPV) are other pitfalls of the SIRS criteria. Moreover, the implementation of sepsis interventions based on this outdated definition failed to improve patients’ outcomes and in some settings was associated with increased use of broad-spectrum antibiotics and Clostridioides difficile (C. difficile) infection. In 2016, sepsis was redefined as a dysregulatory host response to life-threatening infections using quick sequential organ failure assessment (qSOFA) score. The presence of two of three bedside clinical variables (hypotension, respiratory distress, and altered mental status) that have consistently predicted mortality in patients with infections now constitutes sepsis. The scientific debate continues in the medical literature regarding the performance of the new criteria. Some medical professionals and quality organizations consider these changes to the sepsis definition too revolutionary and are resistant to altering existing medical practice. This narrative review presents infection as a continuum from localized to systemic infection (pre-sepsis) with the potential progression into sepsis and septic shock if appropriate antibiotic therapy and source control are delayed. The review assesses host and microbial factors that may influence the rate of progression through the sepsis cascade and proposes diagnostic considerations and management decisions at each step of the way. It emphasizes the need to utilize precision medicine concepts in selecting empirical antibiotic therapy based on patient-specific risk factors for infections due to resistant bacteria and potential benefits from appropriate therapy across the sepsis spectrum.
Sepsis was defined in 1991 by the systemic inflammatory response syndrome (SIRS) criteria which consisted mostly of physiologic responses to infection or inflammation (fever, tachycardia, tachypnea, and leukocytosis). These criteria were initially proposed to identify patients with gram-negative bloodstream infection (BSI). However, most patients with BSI are not critically ill at initial presentation using objective clinical scores for acute severity of illness, such as the Pitt bacteremia score (PBS). Lack of specificity and low positive predictive value (PPV) are other pitfalls of the SIRS criteria. Moreover, the implementation of sepsis interventions based on this outdated definition failed to improve patients’ outcomes and in some settings was associated with increased use of broad-spectrum antibiotics and Clostridioides difficile (C. difficile) infection. In 2016, sepsis was redefined as a dysregulatory host response to life-threatening infections using quick sequential organ failure assessment (qSOFA) score. The presence of two of three bedside clinical variables (hypotension, respiratory distress, and altered mental status) that have consistently predicted mortality in patients with infections now constitutes sepsis. The scientific debate continues in the medical literature regarding the performance of the new criteria. Some medical professionals and quality organizations consider these changes to the sepsis definition too revolutionary and are resistant to altering existing medical practice. This narrative review presents infection as a continuum from localized to systemic infection (pre-sepsis) with the potential progression into sepsis and septic shock if appropriate antibiotic therapy and source control are delayed. The review assesses host and microbial factors that may influence the rate of progression through the sepsis cascade and proposes diagnostic considerations and management decisions at each step of the way. It emphasizes the need to utilize precision medicine concepts in selecting empirical antibiotic therapy based on patient-specific risk factors for infections due to resistant bacteria and potential benefits from appropriate therapy across the sepsis spectrum.
DOI: https://doi.org/10.37349/ei.2022.00075
This article belongs to the special issue The Sepsis induced Immune Conundrum
Coronavirus disease 2019 (COVID-19) is currently a major public health concern causing devastating sociological, economic, and psychological damage to livelihood all over the world. The most intense severity of COVID-19 is not only acute respiratory distress syndrome (ARDS), it also causes multi-organ failure, the post-infection secondary effect as well as death. The fast-mutating ability and high transmissibility rate of the virus cause emergence of the new variants and also the occurrence of breakthrough infections. Evidence suggests that vaccination against COVID-19 has been effective at preventing the severity of illness, hospitalization, and death. The efficacy of vaccines depends on multiple factors including the host’s ability to mount a robust and sustainable immune response, the virus’s ability to mutate its genome, and programmatic factors such as vaccine dose, storage, dosing schedules, etc. In this article, an overview of severe acute respiratory syndrome coronavirus-2 (SARS-CoV-2) infection, its pathogenesis, host immune responses to infection, and different type of COVID-19 vaccines, including vaccine efficacy and adverse effects are described.
Coronavirus disease 2019 (COVID-19) is currently a major public health concern causing devastating sociological, economic, and psychological damage to livelihood all over the world. The most intense severity of COVID-19 is not only acute respiratory distress syndrome (ARDS), it also causes multi-organ failure, the post-infection secondary effect as well as death. The fast-mutating ability and high transmissibility rate of the virus cause emergence of the new variants and also the occurrence of breakthrough infections. Evidence suggests that vaccination against COVID-19 has been effective at preventing the severity of illness, hospitalization, and death. The efficacy of vaccines depends on multiple factors including the host’s ability to mount a robust and sustainable immune response, the virus’s ability to mutate its genome, and programmatic factors such as vaccine dose, storage, dosing schedules, etc. In this article, an overview of severe acute respiratory syndrome coronavirus-2 (SARS-CoV-2) infection, its pathogenesis, host immune responses to infection, and different type of COVID-19 vaccines, including vaccine efficacy and adverse effects are described.
DOI: https://doi.org/10.37349/ei.2022.00074
This article belongs to the special issue Vaccine-induced Immune Responses Against SARS-CoV-2 Infections
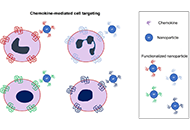
Chemokines are homeostatic or inflammatory small proteins regulating immune cell migration and are structurally characterized by cysteine disulfide bridges. Around 50 human chemokines binding almost 20 seven-transmembrane G-protein coupled receptors have been discovered. The finding that two of them were the main human immunodeficiency virus (HIV) co-receptors intensified the research on the binding mechanism to block the viral entrance. Blockade of chemokine/chemokine receptor signaling ultimately modulates cell migration, then immune responses. Particular nanotechnologies can be designed to interfere with chemokine signaling or to exploit the ligand-receptor interaction. Surface chemical modification of nanomaterials with chemokines or specific peptides can find several applications in bio-medicine, from tissue-specific drug delivery to reduced cell migration in pathological conditions. Recent highlights on peculiar chemokine-nanoparticle design and their potential to modulate immune responses will be discussed.
Chemokines are homeostatic or inflammatory small proteins regulating immune cell migration and are structurally characterized by cysteine disulfide bridges. Around 50 human chemokines binding almost 20 seven-transmembrane G-protein coupled receptors have been discovered. The finding that two of them were the main human immunodeficiency virus (HIV) co-receptors intensified the research on the binding mechanism to block the viral entrance. Blockade of chemokine/chemokine receptor signaling ultimately modulates cell migration, then immune responses. Particular nanotechnologies can be designed to interfere with chemokine signaling or to exploit the ligand-receptor interaction. Surface chemical modification of nanomaterials with chemokines or specific peptides can find several applications in bio-medicine, from tissue-specific drug delivery to reduced cell migration in pathological conditions. Recent highlights on peculiar chemokine-nanoparticle design and their potential to modulate immune responses will be discussed.
DOI: https://doi.org/10.37349/ei.2022.00073
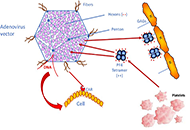
In ultrarare cases, patients vaccinated with DNA adenovirus vector vaccine against severe acute respiratory syndrome coronavirus-2 (SARS-CoV-2), develop a vaccine-induced immune thrombotic thrombocytopenia (VITT), with a high incidence of fatal cases. The causative agent is the development of platelet factor 4 (PF4)-dependent antibodies that resemble heparin-induced thrombocytopenia (HIT) complication, although many differences can be noticed in clinical presentation, antibody reactivity, involved epitopes on the PF4 protein, and pathological mechanisms. From the literature review, and the experience of HIT and testing a few plasmas from patients with VITT, this review analyzes the possible mechanisms, which show the strong immunoglobulin G (IgG) antibody reactivity to PF4 alone, in the absence of heparin, and to a lesser extend to stoichiometric complexes of PF4 and heparin (H-PF4). In addition, much lower heparin concentrations are required for inhibiting antibody binding to PF4. These concentrations are much lower than those required for disrupting the stoichiometric H-PF4 complexes. This confirms that IgG antibodies responsible for HIT bind preferentially to PF4, to epitopes that are readily masked by low concentrations of heparin. These antibodies are at a much higher concentration than the current ones observed for HIT, keeping a strong reactivity even for plasma dilutions as high as 1/500 to 1/5,000, whilst the current dilution for testing heparin-dependent antibodies in HIT is 1/100. Although VITT anti-PF4 antibodies can be detected with the current anti-H-PF4 enzyme-linked immunosorbent assays (ELISAs) designed for HIT, some assays have low sensitivity or are unreactive, like lateral immunofiltration methods or chemiluminescent automated assays. The preferred method should concern the use of capture assays using PF4 coated solid surfaces. This report proposes that the immune response is only targeted to the binding domain of PF4 with the hexons present on the adenovirus vector, through an epitope spreading mechanism, without any exposure of neo-epitopes on PF4 protein.
In ultrarare cases, patients vaccinated with DNA adenovirus vector vaccine against severe acute respiratory syndrome coronavirus-2 (SARS-CoV-2), develop a vaccine-induced immune thrombotic thrombocytopenia (VITT), with a high incidence of fatal cases. The causative agent is the development of platelet factor 4 (PF4)-dependent antibodies that resemble heparin-induced thrombocytopenia (HIT) complication, although many differences can be noticed in clinical presentation, antibody reactivity, involved epitopes on the PF4 protein, and pathological mechanisms. From the literature review, and the experience of HIT and testing a few plasmas from patients with VITT, this review analyzes the possible mechanisms, which show the strong immunoglobulin G (IgG) antibody reactivity to PF4 alone, in the absence of heparin, and to a lesser extend to stoichiometric complexes of PF4 and heparin (H-PF4). In addition, much lower heparin concentrations are required for inhibiting antibody binding to PF4. These concentrations are much lower than those required for disrupting the stoichiometric H-PF4 complexes. This confirms that IgG antibodies responsible for HIT bind preferentially to PF4, to epitopes that are readily masked by low concentrations of heparin. These antibodies are at a much higher concentration than the current ones observed for HIT, keeping a strong reactivity even for plasma dilutions as high as 1/500 to 1/5,000, whilst the current dilution for testing heparin-dependent antibodies in HIT is 1/100. Although VITT anti-PF4 antibodies can be detected with the current anti-H-PF4 enzyme-linked immunosorbent assays (ELISAs) designed for HIT, some assays have low sensitivity or are unreactive, like lateral immunofiltration methods or chemiluminescent automated assays. The preferred method should concern the use of capture assays using PF4 coated solid surfaces. This report proposes that the immune response is only targeted to the binding domain of PF4 with the hexons present on the adenovirus vector, through an epitope spreading mechanism, without any exposure of neo-epitopes on PF4 protein.
DOI: https://doi.org/10.37349/ei.2022.00071
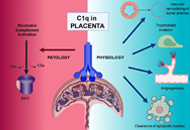
Complement component 1q (C1q) is the recognition molecule of the classical pathway of the complement system that can bind to an array of closely spaced antigen-bound immunoglobulin G (IgG) and IgM antibodies. In addition to its involvement in defence against a range of pathogens and clearance of apoptotic and necrotic cells, C1q has also been implicated in immune and non-immune homeostasis. C1q is locally produced by immune cells such as monocytes, macrophages, and dendritic cells. C1q is also synthesized by decidual endothelial cells, thus acting as a link between decidual cells and trophoblasts, as well as contributing to the remodelling of spiral arteries. Furthermore, C1q is produced by the extravillous trophoblasts (EVTs) invading the decidua. As a pro-angiogenic molecule, C1q is also important for normal placentation processes as it favors the active angiogenesis in the developing decidua. These observations have been validated by C1q gene knock-out mice which showed pre-eclampsia (PE)-like symptoms, characterized by hypertension, proteinuria, glomerular endotheliosis, and increased soluble fms-like tyrosine kinase-1 (sFlt-1)/placental growth factor (PlGF) ratio, and increased oxidative stress. The role of C1q in normal and adverse human pregnancy is being studied extensively due to its absence or low level as a likely precipitating factor for the development of PE.
Complement component 1q (C1q) is the recognition molecule of the classical pathway of the complement system that can bind to an array of closely spaced antigen-bound immunoglobulin G (IgG) and IgM antibodies. In addition to its involvement in defence against a range of pathogens and clearance of apoptotic and necrotic cells, C1q has also been implicated in immune and non-immune homeostasis. C1q is locally produced by immune cells such as monocytes, macrophages, and dendritic cells. C1q is also synthesized by decidual endothelial cells, thus acting as a link between decidual cells and trophoblasts, as well as contributing to the remodelling of spiral arteries. Furthermore, C1q is produced by the extravillous trophoblasts (EVTs) invading the decidua. As a pro-angiogenic molecule, C1q is also important for normal placentation processes as it favors the active angiogenesis in the developing decidua. These observations have been validated by C1q gene knock-out mice which showed pre-eclampsia (PE)-like symptoms, characterized by hypertension, proteinuria, glomerular endotheliosis, and increased soluble fms-like tyrosine kinase-1 (sFlt-1)/placental growth factor (PlGF) ratio, and increased oxidative stress. The role of C1q in normal and adverse human pregnancy is being studied extensively due to its absence or low level as a likely precipitating factor for the development of PE.
DOI: https://doi.org/10.37349/ei.2022.00072
This article belongs to the special issue Human Reproduction: Involvement of the Immune System
