







 Previous
Artificial intelligence (AI) is poised to transform clinical allergy practice by enhancing diagnostic accuracy, personalising treatment, and streamlining healthcare delivery. This narrative review critically examines the current landscape of AI in allergy care, spanning clinical workflows, diagnostics, immunotherapy, and research applications. AI-powered tools such as clinical decision support systems (CDSS), natural language processing (NLP), and conversational agents are being integrated into allergy services, offering improvements in documentation, risk stratification, and remote patient engagement—particularly in paediatric and multilingual settings. Diagnostic innovations include machine learning models that predict oral food challenge outcomes and interpret multi-omics data for personalised allergy phenotyping. AI also supports adaptive immunotherapy dosing, remote monitoring via wearable biosensors, and digital coaching to promote adherence. Federated learning and explainable AI (XAI) emerge as pivotal developments—enabling privacy-preserving collaboration and fostering trust among clinicians and patients. Despite these advancements, significant challenges remain. These include data inequities, algorithmic bias, lack of real-world validation, and regulatory ambiguity. The “black box” nature of many models risks undermining clinician confidence, while over-reliance on alerts could contribute to alarm fatigue. Ethical concerns—particularly around transparency, consent, and liability—require urgent attention. Equitable implementation demands robust governance, diverse training data, and inclusive design that prioritises patient safety. Looking ahead, AI has the potential to power digital twins, support augmented reality training, and enhance allergy surveillance through the integration of environmental and population-level data. With multidisciplinary collaboration, transparent oversight, and patient-centred innovation, AI can help build a more predictive, efficient, and equitable future for allergy care.
Artificial intelligence (AI) is poised to transform clinical allergy practice by enhancing diagnostic accuracy, personalising treatment, and streamlining healthcare delivery. This narrative review critically examines the current landscape of AI in allergy care, spanning clinical workflows, diagnostics, immunotherapy, and research applications. AI-powered tools such as clinical decision support systems (CDSS), natural language processing (NLP), and conversational agents are being integrated into allergy services, offering improvements in documentation, risk stratification, and remote patient engagement—particularly in paediatric and multilingual settings. Diagnostic innovations include machine learning models that predict oral food challenge outcomes and interpret multi-omics data for personalised allergy phenotyping. AI also supports adaptive immunotherapy dosing, remote monitoring via wearable biosensors, and digital coaching to promote adherence. Federated learning and explainable AI (XAI) emerge as pivotal developments—enabling privacy-preserving collaboration and fostering trust among clinicians and patients. Despite these advancements, significant challenges remain. These include data inequities, algorithmic bias, lack of real-world validation, and regulatory ambiguity. The “black box” nature of many models risks undermining clinician confidence, while over-reliance on alerts could contribute to alarm fatigue. Ethical concerns—particularly around transparency, consent, and liability—require urgent attention. Equitable implementation demands robust governance, diverse training data, and inclusive design that prioritises patient safety. Looking ahead, AI has the potential to power digital twins, support augmented reality training, and enhance allergy surveillance through the integration of environmental and population-level data. With multidisciplinary collaboration, transparent oversight, and patient-centred innovation, AI can help build a more predictive, efficient, and equitable future for allergy care.
DOI: https://doi.org/10.37349/eaa.2025.100992
This article belongs to the special issue Allergy and Asthma in the Digital Age


Asthma is a chronic inflammatory airway disorder characterized by recurrent symptoms, airflow obstruction, and bronchial hyperresponsiveness. Approximately 5–10% of asthma cases are classified as severe, requiring high-dose inhaled corticosteroids (ICS) plus additional controllers, often including systemic corticosteroids. Severe asthma imposes a substantial burden on patients due to frequent exacerbations and reduced quality of life. The pathophysiology of severe asthma involves distinct phenotypic and endotypic variations, primarily classified into high-type 2 (T2) and low-T2 inflammatory profiles. While high-T2 asthma, encompassing eosinophilic and allergic subtypes, benefits from targeted biologic therapies such as monoclonal antibodies against interleukin-5 (IL-5), IL-4/IL-13, thymic stromal lymphopoietin (TSLP), and IgE, treatment options for low-T2 asthma remain limited. The advent of precision medicine has facilitated the identification of novel biomarkers for severe asthma, guiding therapeutic decisions and enabling disease stratification. However, key clinical challenges remain, including selecting the most effective biologic therapy, optimal treatment duration, and safe de-escalation strategies upon achieving remission. This review explores the latest evidence on biological therapies, their immunomodulatory effects, and their potential role in reversing bronchial remodelling. Additionally, it discusses emerging biomarkers that may predict treatment response and remission, ultimately contributing to a more personalized approach to asthma management.
Asthma is a chronic inflammatory airway disorder characterized by recurrent symptoms, airflow obstruction, and bronchial hyperresponsiveness. Approximately 5–10% of asthma cases are classified as severe, requiring high-dose inhaled corticosteroids (ICS) plus additional controllers, often including systemic corticosteroids. Severe asthma imposes a substantial burden on patients due to frequent exacerbations and reduced quality of life. The pathophysiology of severe asthma involves distinct phenotypic and endotypic variations, primarily classified into high-type 2 (T2) and low-T2 inflammatory profiles. While high-T2 asthma, encompassing eosinophilic and allergic subtypes, benefits from targeted biologic therapies such as monoclonal antibodies against interleukin-5 (IL-5), IL-4/IL-13, thymic stromal lymphopoietin (TSLP), and IgE, treatment options for low-T2 asthma remain limited. The advent of precision medicine has facilitated the identification of novel biomarkers for severe asthma, guiding therapeutic decisions and enabling disease stratification. However, key clinical challenges remain, including selecting the most effective biologic therapy, optimal treatment duration, and safe de-escalation strategies upon achieving remission. This review explores the latest evidence on biological therapies, their immunomodulatory effects, and their potential role in reversing bronchial remodelling. Additionally, it discusses emerging biomarkers that may predict treatment response and remission, ultimately contributing to a more personalized approach to asthma management.
DOI: https://doi.org/10.37349/eaa.2025.100991
Aim:
Despite the revolutionary impact of biologics (Bx) on severe asthma management, predicting individual treatment responses remains challenging. We aimed to characterize the heterogeneous nature of clinical status and disease activity in patients with severe asthma after biologic therapies through a comprehensive evaluation of real-world clinical outcomes.
Methods:
In this retrospective, multicenter study of 53 patients with severe asthma who received biologic therapies, hierarchical clustering analysis was performed based on three key parameters during treatment: exacerbation, maintenance oral corticosteroid (mOCS) dose, and lung function. Canonical correlation analysis and multinomial logistic regression were used to identify predictors of response patterns.
Results:
Clustering analysis revealed three distinct control groups: well-controlled (n = 23), moderately controlled (n = 22), and poorly controlled (n = 8). Well-controlled patients exhibited minimal exacerbations, no oral corticosteroid (OCS) use, and optimal or stabilized lung function. Moderately controlled patients showed minimal exacerbations and no mOCS use but variable lung function improvements. Poorly controlled patients exhibited persistent exacerbations, mOCS dependence, or both with limited lung function improvement. Baseline forced expiratory volume in 1 second (FEV1) %predicted (percent predicted FEV1) values and blood eosinophil counts independently differentiated well-controlled from moderately controlled patients, whereas baseline mOCS use distinguished moderately controlled from poorly controlled patients.
Conclusions:
Our findings reveal distinct patterns of disease control following biologic therapy in severe asthma, with baseline lung function, eosinophilic inflammation, and OCS use as key predictive factors. These results support the need for personalized treatment approaches in severe asthma management.
Aim:
Despite the revolutionary impact of biologics (Bx) on severe asthma management, predicting individual treatment responses remains challenging. We aimed to characterize the heterogeneous nature of clinical status and disease activity in patients with severe asthma after biologic therapies through a comprehensive evaluation of real-world clinical outcomes.
Methods:
In this retrospective, multicenter study of 53 patients with severe asthma who received biologic therapies, hierarchical clustering analysis was performed based on three key parameters during treatment: exacerbation, maintenance oral corticosteroid (mOCS) dose, and lung function. Canonical correlation analysis and multinomial logistic regression were used to identify predictors of response patterns.
Results:
Clustering analysis revealed three distinct control groups: well-controlled (n = 23), moderately controlled (n = 22), and poorly controlled (n = 8). Well-controlled patients exhibited minimal exacerbations, no oral corticosteroid (OCS) use, and optimal or stabilized lung function. Moderately controlled patients showed minimal exacerbations and no mOCS use but variable lung function improvements. Poorly controlled patients exhibited persistent exacerbations, mOCS dependence, or both with limited lung function improvement. Baseline forced expiratory volume in 1 second (FEV1) %predicted (percent predicted FEV1) values and blood eosinophil counts independently differentiated well-controlled from moderately controlled patients, whereas baseline mOCS use distinguished moderately controlled from poorly controlled patients.
Conclusions:
Our findings reveal distinct patterns of disease control following biologic therapy in severe asthma, with baseline lung function, eosinophilic inflammation, and OCS use as key predictive factors. These results support the need for personalized treatment approaches in severe asthma management.
DOI: https://doi.org/10.37349/eaa.2025.100990
This article belongs to the special issue The Era of Biologics in Allergy
Hypersensitivity reactions (HSRs) to paclitaxel, particularly those mediated by the solubilizer Cremophor® EL, are common, occurring in approximately 10% of patients despite premedication. Nab-paclitaxel, a newer formulation using human serum albumin as the vehicle, is generally considered a safer alternative due to a lower rate of HSRs. We present the case of a 44-year-old woman with breast cancer who developed severe HSRs following multiple doses of paclitaxel and carboplatin. Despite standard premedication, she experienced fever, erythematous skin eruptions, arthralgias, and systemic symptoms following her fourth and fifth cycles of treatment. Subsequent administration of nab-paclitaxel also elicited a similar severe reaction. Skin testing revealed a positive reaction to paclitaxel, but not to carboplatin, suggesting sensitization to paclitaxel. In the context of the similar reaction to nab-paclitaxel, this suggests sensitization to the taxane moiety itself rather than to the solubilizer. The combination of features consistent with both type IV hypersensitivity and cytokine release syndrome further complicates the presentation as well. To our knowledge, this is the first reported case of cross-reactivity between paclitaxel and nab-paclitaxel, challenging the assumption that nab-paclitaxel is always a safe alternative. This emphasizes the need for vigilance and thorough evaluation in patients experiencing atypical chemotherapy reactions, as cytokine release reactions may play a role even in the absence of immunotherapy. It also raises the concern that alternative formulations like nab-paclitaxel may not always be safe in patients with atypical or severe reactions, as they could possibly be sensitized to the taxane moiety itself.
Hypersensitivity reactions (HSRs) to paclitaxel, particularly those mediated by the solubilizer Cremophor® EL, are common, occurring in approximately 10% of patients despite premedication. Nab-paclitaxel, a newer formulation using human serum albumin as the vehicle, is generally considered a safer alternative due to a lower rate of HSRs. We present the case of a 44-year-old woman with breast cancer who developed severe HSRs following multiple doses of paclitaxel and carboplatin. Despite standard premedication, she experienced fever, erythematous skin eruptions, arthralgias, and systemic symptoms following her fourth and fifth cycles of treatment. Subsequent administration of nab-paclitaxel also elicited a similar severe reaction. Skin testing revealed a positive reaction to paclitaxel, but not to carboplatin, suggesting sensitization to paclitaxel. In the context of the similar reaction to nab-paclitaxel, this suggests sensitization to the taxane moiety itself rather than to the solubilizer. The combination of features consistent with both type IV hypersensitivity and cytokine release syndrome further complicates the presentation as well. To our knowledge, this is the first reported case of cross-reactivity between paclitaxel and nab-paclitaxel, challenging the assumption that nab-paclitaxel is always a safe alternative. This emphasizes the need for vigilance and thorough evaluation in patients experiencing atypical chemotherapy reactions, as cytokine release reactions may play a role even in the absence of immunotherapy. It also raises the concern that alternative formulations like nab-paclitaxel may not always be safe in patients with atypical or severe reactions, as they could possibly be sensitized to the taxane moiety itself.
DOI: https://doi.org/10.37349/eaa.2025.100989
Respiratory syncytial virus (RSV) is the leading cause of lower respiratory tract infection (LRTI) burden among infants. Maternal vaccination is a promising preventive strategy, conferring passive immunity through transplacental antibody transfer. The current narrative review was conducted to summarize the current evidence of efficacy and safety of maternal RSV vaccination and assess the practical barriers to its implementation. This review was based on a structured literature search of PubMed/MEDLINE and Google Scholar to identify peer-reviewed studies published between January 2022 and March 2025 using terms such as “maternal RSV vaccine”, “efficacy”, “safety”, “pregnancy”, “Abrysvo”, and “hesitancy”. The review included 5 clinical trials evaluating maternal RSV vaccines and 17 observational and survey studies assessing vaccine acceptance across diverse settings. The bivalent RSVpreF vaccine (Abrysvo) is the only licensed maternal RSV vaccine as of May 2025. In the MATISSE phase 3 trial (n = 7,358), the vaccine demonstrated 81.8% efficacy against medically attended RSV-LRTI at 90 days and 69.4% at 180 days, with 57.1% efficacy against severe RSV-LRTI. No major safety concerns were identified; adverse events and preterm birth rates were comparable between groups. In contrast, trials of GSK’s RSVPreF3-Mat vaccine revealed higher rates of preterm birth (6.8% vs. 4.9%) and a numerical imbalance in infant deaths (0.4% vs. 0.2%), prompting early termination. Across 17 studies (n = 14,959), RSV vaccine acceptance ranged from 39% (France) to 87% (Netherlands), with safety concerns and cultural context influencing attitudes. This review highlights that maternal RSV vaccination with RSVpreF offers effective infant protection with an acceptable safety profile. Future research should focus on long-term infant outcomes, comparative effectiveness in diverse settings, and next-generation vaccines. Implementation will require public trust, cultural sensitivity, and equitable global access.
Respiratory syncytial virus (RSV) is the leading cause of lower respiratory tract infection (LRTI) burden among infants. Maternal vaccination is a promising preventive strategy, conferring passive immunity through transplacental antibody transfer. The current narrative review was conducted to summarize the current evidence of efficacy and safety of maternal RSV vaccination and assess the practical barriers to its implementation. This review was based on a structured literature search of PubMed/MEDLINE and Google Scholar to identify peer-reviewed studies published between January 2022 and March 2025 using terms such as “maternal RSV vaccine”, “efficacy”, “safety”, “pregnancy”, “Abrysvo”, and “hesitancy”. The review included 5 clinical trials evaluating maternal RSV vaccines and 17 observational and survey studies assessing vaccine acceptance across diverse settings. The bivalent RSVpreF vaccine (Abrysvo) is the only licensed maternal RSV vaccine as of May 2025. In the MATISSE phase 3 trial (n = 7,358), the vaccine demonstrated 81.8% efficacy against medically attended RSV-LRTI at 90 days and 69.4% at 180 days, with 57.1% efficacy against severe RSV-LRTI. No major safety concerns were identified; adverse events and preterm birth rates were comparable between groups. In contrast, trials of GSK’s RSVPreF3-Mat vaccine revealed higher rates of preterm birth (6.8% vs. 4.9%) and a numerical imbalance in infant deaths (0.4% vs. 0.2%), prompting early termination. Across 17 studies (n = 14,959), RSV vaccine acceptance ranged from 39% (France) to 87% (Netherlands), with safety concerns and cultural context influencing attitudes. This review highlights that maternal RSV vaccination with RSVpreF offers effective infant protection with an acceptable safety profile. Future research should focus on long-term infant outcomes, comparative effectiveness in diverse settings, and next-generation vaccines. Implementation will require public trust, cultural sensitivity, and equitable global access.
DOI: https://doi.org/10.37349/eaa.2025.100988
This article belongs to the special issue Asthma, Allergies, and Respiratory Infections in Pediatric Age
This mini-review examines the link between climate change, air pollution, and aeroallergen-induced respiratory diseases in Europe. The articles selected in this mini-review highlighted the links between climate change, air pollutants and the impact on aeroallergen-induced respiratory disease. Searching data base PubMed returned results, but not all were relevant. The search conducted for a geographical scope of Europe after 2015 returned a large number of results, clinical studies, manuals, guidelines and recommendations from international recognized institutions or organizations, such as Global Initiative for Asthma (GINA), World Health Organisation (WHO) from which only published texts containing both general information and specific quantifiable information on climate change and air pollutants and their effects on health were selected. The findings highlight how environmental stressors interact to exacerbate allergic respiratory diseases, and emphasize the need for environmental policies.
This mini-review examines the link between climate change, air pollution, and aeroallergen-induced respiratory diseases in Europe. The articles selected in this mini-review highlighted the links between climate change, air pollutants and the impact on aeroallergen-induced respiratory disease. Searching data base PubMed returned results, but not all were relevant. The search conducted for a geographical scope of Europe after 2015 returned a large number of results, clinical studies, manuals, guidelines and recommendations from international recognized institutions or organizations, such as Global Initiative for Asthma (GINA), World Health Organisation (WHO) from which only published texts containing both general information and specific quantifiable information on climate change and air pollutants and their effects on health were selected. The findings highlight how environmental stressors interact to exacerbate allergic respiratory diseases, and emphasize the need for environmental policies.
DOI: https://doi.org/10.37349/eaa.2025.100987
This article belongs to the special issue Climate Change, Allergy, and Immunotherapy
Climate change in the form of rising temperatures and pollution can intensify pollen allergies, increasing health burdens and demanding proactive public health policies. Here, we discuss the current perceptions of physicians and patients on the impact of climate change and some of the initiatives to address its impact on global health. Recent surveys suggest growing concern among healthcare professionals and patients over the expanding evidence that climate change is contributing to the onset and exacerbation of respiratory allergies. Limited evidence exists on effective strategies, but some of the proposed public policy solutions include enhanced pollen monitoring networks, promoting climate-health education in medical curricula, development of early warning systems for thunderstorm asthma, and allergen-reducing urban planning. Collaboration among clinicians, researchers, and policymakers is critical for developing targeted measures that build resilience against climate-driven pollen allergy.
Climate change in the form of rising temperatures and pollution can intensify pollen allergies, increasing health burdens and demanding proactive public health policies. Here, we discuss the current perceptions of physicians and patients on the impact of climate change and some of the initiatives to address its impact on global health. Recent surveys suggest growing concern among healthcare professionals and patients over the expanding evidence that climate change is contributing to the onset and exacerbation of respiratory allergies. Limited evidence exists on effective strategies, but some of the proposed public policy solutions include enhanced pollen monitoring networks, promoting climate-health education in medical curricula, development of early warning systems for thunderstorm asthma, and allergen-reducing urban planning. Collaboration among clinicians, researchers, and policymakers is critical for developing targeted measures that build resilience against climate-driven pollen allergy.
DOI: https://doi.org/10.37349/eaa.2025.100986
This article belongs to the special issue Climate Change, Allergy, and Immunotherapy
Air pollution is an increasing global concern with serious health and economic impacts. Among its many effects, respiratory health is particularly vulnerable. As the first point of contact with inhaled pollutants, the nasal passages play a crucial role in airway defense, making rhinitis one of the key inflammatory conditions linked to environmental pollution. This review explores the relationship between air pollution and rhinitis, highlighting key pollutants such as particulate matter (PM, PM2.5, PM10), nitrogen dioxide (NO2), sulfur dioxide (SO2), and ozone (O3), which contribute to airway inflammation, epithelial barrier dysfunction, immune system dysregulation, and epigenetic changes. Epidemiological studies demonstrate a strong association between pollutant exposure and increased prevalence, severity, and healthcare utilization for allergic rhinitis. However, there is limited research focusing on non-allergic rhinitis. Beyond health concerns, air pollution also imposes a significant economic burden due to rising healthcare costs and lost productivity. Effective mitigation strategies include air quality monitoring, indoor air filtration, policy interventions, and lifestyle modifications. Addressing pollution-related rhinitis requires a multidisciplinary approach involving public health initiatives, clinical management, and environmental policies to reduce exposure and improve patient outcomes. Additionally, limitations in current research are discussed, and further studies are recommended to fill existing knowledge gaps.
Air pollution is an increasing global concern with serious health and economic impacts. Among its many effects, respiratory health is particularly vulnerable. As the first point of contact with inhaled pollutants, the nasal passages play a crucial role in airway defense, making rhinitis one of the key inflammatory conditions linked to environmental pollution. This review explores the relationship between air pollution and rhinitis, highlighting key pollutants such as particulate matter (PM, PM2.5, PM10), nitrogen dioxide (NO2), sulfur dioxide (SO2), and ozone (O3), which contribute to airway inflammation, epithelial barrier dysfunction, immune system dysregulation, and epigenetic changes. Epidemiological studies demonstrate a strong association between pollutant exposure and increased prevalence, severity, and healthcare utilization for allergic rhinitis. However, there is limited research focusing on non-allergic rhinitis. Beyond health concerns, air pollution also imposes a significant economic burden due to rising healthcare costs and lost productivity. Effective mitigation strategies include air quality monitoring, indoor air filtration, policy interventions, and lifestyle modifications. Addressing pollution-related rhinitis requires a multidisciplinary approach involving public health initiatives, clinical management, and environmental policies to reduce exposure and improve patient outcomes. Additionally, limitations in current research are discussed, and further studies are recommended to fill existing knowledge gaps.
DOI: https://doi.org/10.37349/eaa.2025.100985
This article belongs to the special issue Precision Medicine in Allergy and Rhinology
Over 330 million people globally have asthma, a chronic disease with multiple endotypes and observable phenotypes. This disease has a substantial socioeconomic impact. A thorough assessment of multiple clinical aspects (such as the presence of atopy, comorbidities, and clinical presentations), characteristics of lung function (such as the degree of bronchial reversibility, the involvement of the airway obstruction, and airway hyperreactivity), and the interaction of sputum and systemic inflammatory factors (such as neutrophilic, eosinophilic, and mixed) are required to determine the specific endotypes of asthma. The precision medicine approach to asthma represents a new paradigm, with improved opportunities for more effective and appropriate personalized therapies and new insights into the immunological aspects of asthma that demand further research. In the world of precision medicine, biomarker-based therapies for individual patients are just the beginning of an exciting and emerging journey in allergy treatment. A collection of biomarkers might be utilized to define and classify the endotypes based on the phenotyping of asthma, which will be more likely with omics information and unbiased clustering. This review will contribute to the development of personalized therapy for asthma, enabling more accurate treatment. It will also serve as a source of novel targets and new treatments for every identified endotype.
Over 330 million people globally have asthma, a chronic disease with multiple endotypes and observable phenotypes. This disease has a substantial socioeconomic impact. A thorough assessment of multiple clinical aspects (such as the presence of atopy, comorbidities, and clinical presentations), characteristics of lung function (such as the degree of bronchial reversibility, the involvement of the airway obstruction, and airway hyperreactivity), and the interaction of sputum and systemic inflammatory factors (such as neutrophilic, eosinophilic, and mixed) are required to determine the specific endotypes of asthma. The precision medicine approach to asthma represents a new paradigm, with improved opportunities for more effective and appropriate personalized therapies and new insights into the immunological aspects of asthma that demand further research. In the world of precision medicine, biomarker-based therapies for individual patients are just the beginning of an exciting and emerging journey in allergy treatment. A collection of biomarkers might be utilized to define and classify the endotypes based on the phenotyping of asthma, which will be more likely with omics information and unbiased clustering. This review will contribute to the development of personalized therapy for asthma, enabling more accurate treatment. It will also serve as a source of novel targets and new treatments for every identified endotype.
DOI: https://doi.org/10.37349/eaa.2025.100984
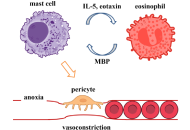
Activation of eosinophils and mast cells in dysregulated type 2 immunity may play key roles in allergic diseases. Eosinophils are linked to the pathobiology of multiple human diseases, including eosinophilic gastrointestinal disorders (EGIDs), functional gastrointestinal disorders (FGIDs), Kimura’s disease, hypereosinophilic syndrome (HES), rheumatoid lesions, allergy, asthma, and some forms of heart disease etc. Eosinophils are part of the innate immune response involved in combating multicellular parasites and some infections. Mast cells play a key role in allergies, allergic conjunctivitis, allergic dermatitis (eczema), allergic rhinitis (hay fever), anaphylaxis, asthma, and mast cell activation syndrome (MCAS). Mast cells can also play a key role in eosinophilic diseases. Eosinophils respond to interleukin 5 (IL-5) and chemotactic chemokine eosinophil chemotactic factor (eotaxin) released from activated mast cells. Mast cells can be activated by fragment crystallizable (Fc) receptor bound immunoglobulin E (IgE) and G (IgG) antibodies bound to allergens and viruses. Cross talk between eosinophils and mast cells can result in chronic inflammations or eosinophilias. Vasoconstriction of capillaries by histamine contracted pericytes is also predicted to contribute to a subset of these diseases. This article proposes that for these diseases, activation of mast cells is a key step in disease pathogenesis. Targeting activated mast cells in these diseases are potential adjunctive therapies to evaluate in clinical studies. A review of relevant eosinophilia literature is presented that supports the role of mast cells in the pathogenesis of multiple allergic and eosinophilia diseases.
Activation of eosinophils and mast cells in dysregulated type 2 immunity may play key roles in allergic diseases. Eosinophils are linked to the pathobiology of multiple human diseases, including eosinophilic gastrointestinal disorders (EGIDs), functional gastrointestinal disorders (FGIDs), Kimura’s disease, hypereosinophilic syndrome (HES), rheumatoid lesions, allergy, asthma, and some forms of heart disease etc. Eosinophils are part of the innate immune response involved in combating multicellular parasites and some infections. Mast cells play a key role in allergies, allergic conjunctivitis, allergic dermatitis (eczema), allergic rhinitis (hay fever), anaphylaxis, asthma, and mast cell activation syndrome (MCAS). Mast cells can also play a key role in eosinophilic diseases. Eosinophils respond to interleukin 5 (IL-5) and chemotactic chemokine eosinophil chemotactic factor (eotaxin) released from activated mast cells. Mast cells can be activated by fragment crystallizable (Fc) receptor bound immunoglobulin E (IgE) and G (IgG) antibodies bound to allergens and viruses. Cross talk between eosinophils and mast cells can result in chronic inflammations or eosinophilias. Vasoconstriction of capillaries by histamine contracted pericytes is also predicted to contribute to a subset of these diseases. This article proposes that for these diseases, activation of mast cells is a key step in disease pathogenesis. Targeting activated mast cells in these diseases are potential adjunctive therapies to evaluate in clinical studies. A review of relevant eosinophilia literature is presented that supports the role of mast cells in the pathogenesis of multiple allergic and eosinophilia diseases.
DOI: https://doi.org/10.37349/eaa.2025.100983
This article belongs to the special issue Innate Immune Mechanisms in Allergic Diseases
Since January 2024, in Albania, we have noted an increased number of visits because of Bordetella pertussis affecting all age groups. The increased numbers reflect increased circulation of Bordetella pertussis in Albania. Increasing cases of Bordetella pertussis are noticed in different European countries (European Centre for Disease Prevention and Control. Increase of pertussis cases in the EU/EEA. 2024.), and its appearance represents a public health problem to be addressed correctly such as introducing the booster dosage of Bordetella pertussis vaccine in the preschool, teenagers and pregnancy, identifying the contacts and early beginning of post-exposure prophylaxis are very important for preventing the burden of Bordetella pertussis and its fatalities.
Since January 2024, in Albania, we have noted an increased number of visits because of Bordetella pertussis affecting all age groups. The increased numbers reflect increased circulation of Bordetella pertussis in Albania. Increasing cases of Bordetella pertussis are noticed in different European countries (European Centre for Disease Prevention and Control. Increase of pertussis cases in the EU/EEA. 2024.), and its appearance represents a public health problem to be addressed correctly such as introducing the booster dosage of Bordetella pertussis vaccine in the preschool, teenagers and pregnancy, identifying the contacts and early beginning of post-exposure prophylaxis are very important for preventing the burden of Bordetella pertussis and its fatalities.
DOI: https://doi.org/10.37349/eaa.2025.100982
This article belongs to the special issue Asthma, Allergies, and Respiratory Infections in Pediatric Age
Pediatric and adolescent asthma is a significant health challenge with high prevalence and socioeconomic costs. Telemedicine has emerged as a promising solution for enhancing asthma management, especially in resource-limited settings and in response to the increasing demand for specialized care, particularly after the coronavirus disease 2019 (COVID-19) pandemic. However, its integration into routine clinical practice is hindered by limited evidence and the absence of standardized protocols tailored to younger populations. Telemedicine offers the potential to optimize healthcare delivery, improve access to specialized services, and support continuous patient monitoring. This initiative aims to address current gaps in standardized practices, ensuring equitable, efficient, and personalized care, particularly in underserved regions. A systematic review of literature on telemedicine and asthma was conducted using MEDLINE, EMBASE, Cochrane Library, and PsycINFO databases, up to October 2024. Studies were evaluated for effectiveness, safety, patient satisfaction, and ethical considerations. International guidelines were also reviewed, and recommendations were formulated through a modified Delphi process with a panel of seven experts, adhering to Oxford Evidence-Based Medicine grading. Telemedicine significantly enhances asthma management, improving treatment adherence, quality of life, and patient education while reducing unplanned visits. It is particularly beneficial for regions with limited access to specialized care. However, challenges persist, including insufficient data on cost-effectiveness, gaps in professional training, and technological barriers. Telemedicine is a valuable tool for managing pediatric and adolescent asthma, offering numerous benefits in accessibility and care continuity. Nevertheless, further research is needed to address existing challenges, establish best practices, and ensure its adaptability to diverse clinical settings, ultimately paving the way for more effective and equitable asthma care.
Pediatric and adolescent asthma is a significant health challenge with high prevalence and socioeconomic costs. Telemedicine has emerged as a promising solution for enhancing asthma management, especially in resource-limited settings and in response to the increasing demand for specialized care, particularly after the coronavirus disease 2019 (COVID-19) pandemic. However, its integration into routine clinical practice is hindered by limited evidence and the absence of standardized protocols tailored to younger populations. Telemedicine offers the potential to optimize healthcare delivery, improve access to specialized services, and support continuous patient monitoring. This initiative aims to address current gaps in standardized practices, ensuring equitable, efficient, and personalized care, particularly in underserved regions. A systematic review of literature on telemedicine and asthma was conducted using MEDLINE, EMBASE, Cochrane Library, and PsycINFO databases, up to October 2024. Studies were evaluated for effectiveness, safety, patient satisfaction, and ethical considerations. International guidelines were also reviewed, and recommendations were formulated through a modified Delphi process with a panel of seven experts, adhering to Oxford Evidence-Based Medicine grading. Telemedicine significantly enhances asthma management, improving treatment adherence, quality of life, and patient education while reducing unplanned visits. It is particularly beneficial for regions with limited access to specialized care. However, challenges persist, including insufficient data on cost-effectiveness, gaps in professional training, and technological barriers. Telemedicine is a valuable tool for managing pediatric and adolescent asthma, offering numerous benefits in accessibility and care continuity. Nevertheless, further research is needed to address existing challenges, establish best practices, and ensure its adaptability to diverse clinical settings, ultimately paving the way for more effective and equitable asthma care.
DOI: https://doi.org/10.37349/eaa.2025.100981
This article belongs to the special issue The Global Picture of Asthma after Guideline Changes and the COVID Pandemics
In the context of severe asthma, one of the causes of poor disease control has been identified in mucus plugs, which are real obstacles to the physiological flow of air in the bronchi. This clinical case will present the efficacy of dupilumab, as measured by respiratory function and chest computed tomography (CT) imaging, in reducing mucus plugs with consequent improvement in symptoms and function.
In the context of severe asthma, one of the causes of poor disease control has been identified in mucus plugs, which are real obstacles to the physiological flow of air in the bronchi. This clinical case will present the efficacy of dupilumab, as measured by respiratory function and chest computed tomography (CT) imaging, in reducing mucus plugs with consequent improvement in symptoms and function.
DOI: https://doi.org/10.37349/eaa.2025.100980
Asthma is a prevalent chronic respiratory condition in children, often exacerbated by allergic reactions, with house dust mites (HDMs) being a significant trigger. Traditional asthma management primarily involves inhaled corticosteroids and bronchodilators, which do not address the underlying allergic mechanisms. Allergen immunotherapy, including subcutaneous and sublingual immunotherapy (SLIT), has emerged as a strategy to induce immune tolerance to allergens. This review evaluates the efficacy of HDM immunotherapy in paediatric asthma, focusing on reductions in asthma exacerbations, improvements in lung function, decreases in medication use, and enhancements in quality of life (QoL). The review highlights that both subcutaneous immunotherapy (SCIT) and SLIT significantly reduce asthma exacerbations in children, with SCIT showing superior efficacy in lung function improvement. Combination therapies, particularly SCIT with biologics, demonstrate enhanced outcomes, including exacerbations and medication use reductions. SCIT has also been shown to improve lung function more effectively than SLIT, particularly in children with high baseline levels of HDM-specific IgE. In terms of safety, both SCIT and SLIT are generally well-tolerated, though SCIT is associated with more localized and systemic reactions, which can be mitigated by combination with biologics. Furthermore, HDM immunotherapy significantly enhances the QoL in paediatric patients by reducing asthma symptoms and improving sleep, leading to long-lasting benefits. Despite these positive outcomes, there remain gaps in knowledge, particularly regarding the optimal duration of therapy and long-term effects post-treatment. Future research should standardize treatment protocols, explore personalized approaches, and investigate the long-term sustainability of treatment benefits to fully optimize the use of HDM immunotherapy in paediatric asthma.
Asthma is a prevalent chronic respiratory condition in children, often exacerbated by allergic reactions, with house dust mites (HDMs) being a significant trigger. Traditional asthma management primarily involves inhaled corticosteroids and bronchodilators, which do not address the underlying allergic mechanisms. Allergen immunotherapy, including subcutaneous and sublingual immunotherapy (SLIT), has emerged as a strategy to induce immune tolerance to allergens. This review evaluates the efficacy of HDM immunotherapy in paediatric asthma, focusing on reductions in asthma exacerbations, improvements in lung function, decreases in medication use, and enhancements in quality of life (QoL). The review highlights that both subcutaneous immunotherapy (SCIT) and SLIT significantly reduce asthma exacerbations in children, with SCIT showing superior efficacy in lung function improvement. Combination therapies, particularly SCIT with biologics, demonstrate enhanced outcomes, including exacerbations and medication use reductions. SCIT has also been shown to improve lung function more effectively than SLIT, particularly in children with high baseline levels of HDM-specific IgE. In terms of safety, both SCIT and SLIT are generally well-tolerated, though SCIT is associated with more localized and systemic reactions, which can be mitigated by combination with biologics. Furthermore, HDM immunotherapy significantly enhances the QoL in paediatric patients by reducing asthma symptoms and improving sleep, leading to long-lasting benefits. Despite these positive outcomes, there remain gaps in knowledge, particularly regarding the optimal duration of therapy and long-term effects post-treatment. Future research should standardize treatment protocols, explore personalized approaches, and investigate the long-term sustainability of treatment benefits to fully optimize the use of HDM immunotherapy in paediatric asthma.
DOI: https://doi.org/10.37349/eaa.2025.100979
This article belongs to the special issue Precision Medicine in Allergy and Rhinology
Aim:
Emerging epidemiological studies have reported a link between allergic diseases, including asthma, and depression. Evidently, the gut microbiota is involved in the pathogenesis of asthma and depression. Therefore, we investigated whether allergic lung inflammation in mice causes gut microbial dysbiosis, via the gut-brain axis, which is potentially associated with depression.
Methods:
Wild-type C57BL/6J female mice were sensitized with intranasal house dust mite (HDM) antigen or phosphate-buffered saline (PBS) for 6 weeks to induce chronic allergic lung inflammation. Sucrose preference tests were performed for assessing depression. Fecal samples were collected, and 16S ribosomal RNA gene sequencing was performed to detect differences in gut microbiota composition between the HDM and PBS groups. The distance calculation, clustering of operational taxonomic units, rarefaction analysis, and estimator calculation (α- and β-diversity) were performed.
Results:
There was a significant difference in β-diversity (Bray-Curtis dissimilarity, F-statistics = 6.16, p = 0.001) of the gut microbiota between HDM and PBS groups. However, there was no difference in the α-diversity. We observed multiple differentially abundant bacteria in the HDM and PBS groups. The order class Clostridia (p = 0.0036) and genus Faecalibaculum (p = 0.028) were more abundant in the HDM group, whereas the phylum Firmicutes (p = 0.037) and genera Dubosiella (p = 0.00024) and Turicibacter (p = 0.037) were more abundant in the PBS group. Notably, the relative abundance of some bacteria was correlated with the sucrose preference test results.
Conclusions:
Six weeks of intranasal HDM administration to mimic the chronic status of lung inflammation in asthma changed the gut microbiome in mice and was associated with depression-like behavioral changes.
Aim:
Emerging epidemiological studies have reported a link between allergic diseases, including asthma, and depression. Evidently, the gut microbiota is involved in the pathogenesis of asthma and depression. Therefore, we investigated whether allergic lung inflammation in mice causes gut microbial dysbiosis, via the gut-brain axis, which is potentially associated with depression.
Methods:
Wild-type C57BL/6J female mice were sensitized with intranasal house dust mite (HDM) antigen or phosphate-buffered saline (PBS) for 6 weeks to induce chronic allergic lung inflammation. Sucrose preference tests were performed for assessing depression. Fecal samples were collected, and 16S ribosomal RNA gene sequencing was performed to detect differences in gut microbiota composition between the HDM and PBS groups. The distance calculation, clustering of operational taxonomic units, rarefaction analysis, and estimator calculation (α- and β-diversity) were performed.
Results:
There was a significant difference in β-diversity (Bray-Curtis dissimilarity, F-statistics = 6.16, p = 0.001) of the gut microbiota between HDM and PBS groups. However, there was no difference in the α-diversity. We observed multiple differentially abundant bacteria in the HDM and PBS groups. The order class Clostridia (p = 0.0036) and genus Faecalibaculum (p = 0.028) were more abundant in the HDM group, whereas the phylum Firmicutes (p = 0.037) and genera Dubosiella (p = 0.00024) and Turicibacter (p = 0.037) were more abundant in the PBS group. Notably, the relative abundance of some bacteria was correlated with the sucrose preference test results.
Conclusions:
Six weeks of intranasal HDM administration to mimic the chronic status of lung inflammation in asthma changed the gut microbiome in mice and was associated with depression-like behavioral changes.
DOI: https://doi.org/10.37349/eaa.2025.100978
Thanks to improvements in asthma care and availability of new biologic treatments, a relatively novel population of adolescents and young adults (AYA) with severe asthma (SA) is growing. Transition from pediatric to adult care represents a critical phase in the management of SA. We herein describe clinical outcomes, therapeutic adjustments and disease management in a group of SA patients transitioning from the pediatric to the adult care center. This is a retrospective study in which demographic and clinical (comorbidities, baseline treatment, number of asthma attacks, spirometry, airway inflammation [fractional exhaled nitric oxide (FeNO) measurements], patient’s compliance) data of four SA patients during visits in the Pediatric center as well as after transition into the Adult Center, were retrospectively recollected. All patients transitioned at 18 years of age. Clinical parameters, spirometry and FeNO showed significant improvement following the addition of biologics to baseline asthma regimen during pediatric follow-up and the early transition phase. Several months after transition to the Adult Center, two males experienced SA exacerbations following voluntary discontinuation of the biologic treatment. Symptom control was gained after a phenotype driven re-introduction of a biologic drug in the regimen. Male patients were less compliant and independent than females in the adult setting. Transition from pediatric to adult care for patients with SA can be effectively managed with coordinated and structured transition processes. While some patients maintain stable clinical and respiratory outcomes, others risk to lose asthma control. A personalized approach supporting both patient’s independence and adherence to treatment is requested for a successful long-term management.
Thanks to improvements in asthma care and availability of new biologic treatments, a relatively novel population of adolescents and young adults (AYA) with severe asthma (SA) is growing. Transition from pediatric to adult care represents a critical phase in the management of SA. We herein describe clinical outcomes, therapeutic adjustments and disease management in a group of SA patients transitioning from the pediatric to the adult care center. This is a retrospective study in which demographic and clinical (comorbidities, baseline treatment, number of asthma attacks, spirometry, airway inflammation [fractional exhaled nitric oxide (FeNO) measurements], patient’s compliance) data of four SA patients during visits in the Pediatric center as well as after transition into the Adult Center, were retrospectively recollected. All patients transitioned at 18 years of age. Clinical parameters, spirometry and FeNO showed significant improvement following the addition of biologics to baseline asthma regimen during pediatric follow-up and the early transition phase. Several months after transition to the Adult Center, two males experienced SA exacerbations following voluntary discontinuation of the biologic treatment. Symptom control was gained after a phenotype driven re-introduction of a biologic drug in the regimen. Male patients were less compliant and independent than females in the adult setting. Transition from pediatric to adult care for patients with SA can be effectively managed with coordinated and structured transition processes. While some patients maintain stable clinical and respiratory outcomes, others risk to lose asthma control. A personalized approach supporting both patient’s independence and adherence to treatment is requested for a successful long-term management.
DOI: https://doi.org/10.37349/eaa.2025.100977
Aim:
This study aims to investigate the impact of asthma on quality of life, explore its associations with anxiety and depression, and identify the key determining factors.
Methods:
A cross-sectional study was conducted in the pulmonology department of Hassan II University Hospital in Fez in 2021. Data were collected using an anonymous questionnaire that included sociodemographic, clinical, and therapeutic information. The Moroccan versions of the Hospital Anxiety and Depression Scale (HADS) and the Short-Form-12 (SF-12) scale were used to assess anxiety, depression, and quality of life. Descriptive analysis was performed, followed by univariate analysis to examine the associations between quality of life, anxiety, depression, and other factors, using statistical tests appropriate for the types of variables studied. A p < 0.05 was considered statistically significant. Data entry was performed using Excel 2013, and statistical analysis was conducted using SPSS version 26.
Results:
Among the 67 patients included (77.6% women, 61.2% aged ≥ 50 years), wheezing (44.8%) and dyspnoea (26.9%) were the most frequent symptoms. Depression was significantly associated with pain (p = 0.020), and frequent hospitalizations (p = 0.021), while anxiety was more common among women (p = 0.034). For quality of life, patients with depression had lower physical component summary (PCS) scores (p = 0.008). Patients over 50 years old had significantly lower PCS and mental component summary (MCS) scores (p = 0.001 and p = 0.002, respectively). Illiterate patients had lower PCS scores (p = 0.022), hypertensive patients had lower PCS scores (p = 0.032), and a nearly significant difference for the MCS (p = 0.053). Diabetic patients had lower MCS scores (p = 0.034). Finally, a positive correlation was observed between respiratory function forced expiratory volume in 1 second (FEV1) and both PCS scores (p = 0.025) and MCS scores (p = 0.018).
Conclusions:
This study underscores the importance of an integrated approach to enhancing the quality of life of asthmatic patients, taking into account respiratory, psychological, and social factors.
Aim:
This study aims to investigate the impact of asthma on quality of life, explore its associations with anxiety and depression, and identify the key determining factors.
Methods:
A cross-sectional study was conducted in the pulmonology department of Hassan II University Hospital in Fez in 2021. Data were collected using an anonymous questionnaire that included sociodemographic, clinical, and therapeutic information. The Moroccan versions of the Hospital Anxiety and Depression Scale (HADS) and the Short-Form-12 (SF-12) scale were used to assess anxiety, depression, and quality of life. Descriptive analysis was performed, followed by univariate analysis to examine the associations between quality of life, anxiety, depression, and other factors, using statistical tests appropriate for the types of variables studied. A p < 0.05 was considered statistically significant. Data entry was performed using Excel 2013, and statistical analysis was conducted using SPSS version 26.
Results:
Among the 67 patients included (77.6% women, 61.2% aged ≥ 50 years), wheezing (44.8%) and dyspnoea (26.9%) were the most frequent symptoms. Depression was significantly associated with pain (p = 0.020), and frequent hospitalizations (p = 0.021), while anxiety was more common among women (p = 0.034). For quality of life, patients with depression had lower physical component summary (PCS) scores (p = 0.008). Patients over 50 years old had significantly lower PCS and mental component summary (MCS) scores (p = 0.001 and p = 0.002, respectively). Illiterate patients had lower PCS scores (p = 0.022), hypertensive patients had lower PCS scores (p = 0.032), and a nearly significant difference for the MCS (p = 0.053). Diabetic patients had lower MCS scores (p = 0.034). Finally, a positive correlation was observed between respiratory function forced expiratory volume in 1 second (FEV1) and both PCS scores (p = 0.025) and MCS scores (p = 0.018).
Conclusions:
This study underscores the importance of an integrated approach to enhancing the quality of life of asthmatic patients, taking into account respiratory, psychological, and social factors.
DOI: https://doi.org/10.37349/eaa.2025.100976
This article belongs to the special issue Asthma and its Relationship with Psychological and Psychopathological Factors
A high percentage of patients with severe asthma also suffer from nasal polyposis, with dupilumab, an anti-IL-4R antibody both diseases can be treated due to its role in type 2 (T2) inflammation. When these conditions are associated with eosinophilic vasculitis, they may be classified as eosinophilic granulomatosis with polyangiitis (EGPA), which can be treated with mepolizumab. This case report presents an atypical form of EGPA, following an unusual course that began with the final signs and symptoms and then proceeded backward to the prodromal stages. Our patient, indeed, a 46-year-old woman, was asymptomatic throughout her youth, with the exception of nasal polyps. Later, at the age of 34, she developed late onset asthma, which became increasingly difficult to treat, until old and previously unacknowledged evidence of vasculitis was discovered, giving a twist to our patient’s medical history and, subsequently, to the therapeutic strategy adopted to treat her. This case report aims to highlight the importance of conducting a thorough anamnesis in patients suffering from both severe asthma and nasal polyposis, taking into account the high prevalence of EGPA in this category of patients, as well as its wide range of clinical manifestations, not to mention the various available therapeutic strategies, including mepolizumab.
A high percentage of patients with severe asthma also suffer from nasal polyposis, with dupilumab, an anti-IL-4R antibody both diseases can be treated due to its role in type 2 (T2) inflammation. When these conditions are associated with eosinophilic vasculitis, they may be classified as eosinophilic granulomatosis with polyangiitis (EGPA), which can be treated with mepolizumab. This case report presents an atypical form of EGPA, following an unusual course that began with the final signs and symptoms and then proceeded backward to the prodromal stages. Our patient, indeed, a 46-year-old woman, was asymptomatic throughout her youth, with the exception of nasal polyps. Later, at the age of 34, she developed late onset asthma, which became increasingly difficult to treat, until old and previously unacknowledged evidence of vasculitis was discovered, giving a twist to our patient’s medical history and, subsequently, to the therapeutic strategy adopted to treat her. This case report aims to highlight the importance of conducting a thorough anamnesis in patients suffering from both severe asthma and nasal polyposis, taking into account the high prevalence of EGPA in this category of patients, as well as its wide range of clinical manifestations, not to mention the various available therapeutic strategies, including mepolizumab.
DOI: https://doi.org/10.37349/eaa.2025.100975
This article belongs to the special issue The Era of Biologics in Allergy
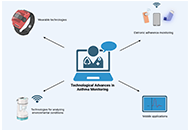
Telemedicine (TM) is rapidly gaining recognition as a valuable tool for accessing medical treatments globally. The article aimed to review the latest literature on the role of TM in asthma care. It has been shown that TM offers numerous advantages for patients and clinicians, facilitating an easier access to healthcare resulting in higher patient satisfaction. Telemedicine technology, pushed by the COVID-19 pandemic, has improved asthma management, notably treatment adherence. Smart inhalers, wearable gadgets, and smartphone apps allow doctors to make data-driven decisions and empower patients to manage their diseases. Real-world research shows that TM is effective and patient-friendly. Infrastructure constraints, data security issues, and long-term patient engagement must be addressed. In conclusion, a hybrid strategy combining TM and in-person visits, enabled by AI and secure digital solutions, can provide equal, efficient, and comprehensive asthma management.
Telemedicine (TM) is rapidly gaining recognition as a valuable tool for accessing medical treatments globally. The article aimed to review the latest literature on the role of TM in asthma care. It has been shown that TM offers numerous advantages for patients and clinicians, facilitating an easier access to healthcare resulting in higher patient satisfaction. Telemedicine technology, pushed by the COVID-19 pandemic, has improved asthma management, notably treatment adherence. Smart inhalers, wearable gadgets, and smartphone apps allow doctors to make data-driven decisions and empower patients to manage their diseases. Real-world research shows that TM is effective and patient-friendly. Infrastructure constraints, data security issues, and long-term patient engagement must be addressed. In conclusion, a hybrid strategy combining TM and in-person visits, enabled by AI and secure digital solutions, can provide equal, efficient, and comprehensive asthma management.
DOI: https://doi.org/10.37349/eaa.2025.100974
This article belongs to the special issue The Global Picture of Asthma after Guideline Changes and the COVID Pandemics
DOI: https://doi.org/10.37349/eaa.2025.100971
