







 Previous
Background:
Ankyloglossia is a congenital condition characterized by restricted tongue mobility, which may influence oral functions such as speech, swallowing, and oral motor coordination. This systematic review aimed to evaluate oral functional outcomes following surgical and/or myofunctional interventions in individuals with lingual hypomobility. A secondary aim was to assess variability and consistency of functional improvements across different therapeutic approaches.
Methods:
This systematic review was conducted in accordance with PRISMA guidelines. PubMed, Scopus, and Web of Science were searched between 15 June 2025 and 10 August 2025. Eligible clinical studies (randomized controlled trials, cohort studies, and case series/reports) evaluated lingual frenotomy, frenulectomy, or frenuloplasty, alone or combined with orofacial myofunctional therapy, and reported oral functional outcomes, including tongue mobility, oral posture, swallowing-related tasks, neuromuscular measures, and patient-reported function. Risk of bias was assessed using validated tools (ROBINS-I and RoB 2). Due to heterogeneity in study design and outcome measures, a narrative synthesis was performed.
Results:
Ten studies involving more than 1,300 participants across pediatric, adolescent, and adult populations were included. The evidence comprised randomized controlled trials, observational studies, and case series. Surgical intervention alone was primarily associated with immediate anatomical and mobility-related improvements. In contrast, combined surgical and myofunctional approaches were more consistently associated with improvements in functional outcomes, including tongue mobility, resting posture, and swallowing-related functions. However, the consistency of these improvements varied across age groups, intervention protocols, and outcome assessment methods. Risk of bias was variable and frequently influenced by heterogeneous diagnostic criteria, nonstandardized interventions, and nonuniform outcome measures.
Discussion:
Combined surgical and myofunctional interventions appear to be associated with improvements in oral functional outcomes compared with stand-alone approaches. However, due to substantial methodological heterogeneity and limited high-quality evidence, these findings should be interpreted with caution and are primarily applicable to the specific functional domains evaluated.
Background:
Ankyloglossia is a congenital condition characterized by restricted tongue mobility, which may influence oral functions such as speech, swallowing, and oral motor coordination. This systematic review aimed to evaluate oral functional outcomes following surgical and/or myofunctional interventions in individuals with lingual hypomobility. A secondary aim was to assess variability and consistency of functional improvements across different therapeutic approaches.
Methods:
This systematic review was conducted in accordance with PRISMA guidelines. PubMed, Scopus, and Web of Science were searched between 15 June 2025 and 10 August 2025. Eligible clinical studies (randomized controlled trials, cohort studies, and case series/reports) evaluated lingual frenotomy, frenulectomy, or frenuloplasty, alone or combined with orofacial myofunctional therapy, and reported oral functional outcomes, including tongue mobility, oral posture, swallowing-related tasks, neuromuscular measures, and patient-reported function. Risk of bias was assessed using validated tools (ROBINS-I and RoB 2). Due to heterogeneity in study design and outcome measures, a narrative synthesis was performed.
Results:
Ten studies involving more than 1,300 participants across pediatric, adolescent, and adult populations were included. The evidence comprised randomized controlled trials, observational studies, and case series. Surgical intervention alone was primarily associated with immediate anatomical and mobility-related improvements. In contrast, combined surgical and myofunctional approaches were more consistently associated with improvements in functional outcomes, including tongue mobility, resting posture, and swallowing-related functions. However, the consistency of these improvements varied across age groups, intervention protocols, and outcome assessment methods. Risk of bias was variable and frequently influenced by heterogeneous diagnostic criteria, nonstandardized interventions, and nonuniform outcome measures.
Discussion:
Combined surgical and myofunctional interventions appear to be associated with improvements in oral functional outcomes compared with stand-alone approaches. However, due to substantial methodological heterogeneity and limited high-quality evidence, these findings should be interpreted with caution and are primarily applicable to the specific functional domains evaluated.
DOI: https://doi.org/10.37349/emed.2026.1001425


Primary sclerosing cholangitis (PSC) is a rare chronic cholangiopathy that is strongly associated with inflammatory bowel disease, particularly ulcerative colitis. It is characterized by multifocal biliary strictures, typically producing the classic “beads-on-a-string” appearance on magnetic resonance cholangiopancreatography, and by the histological finding of periductal concentric fibrosis (“onion-skin” fibrosis). Its pathogenesis is multifactorial and involves genetic susceptibility, immune dysregulation, environmental influences, and perturbations of the gut-liver axis. In this context, toxic bile acids and other luminal mediators originating from inflamed bowel mucosa may contribute to cholangiocyte injury. Phosphatidylcholine (PC) plays a central role in membrane integrity, cellular signaling, and inflammatory regulation, and its deficiency may predispose to hepatobiliary damage. Kindlin proteins are key modulators of integrin-mediated functions; notably, kindlin-2 contributes to the stabilization of intercellular junctions, and its loss impairs smooth muscle and intestinal development. Mice with biliary-specific deletion of kindlin-2 develop onion-skin fibrosis in the absence of overt cholestatic abnormalities, thereby supporting the concept of a gut-liver pathogenic axis. Nevertheless, further investigation is required to determine the extent to which this model reproduces human PSC, particularly regarding PC availability and cholangiocyte junctional integrity. Disruption of tight junctions may reduce PC delivery to the biliary mucosa, thereby promoting hepatic injury. Although these findings support the rationale for exploring PC supplementation as a potential therapeutic strategy in PSC, additional studies are required before translation to clinical trials can be justified.
Primary sclerosing cholangitis (PSC) is a rare chronic cholangiopathy that is strongly associated with inflammatory bowel disease, particularly ulcerative colitis. It is characterized by multifocal biliary strictures, typically producing the classic “beads-on-a-string” appearance on magnetic resonance cholangiopancreatography, and by the histological finding of periductal concentric fibrosis (“onion-skin” fibrosis). Its pathogenesis is multifactorial and involves genetic susceptibility, immune dysregulation, environmental influences, and perturbations of the gut-liver axis. In this context, toxic bile acids and other luminal mediators originating from inflamed bowel mucosa may contribute to cholangiocyte injury. Phosphatidylcholine (PC) plays a central role in membrane integrity, cellular signaling, and inflammatory regulation, and its deficiency may predispose to hepatobiliary damage. Kindlin proteins are key modulators of integrin-mediated functions; notably, kindlin-2 contributes to the stabilization of intercellular junctions, and its loss impairs smooth muscle and intestinal development. Mice with biliary-specific deletion of kindlin-2 develop onion-skin fibrosis in the absence of overt cholestatic abnormalities, thereby supporting the concept of a gut-liver pathogenic axis. Nevertheless, further investigation is required to determine the extent to which this model reproduces human PSC, particularly regarding PC availability and cholangiocyte junctional integrity. Disruption of tight junctions may reduce PC delivery to the biliary mucosa, thereby promoting hepatic injury. Although these findings support the rationale for exploring PC supplementation as a potential therapeutic strategy in PSC, additional studies are required before translation to clinical trials can be justified.
DOI: https://doi.org/10.37349/edd.2026.1005133
Aim:
This work focused on numerical modeling of thermal inactivation parameters of Escherichia coli O157:H7 in pretreated watermelon fruit juice as influenced by processing conditions. The work aimed to enhance microbiological safety and information of the product.
Methods:
Mature and fresh watermelon fruits were sourced, graded, and processed into juice under hygienic conditions. The extracted juice was pasteurized and allowed to cool. Prior to thermal treatments, the juice was sterilized, cooled, and inoculated with Escherichia coli O157:H7. The inoculated samples were then subjected to different treatments. The effect of pH (4.5, 5.5, and 6.5) and temperature (70℃, 80℃, and 90℃) on thermobacteriological properties was investigated. Meanwhile, Design Expert 13 for Windows was used for experimental layout for interactive impact of pH and inactivation temperatures. All experiments were conducted in triplicate. Thermal inactivation curves of Escherichia coli O157:H7 in the juice samples were obtained by plotting the number of survivors (CFU/mL) against time, and the corresponding D-value was obtained. Other thermobacteriology parameters were subsequently calculated using appropriate equations. The data obtained were fitted into a model using Design Expert 13 for Windows.
Results:
Thermal inactivation data obtained showed that the thermal inactivation curve of Escherichia coli O157:H7 in pretreated watermelon juice had a linear interactive effect as temperature and pH varied. As temperature (70–90°C) and pH (4.5–6.5) varied, thermobacteriology parameters such as D-value, F-value, z-value and activation energy ranged from 11.8–23.4 min, 23.6–46.8 min, 8–9.6°C, 32.49–42.03 kJ/mol, respectively. The results showed that Escherichia coli O157:H7 in pretreated watermelon juice demonstrated significant inactivation at a higher temperature of 90℃ and a lower pH of 4.5.
Conclusions:
This study provided valuable data that could be employed as a guide for the potential food industry, scientists, and engineers in order to improve the consumption safety of the product.
Aim:
This work focused on numerical modeling of thermal inactivation parameters of Escherichia coli O157:H7 in pretreated watermelon fruit juice as influenced by processing conditions. The work aimed to enhance microbiological safety and information of the product.
Methods:
Mature and fresh watermelon fruits were sourced, graded, and processed into juice under hygienic conditions. The extracted juice was pasteurized and allowed to cool. Prior to thermal treatments, the juice was sterilized, cooled, and inoculated with Escherichia coli O157:H7. The inoculated samples were then subjected to different treatments. The effect of pH (4.5, 5.5, and 6.5) and temperature (70℃, 80℃, and 90℃) on thermobacteriological properties was investigated. Meanwhile, Design Expert 13 for Windows was used for experimental layout for interactive impact of pH and inactivation temperatures. All experiments were conducted in triplicate. Thermal inactivation curves of Escherichia coli O157:H7 in the juice samples were obtained by plotting the number of survivors (CFU/mL) against time, and the corresponding D-value was obtained. Other thermobacteriology parameters were subsequently calculated using appropriate equations. The data obtained were fitted into a model using Design Expert 13 for Windows.
Results:
Thermal inactivation data obtained showed that the thermal inactivation curve of Escherichia coli O157:H7 in pretreated watermelon juice had a linear interactive effect as temperature and pH varied. As temperature (70–90°C) and pH (4.5–6.5) varied, thermobacteriology parameters such as D-value, F-value, z-value and activation energy ranged from 11.8–23.4 min, 23.6–46.8 min, 8–9.6°C, 32.49–42.03 kJ/mol, respectively. The results showed that Escherichia coli O157:H7 in pretreated watermelon juice demonstrated significant inactivation at a higher temperature of 90℃ and a lower pH of 4.5.
Conclusions:
This study provided valuable data that could be employed as a guide for the potential food industry, scientists, and engineers in order to improve the consumption safety of the product.
DOI: https://doi.org/10.37349/eff.2026.1010185
Exercise-associated muscle cramps (EAMC) remain a significant clinical challenge in elite athletics, often attributed to either electrolyte depletion or altered neuromuscular control. While traditional management focuses on stretching and rehydration, these methods may be insufficient for rapid return to play (RTP) in high-stakes settings with minimal downtime before the next competition. This case report explores the acute application of dry needling (DN) to resolve recurrent EAMC in a 23-year-old National Collegiate Athletic Association (NCAA) Division I basketball athlete. The athlete presented with a severe, involuntary spasm of the right adductor magnus (AM) following a single-leg landing. Initial sideline manual therapy and rehydration provided only transient relief; upon RTP, the athlete sustained a recurrence described as a tenfold increase in intensity, necessitating removal from competition. Within 5 hours of injury, trigger point dry needling (TrP-DN) was administered to the ischiocondylar portion of the AM to facilitate a neuromuscular reset. The intervention resulted in immediate resolution of symptoms and a rapid return to prior performance. The athlete successfully returned to competition the following day, participating in two subsequent games within 48 hours without recurrence or performance deficits. This case demonstrates that DN can serve as a safe and highly effective intervention for the acute management of EAMC, in conjunction with traditional interventions. These findings suggest that directly targeting the motor endplate via DN may more effectively downregulate the neuromuscular hyperexcitability compared to traditional manual stretching and rehydration alone.
Exercise-associated muscle cramps (EAMC) remain a significant clinical challenge in elite athletics, often attributed to either electrolyte depletion or altered neuromuscular control. While traditional management focuses on stretching and rehydration, these methods may be insufficient for rapid return to play (RTP) in high-stakes settings with minimal downtime before the next competition. This case report explores the acute application of dry needling (DN) to resolve recurrent EAMC in a 23-year-old National Collegiate Athletic Association (NCAA) Division I basketball athlete. The athlete presented with a severe, involuntary spasm of the right adductor magnus (AM) following a single-leg landing. Initial sideline manual therapy and rehydration provided only transient relief; upon RTP, the athlete sustained a recurrence described as a tenfold increase in intensity, necessitating removal from competition. Within 5 hours of injury, trigger point dry needling (TrP-DN) was administered to the ischiocondylar portion of the AM to facilitate a neuromuscular reset. The intervention resulted in immediate resolution of symptoms and a rapid return to prior performance. The athlete successfully returned to competition the following day, participating in two subsequent games within 48 hours without recurrence or performance deficits. This case demonstrates that DN can serve as a safe and highly effective intervention for the acute management of EAMC, in conjunction with traditional interventions. These findings suggest that directly targeting the motor endplate via DN may more effectively downregulate the neuromuscular hyperexcitability compared to traditional manual stretching and rehydration alone.
DOI: https://doi.org/10.37349/emd.2026.1007134
Aim:
This study investigated the habitual intake of ultra-processed foods (UPFs) and their association with blood pressure, anthropometric measures, and metabolic health risks among Filipinos aged 16–30 years residing in an urban area.
Methods:
A cross-sectional analytical study was conducted among 360 Filipinos aged 16–30 years residing in Intramuros, Manila. The study assessed UPF intake, systolic and diastolic blood pressure, and anthropometric measures, including body mass index (BMI), body fat percentage, waist-to-height ratio (WHtR), waist-to-hip ratio (WHR), and A Body Shape Index (ABSI). Unadjusted binary logistic regression was used to examine the odds of high UPF intake according to anthropometric and clinical categories. UPF intake status was specified as the dependent variable, with low-moderate intake as the reference category.
Results:
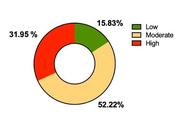
More than half (52.22%) of the Filipino youth had moderate UPF intake. In the unadjusted logistic regression analyses, adults classified as obese according to BMI had higher odds of high UPF intake than adults with normal BMI [odds ratio (OR) = 2.65, 95% confidence interval (CI): 1.13–6.20]. Participants classified as obese according to body fat percentage also had higher odds of high UPF intake than those with normal body fat percentage (OR = 2.45, 95% CI: 1.40–4.29), while participants with high ABSI had higher odds of high UPF intake than those with normal ABSI (OR = 1.65, 95% CI: 1.05–2.59). No significant associations were observed for blood pressure, adolescent BMI, or WHtR/WHR.
Conclusions:
High UPF intake was cross-sectionally associated with selected adiposity-related characteristics. Because the logistic regression models were unadjusted and the study was cross-sectional, the findings do not establish the direction, independence, or causality of these relationships.
Aim:
This study investigated the habitual intake of ultra-processed foods (UPFs) and their association with blood pressure, anthropometric measures, and metabolic health risks among Filipinos aged 16–30 years residing in an urban area.
Methods:
A cross-sectional analytical study was conducted among 360 Filipinos aged 16–30 years residing in Intramuros, Manila. The study assessed UPF intake, systolic and diastolic blood pressure, and anthropometric measures, including body mass index (BMI), body fat percentage, waist-to-height ratio (WHtR), waist-to-hip ratio (WHR), and A Body Shape Index (ABSI). Unadjusted binary logistic regression was used to examine the odds of high UPF intake according to anthropometric and clinical categories. UPF intake status was specified as the dependent variable, with low-moderate intake as the reference category.
Results:
More than half (52.22%) of the Filipino youth had moderate UPF intake. In the unadjusted logistic regression analyses, adults classified as obese according to BMI had higher odds of high UPF intake than adults with normal BMI [odds ratio (OR) = 2.65, 95% confidence interval (CI): 1.13–6.20]. Participants classified as obese according to body fat percentage also had higher odds of high UPF intake than those with normal body fat percentage (OR = 2.45, 95% CI: 1.40–4.29), while participants with high ABSI had higher odds of high UPF intake than those with normal ABSI (OR = 1.65, 95% CI: 1.05–2.59). No significant associations were observed for blood pressure, adolescent BMI, or WHtR/WHR.
Conclusions:
High UPF intake was cross-sectionally associated with selected adiposity-related characteristics. Because the logistic regression models were unadjusted and the study was cross-sectional, the findings do not establish the direction, independence, or causality of these relationships.
DOI: https://doi.org/10.37349/eff.2026.1010184
This article belongs to the special issue Nutrition in Health and Disease
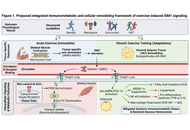
Obesity is a major global health challenge, now recognized as a complex metabolic and inflammatory disorder characterized by excess adiposity and chronic low-grade inflammation. Adipose tissue functions as an endocrine organ, secreting adipokines that regulate metabolism and immune responses. Among these, Isthmin-1 (ISM1) has recently emerged as a novel adipokine with important metabolic and anti-inflammatory roles. ISM1 is widely expressed in adult tissues and is associated with central adiposity and metabolic dysfunction. It enhances glucose uptake via an insulin-independent PI3K/Akt pathway through integrin αVβ5 activation, promoting GLUT4 translocation. ISM1 also regulates lipid metabolism by inhibiting lipogenesis and stimulating fatty acid oxidation. Additionally, it exerts anti-inflammatory effects by suppressing NF-κB signaling and promoting macrophage polarization toward an anti-inflammatory phenotype. Exercise is known to improve adipokine profiles, insulin sensitivity, and inflammation, but its effects on ISM1 remain unexplored. This represents a critical gap in the literature. Understanding how different exercise modalities influence ISM1 could reveal new mechanisms underlying exercise benefits and support its potential as a biomarker or therapeutic target in obesity and metabolic disorders.
Obesity is a major global health challenge, now recognized as a complex metabolic and inflammatory disorder characterized by excess adiposity and chronic low-grade inflammation. Adipose tissue functions as an endocrine organ, secreting adipokines that regulate metabolism and immune responses. Among these, Isthmin-1 (ISM1) has recently emerged as a novel adipokine with important metabolic and anti-inflammatory roles. ISM1 is widely expressed in adult tissues and is associated with central adiposity and metabolic dysfunction. It enhances glucose uptake via an insulin-independent PI3K/Akt pathway through integrin αVβ5 activation, promoting GLUT4 translocation. ISM1 also regulates lipid metabolism by inhibiting lipogenesis and stimulating fatty acid oxidation. Additionally, it exerts anti-inflammatory effects by suppressing NF-κB signaling and promoting macrophage polarization toward an anti-inflammatory phenotype. Exercise is known to improve adipokine profiles, insulin sensitivity, and inflammation, but its effects on ISM1 remain unexplored. This represents a critical gap in the literature. Understanding how different exercise modalities influence ISM1 could reveal new mechanisms underlying exercise benefits and support its potential as a biomarker or therapeutic target in obesity and metabolic disorders.
DOI: https://doi.org/10.37349/ei.2026.1003263
This article belongs to the special issue Physical Activity and Immune System in Chronic Diseases: Mechanisms and Insights
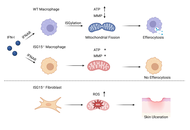
A functional immune system is a key antagonist of cancer cell growth. Cytokines such as interferons (IFNs) promote the onset of inflammation, turn cells into an anti-viral state, and shape the dynamic tumor-immune cell interactome. Recent work illustrates how type I IFNs contribute to the resolution of inflammatory conditions. This involves macrophage-mediated efferocytosis for the clearance of apoptotic cells and the intrinsic capacity of type I IFNs to restrict their own autocrine signaling loops via the IFN-stimulated gene 15 (ISG15) protein. We discuss how this may affect tumor cells and how acetylation-dependent processes can affect the phosphorylation-dependent signaling cascades that augment IFN-dependent gene expression.
A functional immune system is a key antagonist of cancer cell growth. Cytokines such as interferons (IFNs) promote the onset of inflammation, turn cells into an anti-viral state, and shape the dynamic tumor-immune cell interactome. Recent work illustrates how type I IFNs contribute to the resolution of inflammatory conditions. This involves macrophage-mediated efferocytosis for the clearance of apoptotic cells and the intrinsic capacity of type I IFNs to restrict their own autocrine signaling loops via the IFN-stimulated gene 15 (ISG15) protein. We discuss how this may affect tumor cells and how acetylation-dependent processes can affect the phosphorylation-dependent signaling cascades that augment IFN-dependent gene expression.
DOI: https://doi.org/10.37349/etat.2026.1002399
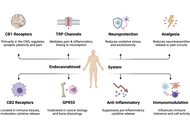
Cannabis sativa has a long history in ethnomedicine, but advances in molecular biology and regulatory shifts have reignited global interest in its therapeutic potential. Cannabinoid research in the 21st century spans molecular pharmacology, clinical applications, and public health integration. This study provides a comprehensive synthesis of the current state of knowledge. This narrative review synthesizes evidence from Scopus, PubMed, and Google Scholar using Medical Subject Headings-based search strategies. Only articles published in English were included, without restrictions on publication year; however, greater emphasis was placed on recent studies to ensure currency, while seminal and historically important publications were included where necessary to provide foundational context. Relevant studies were thematically analyzed and summarized under predefined headings. Major phytocannabinoids have been identified, with Δ9-tetrahydrocannabinol, cannabidiol, and cannabigerol as key therapeutic candidates. Preclinical studies have shown neuroprotective, anti-inflammatory, analgesic, immunomodulatory, and anticancer effects, but clinical translation remains limited by variability, dosing challenges, and inconsistent reproducibility. These effects are mediated through the endocannabinoid system and related receptor networks. Emerging evidence suggests that epigenetic regulation and precision medicine approaches may enhance individualized cannabinoid therapy. However, safety concerns, including cognitive and psychiatric effects, drug interactions, and dependence, require robust pharmacovigilance. Fragmented regulatory frameworks continue to hinder research and equitable access, underscoring the need for standardized formulations, clinician training, and equity-focused integration into health systems. Cannabinoid therapeutics represent a rapidly evolving field with promise in multiple medical domains. Future progress hinges on harmonizing regulations, expanding clinical evidence, and integrating precision medicine, equity, and public health principles to maximize therapeutic benefits while minimizing risks.
Cannabis sativa has a long history in ethnomedicine, but advances in molecular biology and regulatory shifts have reignited global interest in its therapeutic potential. Cannabinoid research in the 21st century spans molecular pharmacology, clinical applications, and public health integration. This study provides a comprehensive synthesis of the current state of knowledge. This narrative review synthesizes evidence from Scopus, PubMed, and Google Scholar using Medical Subject Headings-based search strategies. Only articles published in English were included, without restrictions on publication year; however, greater emphasis was placed on recent studies to ensure currency, while seminal and historically important publications were included where necessary to provide foundational context. Relevant studies were thematically analyzed and summarized under predefined headings. Major phytocannabinoids have been identified, with Δ9-tetrahydrocannabinol, cannabidiol, and cannabigerol as key therapeutic candidates. Preclinical studies have shown neuroprotective, anti-inflammatory, analgesic, immunomodulatory, and anticancer effects, but clinical translation remains limited by variability, dosing challenges, and inconsistent reproducibility. These effects are mediated through the endocannabinoid system and related receptor networks. Emerging evidence suggests that epigenetic regulation and precision medicine approaches may enhance individualized cannabinoid therapy. However, safety concerns, including cognitive and psychiatric effects, drug interactions, and dependence, require robust pharmacovigilance. Fragmented regulatory frameworks continue to hinder research and equitable access, underscoring the need for standardized formulations, clinician training, and equity-focused integration into health systems. Cannabinoid therapeutics represent a rapidly evolving field with promise in multiple medical domains. Future progress hinges on harmonizing regulations, expanding clinical evidence, and integrating precision medicine, equity, and public health principles to maximize therapeutic benefits while minimizing risks.
DOI: https://doi.org/10.37349/eds.2026.1008177
Gastric cancer is one of the most prevalent malignancies of the gastrointestinal tract. Worldwide, it ranks as the fourth most commonly diagnosed cancer and the third leading cause of cancer-related mortality. A variety of diagnostic approaches are used for the detection of gastric cancer. Early diagnosis of gastric cancer is crucial, as timely treatment can significantly improve patient prognosis. Detection and monitoring of circulating tumor DNA (ctDNA) provide valuable clinical information while minimizing the need for invasive procedures, such as tissue biopsy. These ctDNAs have been identified as reliable and accurate biomarkers for gastric cancer. The application of ctDNA in gastric cancer plays a significant role in the early diagnosis, detection, and monitoring of minimal residual disease, as well as in the clinical management of advanced-stage disease.
Gastric cancer is one of the most prevalent malignancies of the gastrointestinal tract. Worldwide, it ranks as the fourth most commonly diagnosed cancer and the third leading cause of cancer-related mortality. A variety of diagnostic approaches are used for the detection of gastric cancer. Early diagnosis of gastric cancer is crucial, as timely treatment can significantly improve patient prognosis. Detection and monitoring of circulating tumor DNA (ctDNA) provide valuable clinical information while minimizing the need for invasive procedures, such as tissue biopsy. These ctDNAs have been identified as reliable and accurate biomarkers for gastric cancer. The application of ctDNA in gastric cancer plays a significant role in the early diagnosis, detection, and monitoring of minimal residual disease, as well as in the clinical management of advanced-stage disease.
DOI: https://doi.org/10.37349/edd.2026.1005132
Pomegranate has long been used in Greco-Arab medicine for gastrointestinal, cardiovascular, metabolic, and inflammatory disorders. It has been described to relieve nausea, vomiting, abdominal pain, diarrhoea, palpitations, etc. Modern scientific studies have validated these uses, attributing them to a rich phytochemical profile of polyphenols, flavonoids, anthocyanins, tannins, punicalagins, and ellagitannins. However, the precise mechanism of action and optimal application strategies for pomegranate in systemic diseases remain an area of investigation. Metabolomics provides a robust platform for elucidating the intricate relationships between pomegranate bioactives and human physiology. Therefore, to evaluate the therapeutic potential of pomegranate (Punica granatum L.) and find out how metabolomics can enhance its pharmacological applications, a literature review was conducted using ancient & modern pharmacology books, PubMed, Scopus, Web of Science, and Google Scholar. Human clinical trials were prioritized, followed by in vivo and in vitro studies. Evidence was synthesized qualitatively with emphasis on metabolomic findings. The research question was framed to determine whether metabolomics can enhance and optimize the therapeutic potential of pomegranate. Metabolomic studies demonstrated that pomegranate exhibits all its biological activities through gut microbiota-derived metabolites, particularly urolithins, which play a key role in mediating these effects. Therefore, it was concluded that integration of metabolomics with traditional pharmacology can enhance pomegranate-based therapeutics and support its role in precision nutrition.
Pomegranate has long been used in Greco-Arab medicine for gastrointestinal, cardiovascular, metabolic, and inflammatory disorders. It has been described to relieve nausea, vomiting, abdominal pain, diarrhoea, palpitations, etc. Modern scientific studies have validated these uses, attributing them to a rich phytochemical profile of polyphenols, flavonoids, anthocyanins, tannins, punicalagins, and ellagitannins. However, the precise mechanism of action and optimal application strategies for pomegranate in systemic diseases remain an area of investigation. Metabolomics provides a robust platform for elucidating the intricate relationships between pomegranate bioactives and human physiology. Therefore, to evaluate the therapeutic potential of pomegranate (Punica granatum L.) and find out how metabolomics can enhance its pharmacological applications, a literature review was conducted using ancient & modern pharmacology books, PubMed, Scopus, Web of Science, and Google Scholar. Human clinical trials were prioritized, followed by in vivo and in vitro studies. Evidence was synthesized qualitatively with emphasis on metabolomic findings. The research question was framed to determine whether metabolomics can enhance and optimize the therapeutic potential of pomegranate. Metabolomic studies demonstrated that pomegranate exhibits all its biological activities through gut microbiota-derived metabolites, particularly urolithins, which play a key role in mediating these effects. Therefore, it was concluded that integration of metabolomics with traditional pharmacology can enhance pomegranate-based therapeutics and support its role in precision nutrition.
DOI: https://doi.org/10.37349/eff.2026.1010183
This article belongs to the special issue Food-Derived Bioactive Compounds: From Foodomics to Therapeutic Applications
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS)/toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP), are T-cell-mediated hypersensitivity reactions. Although their causative agents and acute manifestations are well characterized, limited data exist regarding their long-term sequelae, particularly the subsequent development of autoimmune disease. A comprehensive literature review was conducted using PubMed. Given the limited published evidence regarding autoimmune sequelae following SCARs, the search strategy was intentionally broad and included studies published from the 1980s through 2025. Among SCARs, DRESS demonstrated the strongest association with autoimmune disease, including type 1 diabetes mellitus, thyroiditis, bullous pemphigoid, thrombotic thrombocytopenic purpura, autoimmune hemolytic anemia, vitiligo, and systemic lupus erythematosus. Proposed pathogenic mechanisms include viral reactivation and persistent immune dysregulation. SJS/TEN has also been associated with fulminant type 1 diabetes mellitus, autoimmune thyroid disease, systemic lupus erythematosus, Sjögren’s syndrome, and the development of positive antinuclear antibodies. In contrast, evidence linking AGEP to autoimmune disease remains limited and conflicting, although associations with CARD14 mutations and polyarteritis nodosa have been reported. Evidence supporting post-SCAR autoimmunity, particularly following DRESS, is growing but remains largely based on case reports and small observational studies. SCARs, particularly DRESS and to a lesser extent SJS/TEN, may predispose patients to autoimmune disease through persistent immune dysregulation and viral reactivation. In contrast, no clear association has been established between AGEP and autoimmune disease. Clinicians should remain vigilant for potential long-term autoimmune sequelae following SCARs and consider multidisciplinary follow-up when clinically appropriate. Further prospective studies are needed to better characterize the underlying mechanisms, incidence, and optimal long-term surveillance strategies associated with these conditions.
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS)/toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP), are T-cell-mediated hypersensitivity reactions. Although their causative agents and acute manifestations are well characterized, limited data exist regarding their long-term sequelae, particularly the subsequent development of autoimmune disease. A comprehensive literature review was conducted using PubMed. Given the limited published evidence regarding autoimmune sequelae following SCARs, the search strategy was intentionally broad and included studies published from the 1980s through 2025. Among SCARs, DRESS demonstrated the strongest association with autoimmune disease, including type 1 diabetes mellitus, thyroiditis, bullous pemphigoid, thrombotic thrombocytopenic purpura, autoimmune hemolytic anemia, vitiligo, and systemic lupus erythematosus. Proposed pathogenic mechanisms include viral reactivation and persistent immune dysregulation. SJS/TEN has also been associated with fulminant type 1 diabetes mellitus, autoimmune thyroid disease, systemic lupus erythematosus, Sjögren’s syndrome, and the development of positive antinuclear antibodies. In contrast, evidence linking AGEP to autoimmune disease remains limited and conflicting, although associations with CARD14 mutations and polyarteritis nodosa have been reported. Evidence supporting post-SCAR autoimmunity, particularly following DRESS, is growing but remains largely based on case reports and small observational studies. SCARs, particularly DRESS and to a lesser extent SJS/TEN, may predispose patients to autoimmune disease through persistent immune dysregulation and viral reactivation. In contrast, no clear association has been established between AGEP and autoimmune disease. Clinicians should remain vigilant for potential long-term autoimmune sequelae following SCARs and consider multidisciplinary follow-up when clinically appropriate. Further prospective studies are needed to better characterize the underlying mechanisms, incidence, and optimal long-term surveillance strategies associated with these conditions.
DOI: https://doi.org/10.37349/eaa.2026.1009131
Bacterial co-infection in patients with coronavirus disease 2019 (COVID-19) can complicate diagnosis because of overlapping clinicoradiologic findings among pathogens. We report a case of suspected triple co-infection with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), Legionella pneumophila (L. pneumophila), and Streptococcus pneumoniae (S. pneumoniae) after hot-spring travel in a post-splenectomy patient. A man in his 70s with a history of subtotal esophagectomy and concomitant splenectomy for esophageal cancer was admitted with fever, worsening productive cough, and altered sensorium. He had recently traveled to a hot spring with a group that included his wife, who also developed a fever and was diagnosed with COVID-19. On admission, results of urinary antigen tests for L. pneumophila and S. pneumoniae were positive, a SARS-CoV-2 nucleic acid amplification test was positive, and sputum culture yielded S. pneumoniae. Chest computed tomography revealed multifocal bilateral ground-glass opacities, small bilateral pleural effusions, and relatively well-defined right middle-lobe consolidation with air bronchograms in a peribronchovascular distribution. These microbiological and radiological findings supported a suspected triple co-infection rather than COVID-19 alone. Treatment with remdesivir, ceftriaxone, and levofloxacin was initiated, and the patient’s condition improved, with better oxygenation and decreased inflammatory markers. Remdesivir and ceftriaxone were discontinued after 5 days, whereas levofloxacin was continued for 14 days. Follow-up imaging revealed marked improvement, and the patient was discharged. Public health investigations did not detect Legionella at the hot-spring facility or identify any additional linked cases. This case highlights the importance of prompt pathogen-directed evaluation when COVID-19 pneumonia is accompanied by a relevant exposure history, host risk factors, and atypical imaging findings.
Bacterial co-infection in patients with coronavirus disease 2019 (COVID-19) can complicate diagnosis because of overlapping clinicoradiologic findings among pathogens. We report a case of suspected triple co-infection with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), Legionella pneumophila (L. pneumophila), and Streptococcus pneumoniae (S. pneumoniae) after hot-spring travel in a post-splenectomy patient. A man in his 70s with a history of subtotal esophagectomy and concomitant splenectomy for esophageal cancer was admitted with fever, worsening productive cough, and altered sensorium. He had recently traveled to a hot spring with a group that included his wife, who also developed a fever and was diagnosed with COVID-19. On admission, results of urinary antigen tests for L. pneumophila and S. pneumoniae were positive, a SARS-CoV-2 nucleic acid amplification test was positive, and sputum culture yielded S. pneumoniae. Chest computed tomography revealed multifocal bilateral ground-glass opacities, small bilateral pleural effusions, and relatively well-defined right middle-lobe consolidation with air bronchograms in a peribronchovascular distribution. These microbiological and radiological findings supported a suspected triple co-infection rather than COVID-19 alone. Treatment with remdesivir, ceftriaxone, and levofloxacin was initiated, and the patient’s condition improved, with better oxygenation and decreased inflammatory markers. Remdesivir and ceftriaxone were discontinued after 5 days, whereas levofloxacin was continued for 14 days. Follow-up imaging revealed marked improvement, and the patient was discharged. Public health investigations did not detect Legionella at the hot-spring facility or identify any additional linked cases. This case highlights the importance of prompt pathogen-directed evaluation when COVID-19 pneumonia is accompanied by a relevant exposure history, host risk factors, and atypical imaging findings.
DOI: https://doi.org/10.37349/emed.2026.1001424
This article belongs to the special issue Legionellosis: From Environmental Exposure to Clinical Disease
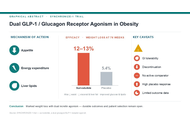
The therapeutic landscape for obesity is changing rapidly, driven by the recognition of obesity as a chronic, biologically heterogeneous disease, with clinically relevant organ consequences. In this context, the phase 3 SYNCHRONIZE™-1 trial of survodutide, a once-weekly dual agonist of glucagon receptor and glucagon-like peptide 1 (GLP-1) receptor, is notable not simply because it adds another effective incretin-based therapy, but because it tests a broader metabolic concept. By pairing GLP-1-mediated appetite suppression with glucagon-mediated effects on energy expenditure and hepatic lipid handling, survodutide aims to extend treatment beyond appetite control towards coordinated modulation of adiposity, cardiometabolic risk and steatotic liver disease. In adults with obesity without diabetes, SYNCHRONIZE™-1 showed sustained body-weight reductions of approximately 12–13% over 76 weeks, compared with 5.4% with placebo, and increased the proportion of participants achieving clinically ambitious weight-loss thresholds, including at least 20% weight loss. Improvements in waist circumference, glycemic and lipid measures, together with reductions in visceral and liver fat content (LFC) in imaging analyses, support the possibility of benefits that are metabolically broader than scale weight alone. Yet the trial also illustrates familiar tensions in obesity pharmacotherapy: gastrointestinal tolerability, treatment discontinuation, the absence of an active comparator, unexpectedly high placebo-associated weight loss and limited outcome data. Thus, SYNCHRONIZE™-1 should be read as an important proof of principle for dual glucagon-GLP-1 receptor agonism rather than as a definitive positioning of the therapy within the treatment landscape. The next challenge is to determine whether this mechanism delivers durable cardiovascular, renal, and hepatic benefits, and in which patient populations.
The therapeutic landscape for obesity is changing rapidly, driven by the recognition of obesity as a chronic, biologically heterogeneous disease, with clinically relevant organ consequences. In this context, the phase 3 SYNCHRONIZE™-1 trial of survodutide, a once-weekly dual agonist of glucagon receptor and glucagon-like peptide 1 (GLP-1) receptor, is notable not simply because it adds another effective incretin-based therapy, but because it tests a broader metabolic concept. By pairing GLP-1-mediated appetite suppression with glucagon-mediated effects on energy expenditure and hepatic lipid handling, survodutide aims to extend treatment beyond appetite control towards coordinated modulation of adiposity, cardiometabolic risk and steatotic liver disease. In adults with obesity without diabetes, SYNCHRONIZE™-1 showed sustained body-weight reductions of approximately 12–13% over 76 weeks, compared with 5.4% with placebo, and increased the proportion of participants achieving clinically ambitious weight-loss thresholds, including at least 20% weight loss. Improvements in waist circumference, glycemic and lipid measures, together with reductions in visceral and liver fat content (LFC) in imaging analyses, support the possibility of benefits that are metabolically broader than scale weight alone. Yet the trial also illustrates familiar tensions in obesity pharmacotherapy: gastrointestinal tolerability, treatment discontinuation, the absence of an active comparator, unexpectedly high placebo-associated weight loss and limited outcome data. Thus, SYNCHRONIZE™-1 should be read as an important proof of principle for dual glucagon-GLP-1 receptor agonism rather than as a definitive positioning of the therapy within the treatment landscape. The next challenge is to determine whether this mechanism delivers durable cardiovascular, renal, and hepatic benefits, and in which patient populations.
DOI: https://doi.org/10.37349/eds.2026.1008175
Cancer treatment faces severe challenges such as drug resistance, side effects, and high costs. The “repurposing old drugs” strategy, which involves repositioning approved drugs for non-oncology indications for cancer treatment, has opened up new avenues for developing efficient, low-toxicity, and rapidly translatable combination therapies. This strategy can not only accelerate clinical translation by leveraging known pharmacological and safety data but also generate synergistic effects with standard chemotherapy, targeted therapy, or immunotherapy by targeting non-classical pathways such as the tumor microenvironment, metabolic reprogramming, and epigenetic regulation. This paper aims to systematically review the repositioning strategies of non-oncology drugs in cancer combination therapies, focusing on their mechanisms of action, synergistic principles, high-throughput screening and computational prediction methods, as well as pre-clinical and clinical research progress based on models such as patient-derived organoids. The paper systematically analyzes the synergistic effects and potential of representative drugs such as metformin, statins, antimalarials, antipsychotics, non-steroidal anti-inflammatory drugs, β-blockers, antihistamines, and cardiovascular drugs. It also summarizes the current challenges in drug screening, mechanism validation, commercial incentives, clinical trial design, and safety re-evaluation, aiming to provide a theoretical basis and future research directions for optimizing cancer combination treatment strategies.
Cancer treatment faces severe challenges such as drug resistance, side effects, and high costs. The “repurposing old drugs” strategy, which involves repositioning approved drugs for non-oncology indications for cancer treatment, has opened up new avenues for developing efficient, low-toxicity, and rapidly translatable combination therapies. This strategy can not only accelerate clinical translation by leveraging known pharmacological and safety data but also generate synergistic effects with standard chemotherapy, targeted therapy, or immunotherapy by targeting non-classical pathways such as the tumor microenvironment, metabolic reprogramming, and epigenetic regulation. This paper aims to systematically review the repositioning strategies of non-oncology drugs in cancer combination therapies, focusing on their mechanisms of action, synergistic principles, high-throughput screening and computational prediction methods, as well as pre-clinical and clinical research progress based on models such as patient-derived organoids. The paper systematically analyzes the synergistic effects and potential of representative drugs such as metformin, statins, antimalarials, antipsychotics, non-steroidal anti-inflammatory drugs, β-blockers, antihistamines, and cardiovascular drugs. It also summarizes the current challenges in drug screening, mechanism validation, commercial incentives, clinical trial design, and safety re-evaluation, aiming to provide a theoretical basis and future research directions for optimizing cancer combination treatment strategies.
DOI: https://doi.org/10.37349/eds.2026.1008176
This article belongs to the special issue Drug Repurposing: Accelerating Cancer Therapeutic Discoveries
Breast cancer management increasingly hinges on decisions made in “grey zones” where tissue sampling is scarce, and tumour biology evolves under therapeutic pressure. This narrative review synthesises evidence on how whole-body imaging biomarkers and circulating tumour DNA (ctDNA) can support response-adaptive pathways at the interface of surgical and systemic care. Four clinically actionable domains are discussed. (a) 16α-[18F]fluoro-17β-estradiol ([18F]FES) positron emission tomography/computed tomography (PET/CT) enables non-invasive, whole-body mapping of functional oestrogen receptor (ER) expression to address receptor discordance, heterogeneous metastases, and selection of endocrine-based strategies. (b) Human epidermal growth factor receptor 2 (HER2)-targeted PET (notably 89Zr-trastuzumab, with emerging alternatives) provides whole-body receptor assessment to uncover actionable HER2-positive disease despite HER2-negative primaries, informing anti-HER2 treatment selection when repeat biopsy is infeasible. (c) In triple-negative breast cancer treated with immune checkpoint inhibitors, 18F-fluorodeoxyglucose (18F-FDG) PET/CT offers quantitative response and whole-body burden assessment but requires immunotherapy-aware interpretation (e.g., confirmation strategies for apparent early progression) to mitigate pseudoprogression and dissociated responses, while simultaneously visualising immune-related adverse events. (d) Pairing early metabolic change on FDG PET/CT with ctDNA kinetics is presented as a biologically complementary approach for response monitoring and risk stratification, with potential to inform trial-embedded response-adaptive hypotheses, with ctDNA offering a rapid systemic trajectory and PET providing lesion-level localisation in heterogeneous or oligoprogressive disease. Overall, these tools add value only when linked to prespecified clinical questions and consensus actions; prospective studies are needed to validate standardised, outcome-improving response-adaptive algorithms that integrate imaging and liquid biopsy. Key implementation challenges include tracer availability, harmonised acquisition/reconstruction, threshold definition, and avoiding overtesting. Near-term impact may be greatest in problem-solving and in trial-embedded decision rules that operationalise biomarker-guided care.
Breast cancer management increasingly hinges on decisions made in “grey zones” where tissue sampling is scarce, and tumour biology evolves under therapeutic pressure. This narrative review synthesises evidence on how whole-body imaging biomarkers and circulating tumour DNA (ctDNA) can support response-adaptive pathways at the interface of surgical and systemic care. Four clinically actionable domains are discussed. (a) 16α-[18F]fluoro-17β-estradiol ([18F]FES) positron emission tomography/computed tomography (PET/CT) enables non-invasive, whole-body mapping of functional oestrogen receptor (ER) expression to address receptor discordance, heterogeneous metastases, and selection of endocrine-based strategies. (b) Human epidermal growth factor receptor 2 (HER2)-targeted PET (notably 89Zr-trastuzumab, with emerging alternatives) provides whole-body receptor assessment to uncover actionable HER2-positive disease despite HER2-negative primaries, informing anti-HER2 treatment selection when repeat biopsy is infeasible. (c) In triple-negative breast cancer treated with immune checkpoint inhibitors, 18F-fluorodeoxyglucose (18F-FDG) PET/CT offers quantitative response and whole-body burden assessment but requires immunotherapy-aware interpretation (e.g., confirmation strategies for apparent early progression) to mitigate pseudoprogression and dissociated responses, while simultaneously visualising immune-related adverse events. (d) Pairing early metabolic change on FDG PET/CT with ctDNA kinetics is presented as a biologically complementary approach for response monitoring and risk stratification, with potential to inform trial-embedded response-adaptive hypotheses, with ctDNA offering a rapid systemic trajectory and PET providing lesion-level localisation in heterogeneous or oligoprogressive disease. Overall, these tools add value only when linked to prespecified clinical questions and consensus actions; prospective studies are needed to validate standardised, outcome-improving response-adaptive algorithms that integrate imaging and liquid biopsy. Key implementation challenges include tracer availability, harmonised acquisition/reconstruction, threshold definition, and avoiding overtesting. Near-term impact may be greatest in problem-solving and in trial-embedded decision rules that operationalise biomarker-guided care.
DOI: https://doi.org/10.37349/etat.2026.1002398
This article belongs to the special issue Breaking Boundaries in Breast Cancer Care: Emerging Controversies and Innovation in Surgical and Medical Approaches
Breast cancer survival is shaped by a complex interaction of tumor-specific, biological, and patient-related factors. Stage at diagnosis remains the strongest predictor of outcome. Tumor size, nodal involvement, and histologic grade further aid in prognostic prediction by reflecting the biological aggressiveness of the disease. Since the early 2000s, molecular characteristics gained importance in risk stratification. Hormone receptor-positive cancers generally respond well to endocrine therapy, while HER2-positive tumors, once associated with poor outcomes, now benefit from targeted therapy. Newer agents and combinations such as CDK4/6 and PI3K/AKT/mTOR inhibitors are being investigated recently. Patient factors, including age, comorbidities, and overall health, also influence outcome and treatment tolerance. Cardiovascular toxicity from chemotherapy and radiotherapy has become an important consideration, particularly in the elderly. Although modern radiotherapy techniques have reduced cardiac risks, long-term cardiovascular mortality remains a competing cause of death in many survivors. Studies comparing breast-conserving therapy with mastectomy suggest improved overall survival with the former, partly due to reduced treatment morbidity. Early detection through mammography, ultrasound, and awareness campaigns greatly improves survival, yet access remains unequal in low-resource settings. Strengthening healthcare systems, tailoring treatments, expanding multidisciplinary care and improving public education are essential. Affordable personalized therapies, better infrastructure, and international collaboration can reduce disparities and enhance global breast cancer outcomes. Our international team researched literature information as well as summarizing up-to-date opinions from global experts, including those with limited resources and war-torn regions.
Breast cancer survival is shaped by a complex interaction of tumor-specific, biological, and patient-related factors. Stage at diagnosis remains the strongest predictor of outcome. Tumor size, nodal involvement, and histologic grade further aid in prognostic prediction by reflecting the biological aggressiveness of the disease. Since the early 2000s, molecular characteristics gained importance in risk stratification. Hormone receptor-positive cancers generally respond well to endocrine therapy, while HER2-positive tumors, once associated with poor outcomes, now benefit from targeted therapy. Newer agents and combinations such as CDK4/6 and PI3K/AKT/mTOR inhibitors are being investigated recently. Patient factors, including age, comorbidities, and overall health, also influence outcome and treatment tolerance. Cardiovascular toxicity from chemotherapy and radiotherapy has become an important consideration, particularly in the elderly. Although modern radiotherapy techniques have reduced cardiac risks, long-term cardiovascular mortality remains a competing cause of death in many survivors. Studies comparing breast-conserving therapy with mastectomy suggest improved overall survival with the former, partly due to reduced treatment morbidity. Early detection through mammography, ultrasound, and awareness campaigns greatly improves survival, yet access remains unequal in low-resource settings. Strengthening healthcare systems, tailoring treatments, expanding multidisciplinary care and improving public education are essential. Affordable personalized therapies, better infrastructure, and international collaboration can reduce disparities and enhance global breast cancer outcomes. Our international team researched literature information as well as summarizing up-to-date opinions from global experts, including those with limited resources and war-torn regions.
DOI: https://doi.org/10.37349/emed.2026.1001423
The human gut microbiota plays a critical role in regulating host health and disease, making it a key target for the development of targeted microbial therapies. This review focuses on designer probiotics and synbiotics, which are genetically engineered microorganisms used in combination with prebiotics to modulate the gut microbiota and support personalised health outcomes. Unlike conventional probiotics, these engineered strains are designed to perform specific metabolic or signalling functions, thereby enhancing colonisation efficiency and functional efficacy. The article summarises recent advancements in systems biology, synthetic biology, and omics technologies (including genomics, proteomics, and metabolomics) that facilitate the design and optimisation of next-generation microbial formulations. Their significance lies in enabling precision nutrition and the development of functional foods tailored to individual host requirements. This review also discusses strategies for microbial strain engineering, synbiotic formulation, and the application of high-throughput omics approaches to better understand host-microbe interactions. Furthermore, it highlights applications in managing gut-related disorders and improving food quality. While addressing challenges such as biosafety concerns, regulatory limitations, and environmental implications, the review emphasises the potential of designer probiotics and synbiotics as innovative tools for precision-guided health through dietary interventions. Overall, this emerging field provides a sustainable approach to advancing nutrition and microbiome-based therapies by bridging precision health with food science.
The human gut microbiota plays a critical role in regulating host health and disease, making it a key target for the development of targeted microbial therapies. This review focuses on designer probiotics and synbiotics, which are genetically engineered microorganisms used in combination with prebiotics to modulate the gut microbiota and support personalised health outcomes. Unlike conventional probiotics, these engineered strains are designed to perform specific metabolic or signalling functions, thereby enhancing colonisation efficiency and functional efficacy. The article summarises recent advancements in systems biology, synthetic biology, and omics technologies (including genomics, proteomics, and metabolomics) that facilitate the design and optimisation of next-generation microbial formulations. Their significance lies in enabling precision nutrition and the development of functional foods tailored to individual host requirements. This review also discusses strategies for microbial strain engineering, synbiotic formulation, and the application of high-throughput omics approaches to better understand host-microbe interactions. Furthermore, it highlights applications in managing gut-related disorders and improving food quality. While addressing challenges such as biosafety concerns, regulatory limitations, and environmental implications, the review emphasises the potential of designer probiotics and synbiotics as innovative tools for precision-guided health through dietary interventions. Overall, this emerging field provides a sustainable approach to advancing nutrition and microbiome-based therapies by bridging precision health with food science.
DOI: https://doi.org/10.37349/eff.2026.1010182
Aim:
Allostatic load (AL) is a composite measure of cumulative physiological stress, but its role in heart failure (HF) onset and prognosis remains unclear.
Methods:
We analyzed data from two U.S. cohorts. Logistic regression assessed AL and incident HF in 3,814 adults from the Health and Retirement Study (HRS, 2016–2020). Cox regression examined AL with cardiovascular and all-cause mortality in 1,200 HF patients from the National Health and Nutrition Examination Survey (NHANES, 1999–2010 and 2015–2016). AL was derived from nine biomarkers and categorized as low (0–2), medium (3), or high (≥ 4).
Results:
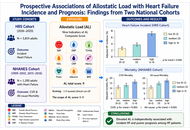
In HRS, after full adjustment, high AL was associated with increased incident HF risk versus low AL (OR = 2.07; 95% CI: 1.29–3.32; P = 0.002), with each 1-unit increase raising risk by 30% (P < 0.001). In NHANES, after full adjustment, high AL predicted elevated cardiovascular (HR = 2.03; 95% CI: 1.37–3.03; P < 0.001) and all-cause mortality (HR = 1.70; 95% CI: 1.30–2.22; P < 0.001). Per unit increase, AL raised cardiovascular mortality by 18% and all-cause mortality by 15%. Model performance improved modestly with AL.
Conclusions:
Elevated AL is independently associated with HF incidence and poorer prognosis, supporting its potential as an integrative biomarker for HF risk stratification and prevention.
Aim:
Allostatic load (AL) is a composite measure of cumulative physiological stress, but its role in heart failure (HF) onset and prognosis remains unclear.
Methods:
We analyzed data from two U.S. cohorts. Logistic regression assessed AL and incident HF in 3,814 adults from the Health and Retirement Study (HRS, 2016–2020). Cox regression examined AL with cardiovascular and all-cause mortality in 1,200 HF patients from the National Health and Nutrition Examination Survey (NHANES, 1999–2010 and 2015–2016). AL was derived from nine biomarkers and categorized as low (0–2), medium (3), or high (≥ 4).
Results:
In HRS, after full adjustment, high AL was associated with increased incident HF risk versus low AL (OR = 2.07; 95% CI: 1.29–3.32; P = 0.002), with each 1-unit increase raising risk by 30% (P < 0.001). In NHANES, after full adjustment, high AL predicted elevated cardiovascular (HR = 2.03; 95% CI: 1.37–3.03; P < 0.001) and all-cause mortality (HR = 1.70; 95% CI: 1.30–2.22; P < 0.001). Per unit increase, AL raised cardiovascular mortality by 18% and all-cause mortality by 15%. Model performance improved modestly with AL.
Conclusions:
Elevated AL is independently associated with HF incidence and poorer prognosis, supporting its potential as an integrative biomarker for HF risk stratification and prevention.
DOI: https://doi.org/10.37349/ec.2026.1012118
Aim:
Telemonitoring apps are increasingly prescribed as part of self-management for patients with Chronic Obstructive Pulmonary Disease (COPD), yet patients still make minimal use of these apps. This research investigates explanatory factors associated with the behavioral intention to use and actual use of COPD telemonitoring apps among users and non-users.
Methods:
A cross-sectional study was conducted among 200 COPD patients from two Dutch hospitals. Eligible participants (≥ 18 years, diagnosed with COPD, ≥ 2 outpatient pulmonology visits in 2023) were identified through the electronic health record and invited by mail. Participants completed a self-administered questionnaire assessing demographics, disease severity, literacy, facilitating conditions, and app-related factors, based on the Unified Theory of Acceptance and Use of Technology 2 (UTAUT2), the Technology Acceptance Model (TAM), and the Reasoned Action Approach (RAA). Behavioral intention was analyzed using hierarchical multiple regression, and use was analyzed using binomial logistic regression.
Results:
Intention was explained by performance expectancy (coefficient = 0.760, p ≤ 0.001), self-efficacy (coefficient = 0.207, p = 0.009), and alignment with personal norms and values (coefficient = 0.163, p = 0.006). Use was explained by self-efficacy (OR = 1.992, p = 0.023), social influence (OR = 1.642, p = 0.039), personalization (OR = 0.628, p = 0.039), and intention to use (OR = 3.459, p ≤ 0.001). App users showed significantly higher digital literacy, performance expectancy, and fewer symptoms compared to non-users. Users also experienced significantly higher importance of social influence and alignment with norms and values than non-users. Demographic variables and disease severity were no significant predictors of behavioral intention and use.
Conclusions:
Optimizing the app and the supportive role of the healthcare professional, enhancing digital and health literacy, and hybrid care ensures that patients can benefit from both traditional care and the advantages of remote monitoring.
Aim:
Telemonitoring apps are increasingly prescribed as part of self-management for patients with Chronic Obstructive Pulmonary Disease (COPD), yet patients still make minimal use of these apps. This research investigates explanatory factors associated with the behavioral intention to use and actual use of COPD telemonitoring apps among users and non-users.
Methods:
A cross-sectional study was conducted among 200 COPD patients from two Dutch hospitals. Eligible participants (≥ 18 years, diagnosed with COPD, ≥ 2 outpatient pulmonology visits in 2023) were identified through the electronic health record and invited by mail. Participants completed a self-administered questionnaire assessing demographics, disease severity, literacy, facilitating conditions, and app-related factors, based on the Unified Theory of Acceptance and Use of Technology 2 (UTAUT2), the Technology Acceptance Model (TAM), and the Reasoned Action Approach (RAA). Behavioral intention was analyzed using hierarchical multiple regression, and use was analyzed using binomial logistic regression.
Results:
Intention was explained by performance expectancy (coefficient = 0.760, p ≤ 0.001), self-efficacy (coefficient = 0.207, p = 0.009), and alignment with personal norms and values (coefficient = 0.163, p = 0.006). Use was explained by self-efficacy (OR = 1.992, p = 0.023), social influence (OR = 1.642, p = 0.039), personalization (OR = 0.628, p = 0.039), and intention to use (OR = 3.459, p ≤ 0.001). App users showed significantly higher digital literacy, performance expectancy, and fewer symptoms compared to non-users. Users also experienced significantly higher importance of social influence and alignment with norms and values than non-users. Demographic variables and disease severity were no significant predictors of behavioral intention and use.
Conclusions:
Optimizing the app and the supportive role of the healthcare professional, enhancing digital and health literacy, and hybrid care ensures that patients can benefit from both traditional care and the advantages of remote monitoring.
DOI: https://doi.org/10.37349/edht.2026.1011101
With the rising global prevalence of obesity and type 2 diabetes, metabolic disorders have become major drivers of cardiovascular morbidity and mortality worldwide. Cardiovascular-kidney-metabolic (CKM) syndrome encompasses obesity, type 2 diabetes mellitus (T2DM), chronic kidney disease (CKD), and cardiovascular disease (CVD), all of which share common pathophysiological pathways. Glucagon-like peptide-1 receptor agonists (GLP-1RAs), a novel class of antihyperglycemic agents, have demonstrated pleiotropic effects—including weight reduction, blood pressure lowering, albuminuria reduction, decreased major adverse cardiovascular events (MACE), and slowed progression of renal dysfunction. These benefits position GLP-1RAs as a potential cornerstone therapy for CKM syndrome. This review synthesizes recent advances in GLP-1RA research within the CKM framework, explores their underlying mechanisms, and offers insights to refine diagnostic and therapeutic strategies for cardiometabolic diseases.
With the rising global prevalence of obesity and type 2 diabetes, metabolic disorders have become major drivers of cardiovascular morbidity and mortality worldwide. Cardiovascular-kidney-metabolic (CKM) syndrome encompasses obesity, type 2 diabetes mellitus (T2DM), chronic kidney disease (CKD), and cardiovascular disease (CVD), all of which share common pathophysiological pathways. Glucagon-like peptide-1 receptor agonists (GLP-1RAs), a novel class of antihyperglycemic agents, have demonstrated pleiotropic effects—including weight reduction, blood pressure lowering, albuminuria reduction, decreased major adverse cardiovascular events (MACE), and slowed progression of renal dysfunction. These benefits position GLP-1RAs as a potential cornerstone therapy for CKM syndrome. This review synthesizes recent advances in GLP-1RA research within the CKM framework, explores their underlying mechanisms, and offers insights to refine diagnostic and therapeutic strategies for cardiometabolic diseases.
DOI: https://doi.org/10.37349/eemd.2026.101481
